[Complex injuries of the spine]
Related Experiment Video
Updated: Aug 19, 2026
A Novel Vertebral Stabilization Method for Producing Contusive Spinal Cord Injury
Published on: January 5, 2015

Abstract:
3 different types of complex spinal trauma are defined: Type I means a multilevel contiguous or non contiguous unstable injury, type II is described as a spinal injury with concomitant thoracic or abdominal lesion, type III stands for the coincidence of spinal injury and polytrauma. Overlapping of different types occurs. Type I: The incidence amounts according a german multicenter study to about 2.5%. Multilevel injuries need to be stabilized for a long distance from posterior. With a thorough analysis the segments to be fused are determined. Type II: The leading thoracic injury is a lung contusion which occurs in up to 50% of the cases. A CT scan of the thorax during the first diagnostic screening is recommended. Early reduction and stabilization from posterior should be aimed at. During the first two weeks anterior procedures are contraindicated. Abdominal injuries are to be found in 3-4% of all spinal injuries. All organs could be affected. A typical constallation is the "seat-belt syndrome" with lesions of the upper abdominal organs and a flexiondistraction injury of the upper lumbar spine. The main problem is to make the diagnosis of both components initially. Most of the patients may be treated in one operation by first taking care of the abdominal injury and than stabilizing the spine. The prognosis of this combination is favorable. Type III: In 17-18% of all polytraumatized patients lesions of the spine are to be diagnosed. From these only one third need surgical care. From 680 patients with operatively treated fractures of the thoracolumbar junction 6.2% were polytraumatized according to the multicenter study mentioned above. The risk of missing a spinal injury in polytrauma totals approximately 20%. Surgical stabilization should be performed in the primary phase (day-1-surgery). Additional injuries, potentially time consuming operations with a high blood loss sometimes necessitate a different approach. Non stabilized spinal injuries apparently do not have the same negative effect on the whole organism as long bone fractures. In the early phase of treatment on the C-spine only anterior procedures and on the thoracolumbar spine only posterior techniques should be applied.
Related Concept Videos
 01:16
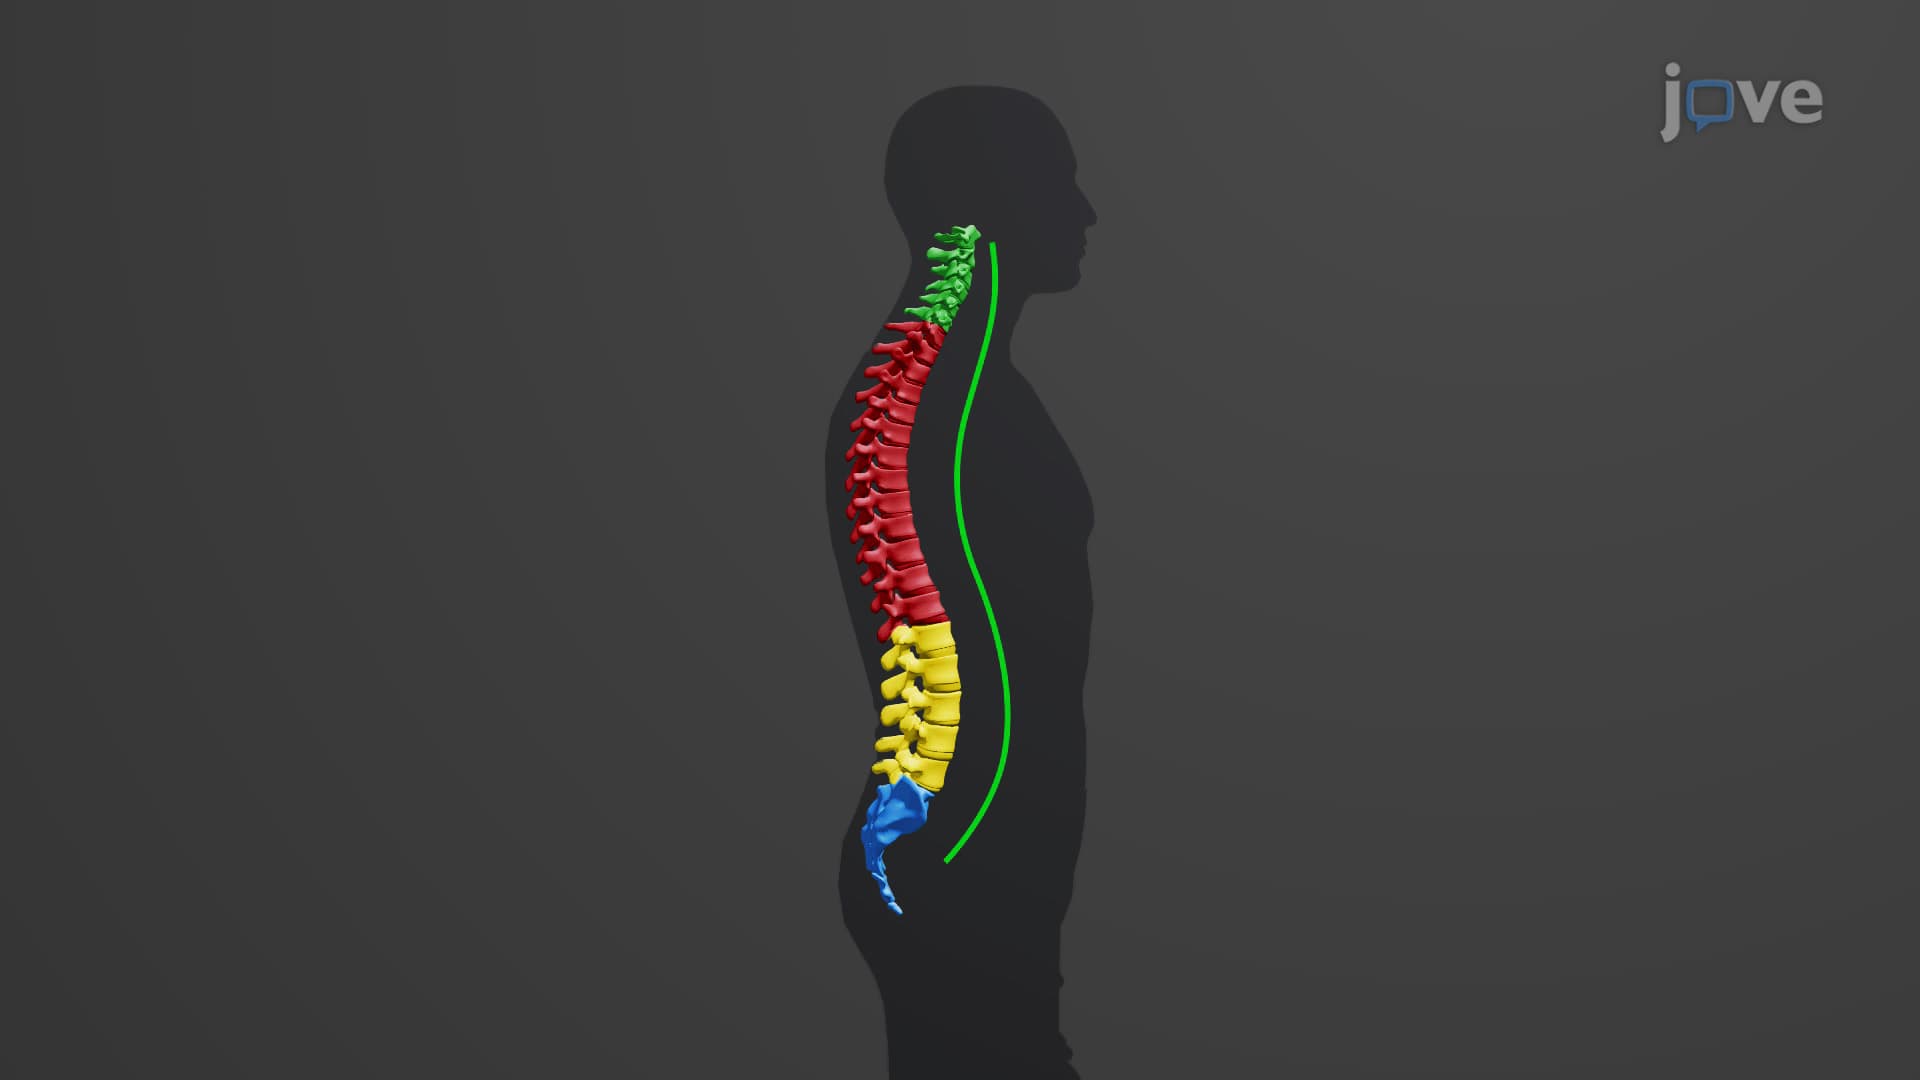
Vertebral Column: Regions and Curvature
Regions of the Vertebral Column
In an adult, the spine is subdivided into five regions: the cervical, the thoracic, the lumbar, the sacral, and the coccygeal region. The spine initially develops as a series of 33 vertebrae; after 20 years of age, the nine bones in the sacral region, five sacral, and four coccygeal bones fuse to form the...
 01:27
Muscles of the Vertebral Column
Superficial Layer:
The superficial layer consists primarily of the splenius muscles, which include the splenius capitis and splenius cervicis. These muscles are mainly responsible for the head and cervical spine movements, including extension, rotation, and lateral bending. The splenius capitis...
 01:15
Spinal Cord: Gross Anatomy
 01:14
Spinal Cord Injury ll: Pathophysiology
 01:29
Herniated Intervertebral Disc l: Introduction
 01:25
Secondary Spinal Cord Injury llI: Pathophysiology