Duplex ultrasound in the hemodynamic evaluation of the late sequelae of deep venous thrombosis
Related Experiment Video
Updated: Oct 30, 2026
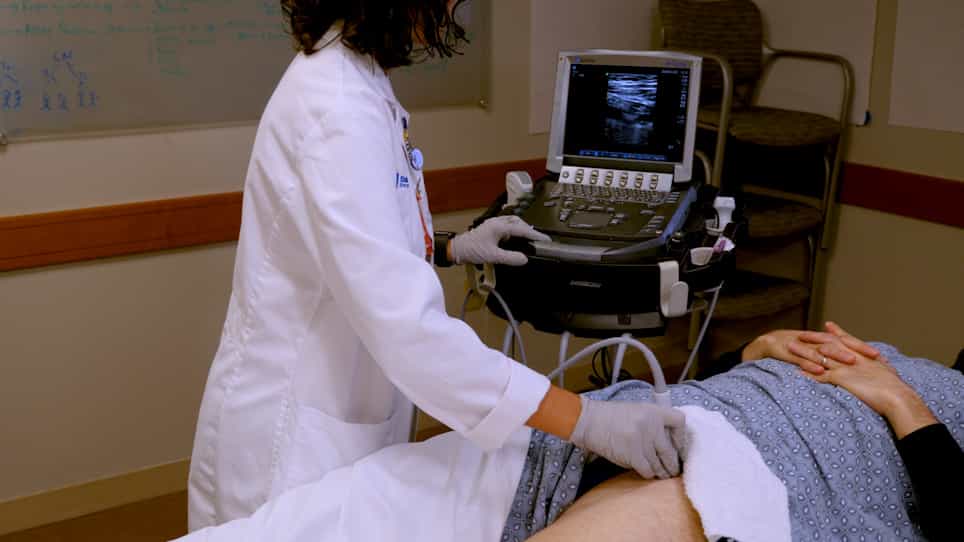
Point-Of-Care Ultrasound Screening for Proximal Lower Extremity Deep Venous Thrombosis
Published on: February 10, 2023
J H Haenen1, M C Janssen, H van Langen
1Clinical Vascular Laboratory, University Hospital, Nijmegen, The Netherlands.

Insights
Deep venous thrombosis (DVT) often leads to long-term venous abnormalities, with reflux being the most common issue years later. These findings highlight the persistent impact of DVT on venous health.
Area of Science:
- Vascular Medicine
- Diagnostic Imaging
- Medical Ultrasound
Background:
- Deep venous thrombosis (DVT) is a significant vascular condition with potential long-term sequelae.
- Understanding the chronic hemodynamic consequences of DVT is crucial for patient management.
- Previous diagnoses of DVT were established using phlebography.
Purpose of the Study:
- To evaluate the long-term hemodynamic outcome of deep venous thrombosis (DVT).
- To assess venous abnormalities 7 to 13 years post-initial DVT diagnosis using duplex ultrasound.
Main Methods:
- Duplex ultrasound was employed to examine 1212 vein segments in 72 patients with a history of DVT.
- Vein segments were assessed for reflux, obstruction (noncompressibility), and flow.
- Data were compared between initially thrombosed and non-thrombosed segments, and with 31 healthy controls for reflux definition.
Main Results:
- After 7-13 years, 89% of patients exhibited venous abnormalities.
- Reflux was the most common abnormality (46%), followed by noncompressibility (8%), and combined findings (35%).
- Initially thrombosed proximal vein segments showed significantly higher rates of reflux (46%) and noncompressibility (12%) compared to non-thrombosed segments.
Conclusions:
- Venous abnormalities persist in most patients with a history of DVT for 7-13 years.
- Reflux is the predominant long-term abnormality following DVT.
- Initially thrombosed segments, particularly in the proximal veins, are more prone to chronic abnormalities.
Purpose:
The use of duplex ultrasound scanning to evaluate the hemodynamic outcome of deep venous thrombosis 7 to 13 years after the original diagnosis.
Methods:
Duplex ultrasound was used to re-examine 1212 segments of vein from 72 patients (49 men, 23 women) with deep venous thrombosis previously diagnosed by means of phlebography to detect reflux and obstruction and evaluate flow; 611 segments were initially thrombosed and 601 segments were open. To define reflux, reversed flow in 31 healthy persons was measured.
Results:
In a review of all veins of the 72 patients, 8 patients (11%) had completely normal duplex results in all veins, 33 (46%) had reflux, 6 (8%) had at least one noncompressible vein segment, and 25 (35%) had a combination of both. In the proximal vein segments without initial thrombosis a higher percentage was normal (73%) than in segments with initial thrombosis (46%). There was a significantly higher frequency of reflux (46%, p = 0.05) and noncompressibility (12%, p < 0.01) in initially thrombosed proximal vein segments than in vein segments without initial thrombosis (reflux 25%, noncompressibility 3%). Distal to the knee 125 (17%) of 720 vein segments were not traceable. Significantly more initially thrombosed vein segments were not traceable (p < 0.01). In distal vein segments there was no significant difference in reflux (7% versus 5%) and noncompressibility (10% versus 5%) between vein segments with and without initial thrombosis. Flow was present in 99% of the 611 previously thrombosed proximal and distal segments.
Conclusions:
Most patients with deep venous thrombosis still had venous abnormalities 7 to 13 years after the initial diagnosis. The most common abnormality was reflux. Significantly more abnormalities were found in initially thrombosed segments. The abnormalities were found in the proximal vein segments and in the distal vein segments, although less frequently in the latter.
Related Concept Videos
 01:20
Venous Thrombosis II: Clinical Manifestations and Diagnostic Studies
 01:29
Venous Thrombosis III: Interprofessional Care
 01:30
Venous Thrombosis I: Introduction
 01:30
Venous Thrombosis IV: Nursing Management
 01:26
Varicose Veins II: Diagnostic Studies and Interprofessional Care
 01:27
Assessment of the Cardiovascular System III: Palpation
Jugular Venous Pressure (JVP) Measurement
Position the patient at a thirty- to forty-five-degree angle or in a semi-fowler's position. Look for the highest point of pulsation in the internal jugular vein and measure the vertical distance to the angle of Loius or sternal angle. A normal JVP is 3-4 cm above the...