Related Experiment Video
Updated: Aug 15, 2026

RNAscope for In situ Detection of Transcriptionally Active Human Papillomavirus in Head and Neck Squamous Cell Carcinoma
Published on: March 11, 2014
Nonnasopharyngeal lymphoepithelioma of the head and neck
1Department of Radiation Oncology, University of Texas M. D. Anderson Cancer Center, Houston 77030, USA.

Background:
Lymphoepithelioma (squamous cell carcinoma with associated lymphoid stroma) commonly occurs in the nasopharynx, rarely at other sites. As a result, the clinical course and optimal treatment of nonnasopharyngeal lymphoepithelioma of the head and neck have not been well described. This retrospective study was undertaken to analyze the clinical course of the disease in patients treated at a single institution and to formulate recommendations for treatment based on that experience as well as results reported in the literature.
Methods:
Between 1950 and 1994, 34 patients with nonnasopharyngeal lymphoepithelioma of the head and neck were treated at the University of Texas M. D. Anderson Cancer Center. The patients' medical records were reviewed and their pathologic specimens evaluated. The primary tumor sites were: oropharynx (24 patients), salivary gland (4), laryngohypopharynx (4), and the maxillary sinus/nasal cavity (2). Assessed in accordance with the 1992 American Joint Committee Against Cancer TNM staging system, T classifications were TX-2, T1-7, T2-8, T3-10, and T4-7, and N classifications were N0-8, N1-5, N2-15, and N3-6. Treatment consisted of radiotherapy for 24 patients, excisional biopsy of the primary tumor followed by radiotherapy for 7 patients, and surgery for 3 patients. Of the patients treated with radiotherapy, neck dissections were performed on only two, both of whom had persistent lymph node masses after completing radiotherapy. The median dose delivered to the primary tumor was 65 gray (Gy) (range, 46-78 Gy). The median fraction size was 2.1 Gy (range, 1.6-3.2 Gy).
Results:
The 5-year actuarial disease specific survival and overall survival rates were 59% and 39%, respectively. The 5-year actuarial local control rate for all patients was 94%. For the irradiated patients, the 5-year regional control rates were 77% overall and 83% within the radiation field. The 5-year actuarial rate of distant metastasis for all patients was 30%. For patients who presented with and without regional adenopathy, the 5-year rates of distant metastasis were 36% and 12%, respectively (P = 0.27).
Conclusions:
Nonnasopharygeal lymphoepithelioma is a radiosensitive disease. High rates of locoregional tumor control were achieved with radiotherapy at all head and neck sites. The main cause of treatment failure was distant metastasis, which occurred more frequently in patients with lymph node involvement. Radiotherapy is appropriate initial locoregional therapy for patients with this disease. Surgery should be reserved for patients who have persistent disease after completing radiotherapy. Systemic therapy is a reasonable approach for patients who present with regional adenopathy because they have a relatively high rate of distant metastasis.
Related Concept Videos
 01:16
Primary Lymphoid Organs
The red bone marrow is a soft, spongy tissue nestled in the interior of long bones such as the humerus and femur. It is the site...
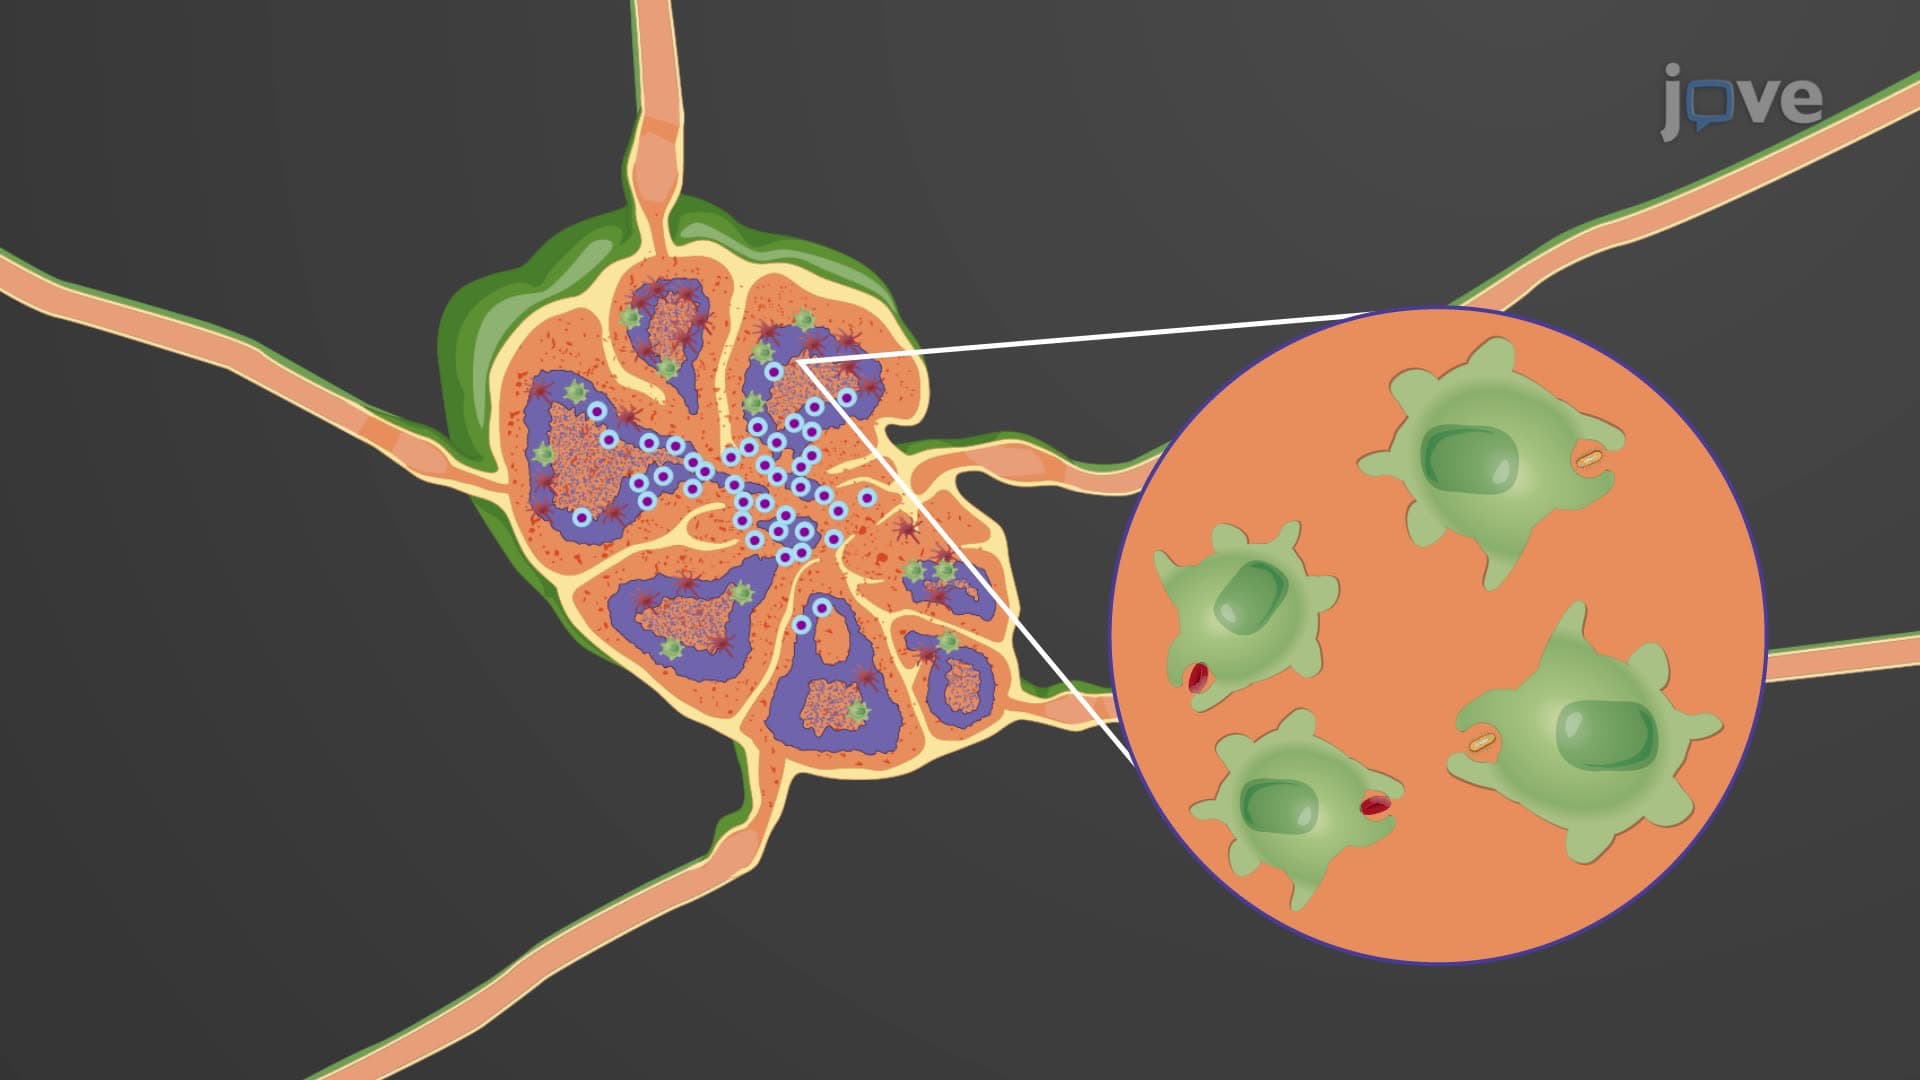 01:15
Secondary Lymphoid Organs
The spleen is a vital organ in the lymphatic system, nestled in the upper left side of the abdomen. It is composed of two primary regions: the red pulp and the white pulp, each having distinct functions. The red pulp performs a significant role in blood filtration. It efficiently purges the blood of old or damaged red blood cells and...
 01:23
Detailed Structure and Function of Lymph Nodes
From a histological perspective, lymph nodes can be split into two main areas: the superficial cortex and the deep medulla. The outer cortex is populated by dendritic cells, macrophages, and B lymphocytes, which are densely packed into follicles. When these B-lymphocytes are presented...