Related Experiment Video
Updated: Oct 29, 2026
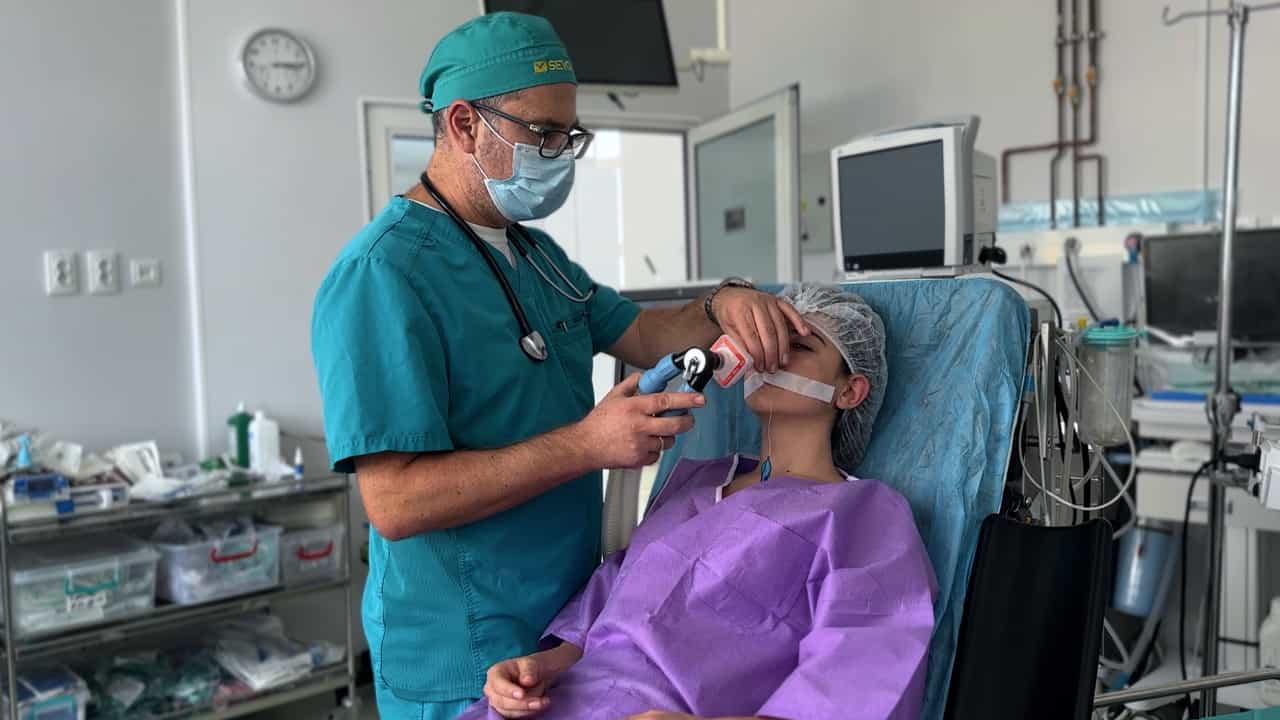
The Flexible Rhino-Laryngoscope for Awake Nasotracheal Intubation
Published on: August 2, 2024
A comparison of awake versus paralyzed tracheal intubation for infants with pyloric stenosis
S D Cook-Sather1, H V Tulloch, A Cnaan
1Department of Anesthesiology and Critical Care Medicine, The Children's Hospital of Philadelphia, Pennsylvania 19104-4399, USA.

Insights
Anesthetized, paralyzed tracheal intubation is superior for infants with pyloric stenosis, offering higher success rates and shorter intubation times compared to awake intubation. This method is recommended for routine anesthetic management.
Area of Science:
- Pediatric Anesthesiology
- Surgical Procedures
Background:
- Pyloric stenosis is a common surgical condition in infants.
- Tracheal intubation is a critical step in the anesthetic management of these infants.
- The optimal intubation technique (awake vs. paralyzed) remains a subject of study.
Purpose of the Study:
- To compare the efficacy and safety of awake versus anesthetized, paralyzed tracheal intubation in infants with pyloric stenosis.
- To evaluate key metrics including first-attempt success rate, intubation time, physiological changes, and complication incidence.
Main Methods:
- Prospective, nonrandomized, observational study involving 76 infants with pyloric stenosis.
- Three intubation groups: awake (A), rapid-sequence induction (R), and modified rapid-sequence induction (M).
- Data collected on intubation success, time, heart rate (HR), oxygen saturation (SpO2), and complications.
Main Results:
- Higher first-attempt intubation success rate in paralyzed groups (R and M) at 87% versus 64% in the awake group (A) (P = 0.028).
- Shorter median intubation time for paralyzed groups (34s) compared to the awake group (63s) (P = 0.004).
- No significant differences in transient decreases in HR or SpO2, or incidences of bradycardia and desaturation between groups.
Conclusions:
- Anesthetized, paralyzed tracheal intubation is not inferior to awake intubation for infants with pyloric stenosis regarding oxygenation, heart rate stability, and complications.
- The study advocates for the routine use of anesthetized, paralyzed intubation in this patient population.
- Awake intubation should be abandoned for routine anesthetic management of infants with pyloric stenosis due to longer duration and lower success rates.
Unlabelled:
This prospective, nonrandomized, observational study of 76 infants with pyloric stenosis was conducted at an academic children's hospital and compared awake versus paralyzed tracheal intubation in terms of successful first attempt rate, intubation time, heart rate (HR) and arterial hemoglobin oxygen saturation (SpO2) changes, and complications. Three groups were determined by intubation method: awake (A) with an oxygen-insufflating laryngoscope, after rapid-sequence induction (R), or after modified rapid-sequence induction (M) including ventilation through cricoid pressure. Successful first attempt intubation rate was 64% for Group A versus 87% for paralyzed Groups R and M (P = 0.028). Median intubation time was 63 s in Group A versus 34 s in Groups R and M (P = 0.004). Transient, mild decreases in mean HR and SpO2 and incidences of significant bradycardia and decreased SpO2 did not vary by group. Complications, including bronchial or esophageal intubation, emesis, and oropharyngeal trauma, were few. Senior anesthesiologists intervened in four tracheal intubations. We advocate anesthetized, paralyzed tracheal intubation because struggling with conscious infants takes longer, often requires multiple attempts, and prevents neither bradycardia nor decreased SpO2. After induction, additional mask ventilation with O2 confers no advantage over immediate tracheal intubation in preserving SpO2.
Implications:
In our children's hospital, awake tracheal intubation was not superior to anesthetized, paralyzed intubation in maintaining adequate oxygenation and heart rate or in reducing complications, and should be abandoned in favor of the latter technique for routine anesthetic management of otherwise healthy infants with pyloric stenosis.

Related Concept Videos
 01:15
Endotracheal Intubation I: Procedure
The ET tube comprises various components, including a standard adaptor to attach a bag-valve-mask (BVM) or ventilator, a cuff, a pilot balloon, and radiopaque markings along its length to measure the insertion distance. The tube sizes...
 01:30
Cardiopulmonary Resuscitation V: Advanced Airway Management Techniques
 01:11
Pyloric Obstruction
 01:17
Endotracheal Intubation II: Nursing Management
1. Nursing Care of Patients Before Intubation
Before the endotracheal intubation procedure, nurses play an essential role in ensuring the process goes smoothly. The nurses must be familiar with intubation...
 01:24
Endotracheal Tube Extubation
Procedure
Extubation removes the endotracheal tube (ETT) from the patient on mechanical ventilation. It requires a well-coordinated, multidisciplinary approach involving physicians, nurses, respiratory therapists, and other healthcare professionals.
 01:28
Tracheostomy: Procedure and Tubes
Tracheostomy tubes can be made of semiflexible plastic (polyurethane or silicone), rigid plastic, or metal, and they come in...