[Pathomorphology of coronary atherosclerosis]
Related Experiment Video
Updated: Oct 29, 2026
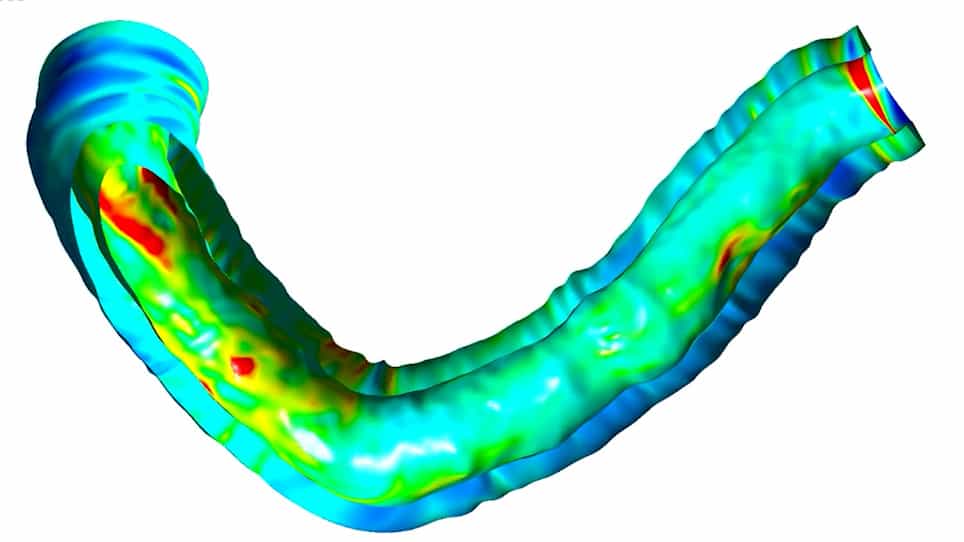
Optical Coherence Tomography Based Biomechanical Fluid-Structure Interaction Analysis of Coronary Atherosclerosis Progression
Published on: January 15, 2022
1Institut für Pathologie, Universität Freiburg. ihling@frk1.ukl.uni-freiburg.de

Insights
Atherosclerosis involves chronic inflammation and wound healing, with plaque rupture causing acute coronary syndromes. Endothelin-1 (ET-1) is implicated in plaque activity and vasoreactivity, potentially contributing to atherosclerosis progression.
Area of Science:
- Cardiovascular Pathology
- Inflammation Biology
- Vascular Medicine
Context:
- Atherosclerosis is a chronic inflammatory disease characterized by plaque buildup in arteries.
- Plaque rupture and subsequent thrombosis are major causes of acute coronary syndromes.
- The American Heart Association Committee on Vascular Lesions provides a morphologic classification for atherosclerotic plaques.
Purpose:
- To investigate the role of endothelin-1 (ET-1) in active coronary atherosclerotic lesions.
- To correlate ET-1 expression with plaque morphology and inflammatory processes.
- To understand ET-1's contribution to vasoreactivity and potential role in atherosclerosis progression.
Summary:
- Atherosclerotic plaques share characteristics with chronic inflammation and wound healing.
- Active plaques exhibit features like a large lipid core, increased macrophages, and thin fibrous caps.
- ET-1, a potent vasoconstrictor, is found in inflammatory cells within plaques and is upregulated in active lesions.
Impact:
- Findings suggest ET-1 plays a dual role in atherosclerosis, potentially aiding vessel wall stabilization post-rupture while promoting vasospasm and disease progression.
- This research provides a framework for relating clinical findings to plaque morphology.
- Understanding ET-1's role may lead to novel therapeutic strategies for managing atherosclerosis and acute coronary syndromes.
Abstract:
The "American Heart Association Committee on Vascular Lesions" suggests the following morphologic classification of atherosclerotic plaques: the classification is based on large autopsy studies facilitating the assessment of the natural course of atherosclerotic lesions at precisely defined progression prone areas of the coronary tree from their clinically silent beginning to the stage where they produce symptoms. Lesion evolution is divided in 5 phases reflecting the possible time course of plaque development. Each phase is characterized by plaques with a distinctive morphology. The classification offers a framework of typical morphologies which the results of clinical investigations may be related to. Looking at the plaque composition, it is readily conceivable that atherosclerosis shares many characteristics with the general pathology of chronic inflammation and wound healing. Clinical symptoms e.g. acute coronary syndromes, arise from inflammation-mediated endothelial erosion and/or plaque rupture with ensuring coronary thrombosis. Advanced or complicated plaques are composed of different kinds of constituents in varying proportions. However, plaques at risk display a large lipid core occupying more than 40% of the plaque's volume, increased numbers of macrophages, reduced numbers of smooth muscle cells, an increased expression of tissue factor, and a thin plaque cap. Functionally, active plaques are characterized by a locally enhanced vasoreactivity with evidence coming from our own recent investigations that localised chronic inflammatory processes within the atherosclerotic plaque are responsible not only for the plaque rupture itself, but also for the hyperreactivity of these vessels to vasoconstrictor stimuli. In this context endothelin 1 (ET-1), a very potent vasoconstrictor peptide, may play an important role. ET-1 was originally reported to be produced by endothelial cells and to act locally in a paracrine fashion to regulate vascular tone. However, further studies have clarified that ET-1 is not only produced by endothelial cells but also by human inflammatory cells suggesting a role for ET-1 in inflammatory processes. Additionally, ET-1 displays a potent mitogenic activity. We examined immunohistochemically the presence of ET-1 in coronary plaque tissue obtained by directional coronary atherectomy. ET-1 immunoreactivity preferentially localized in plaque components indicative of a chronic inflammatory process. In addition, semiquantitative analysis of ET-1-like immunoreactivity revealed significantly higher staining grades in active coronary lesions compared with nonactive lesions. The increased ET-1 content in active coronary lesions may be beneficial to the stabilization of the vessel wall after plaque rupture and disadvantageous because it may lead to vasospasm and to the progression of atherosclerosis.


Related Concept Videos
 01:26
Coronary Artery Disease II: Pathophysiology
 01:30
Atherosclerosis I: Introduction
 01:30
Coronary Artery Disease I: Introduction
 01:27
Atherosclerosis II: Clinical Manifestations and Diagnostic Tests
 01:30
Coronary Artery Disease III: Clinical Manifestations
 01:19
Acute Coronary Syndrome II: Pathophysiology and Clinical Manifestations