Related Experiment Video
Updated: Aug 19, 2026


In vivo Liver Endocytosis Followed by Purification of Liver Cells by Liver Perfusion
Published on: November 10, 2011
Heparin elimination in uraemic patients on Haemodialysis

Heparin (100 U/kg bodyweight) was administered as single i.v. injections, and heparin concentration in plasma determined by polybrene titration. Mean concentration half-life was 74.7 min in the normal group (n = 6), 118.6 min in the nephrectomized patients (n = 5), and 97.8 min in the other uraemic patients (n = 6). The differences between the mean values for the normals and for the 2 patient groups were statistically significant (p is less than 0.001 and p approximately 0.2 respectively). Mean anticoagulant half-life (based on thrombin clotting time) was 64.3, 75.8 and 62.7 min in the 3 groups. The differences between heparin concentration half-life and anticoagulant half-life in the 3 groups were statistically significant. These differences may be partly explained by a significant fall in heparin cofactor activity after injection of heparin. There was a strong positive individual correlation between heparin concentration half-life and anticoagulant half-life in the patients (r = 0.94), but not in the normal group (r = 0.31). There was a strong negative individual correlation between heparin tolerance and heparin concentration half-life in the patients (r = -0.84), but no correlation in the normal group. It is concluded that severely impaired renal function has a significant, but moderate influence on heparin elimination.
Heparin (100 U/kg bodyweight) was administered as single i.v. injections, and heparin concentration in plasma determined by polybrene titration. Mean concentration half-life was 74.7 min in the normal group (n = 6), 118.6 min in the nephrectomized patients (n = 5), and 97.8 min in the other uraemic patients (n = 6). The differences between the mean values for the normals and for the 2 patient groups were statistically significant (p is less than 0.001 and p approximately 0.2 respectively). Mean anticoagulant half-life (based on thrombin clotting time) was 64.3, 75.8 and 62.7 min in the 3 groups. The differences between heparin concentration half-life and anticoagulant half-life in the 3 groups were statistically significant. These differences may be partly explained by a significant fall in heparin cofactor activity after injection of heparin. There was a strong positive individual correlation between heparin concentration half-life and anticoagulant half-life in the patients (r = 0.94), but not in the normal group (r = 0.31). There was a strong negative individual correlation between heparin tolerance and heparin concentration half-life in the patients (r = -0.84), but no correlation in the normal group. It is concluded that severely impaired renal function has a significant, but moderate influence on heparin elimination.


Related Concept Videos
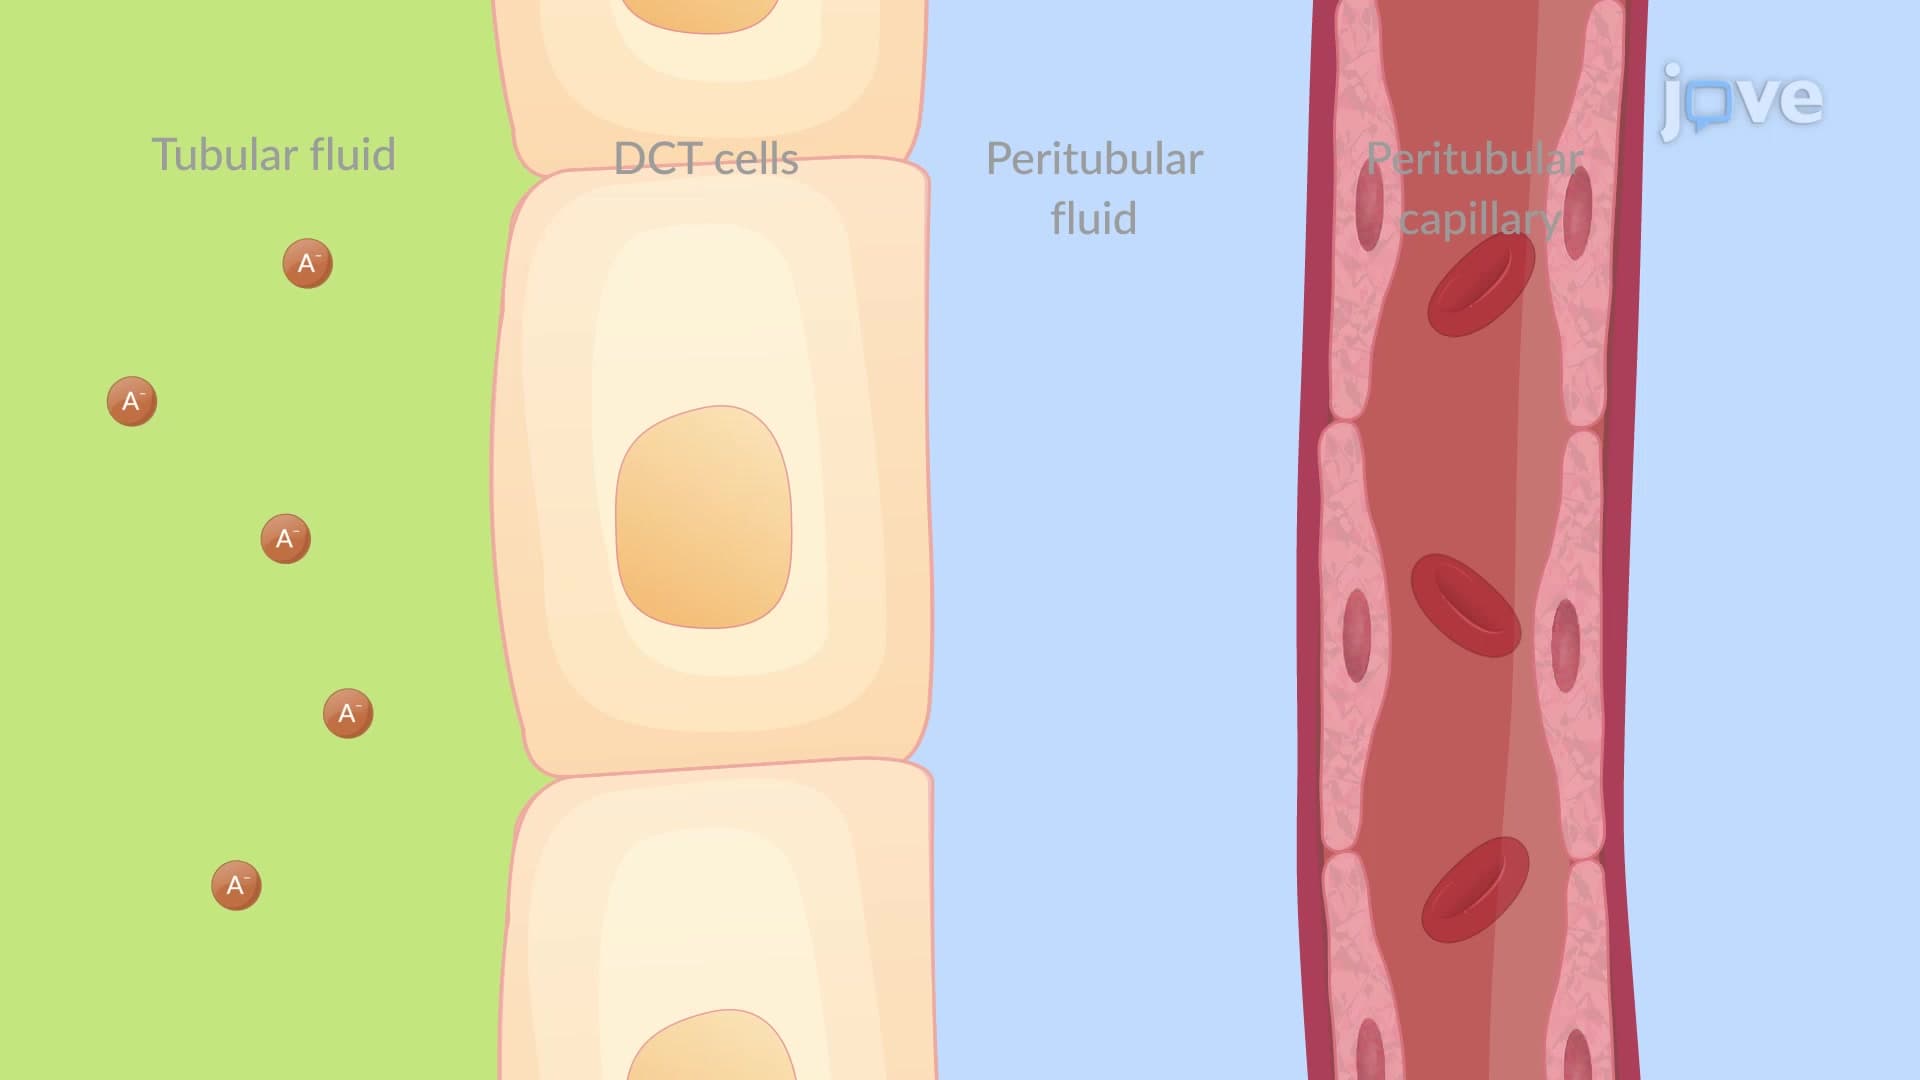 01:22
Drug Elimination by Renal Route: Tubular Reabsorption
 01:30
Anticoagulant Drugs: Low-Molecular-Weight Heparins
 01:28
Renal Drug Excretion: Tubular Secretion
 01:25
Drug Dosing in Renal Diseases: Dose Adjustments Based on Drug Clearance and Elimination Rate Constant
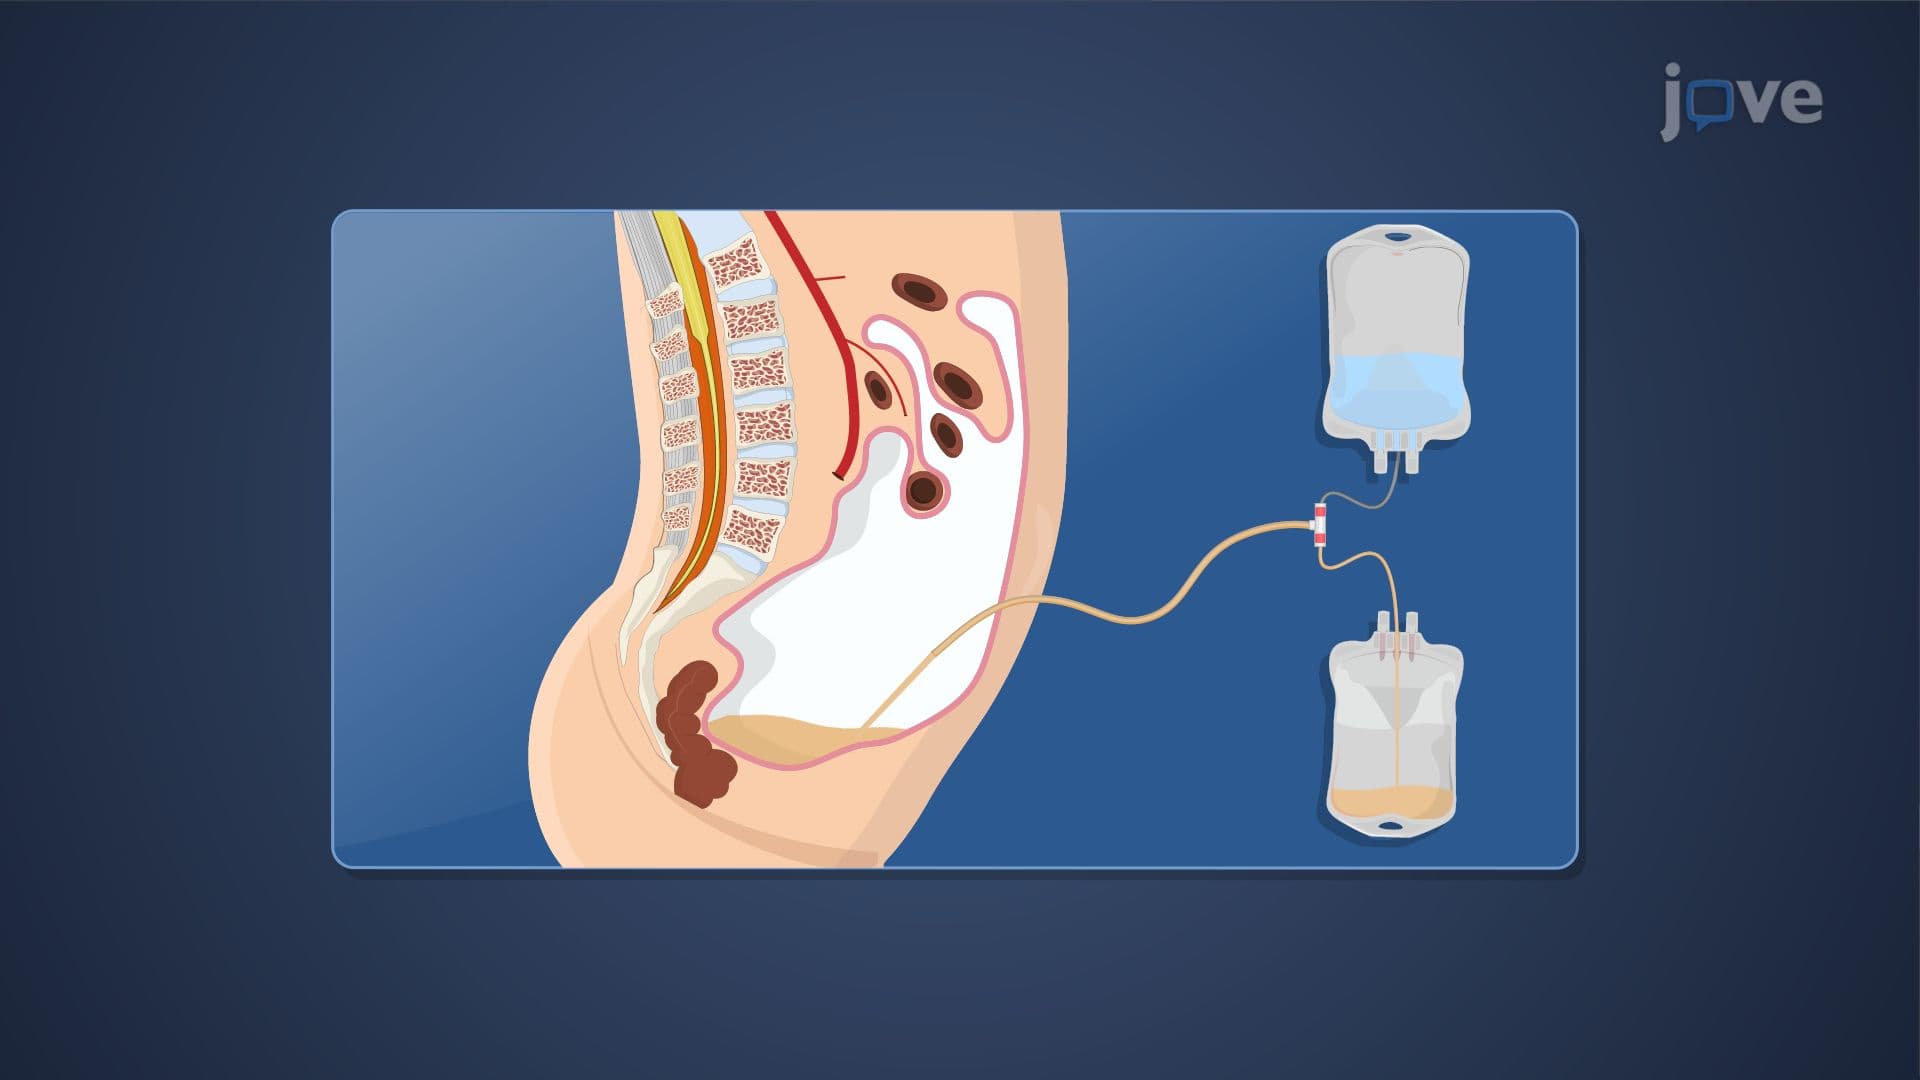 01:30
Extracorporeal Removal of Drugs: Peritoneal Dialysis and Hemodialysis
 01:24
Hemodialysis II: Procedure and Complications