Related Experiment Video
Updated: May 5, 2026


A Method for Mouse Pancreatic Islet Isolation and Intracellular cAMP Determination
Published on: June 25, 2014
Faecal elastase 1: not helpful in diagnosing chronic pancreatitis associated with mild to moderate exocrine
P G Lankisch1, I Schmidt, H König
1Department of Internal Medicine, Municipal Hospital of Lüneburg, Germany.

Background/Aim:
The suggestion that estimation of faecal elastase 1 is a valuable new tubeless pancreatic function test was evaluated by comparing it with faecal chymotrypsin estimation in patients categorised according to grades of exocrine pancreatic insufficiency (EPI) based on the gold standard tests, the secretin-pancreozymin test (SPT) and faecal fat analysis.
Methods:
In 64 patients in whom EPI was suspected, the following tests were performed: SPT, faecal fat analysis, faecal chymotrypsin estimation, faecal elastase 1 estimation. EPI was graded according to the results of the SPT and faecal fat analysis as absent, mild, moderate, or severe. The upper limit of normal for faecal elastase 1 was taken as 200 micrograms/g, and for faecal chymotrypsin 3 U/g stool. Levels between 3 and 6 U/g stool for faecal chymotrypsin are usually considered to be suspicious for EPI. In this study, both 3 and 6 U/g stool were evaluated as the upper limit of normal.
Results:
Exocrine pancreatic function was normal in 34 patients, of whom 94, 91, and 79% had normal faecal elastase 1 and faecal chymotrypsin levels (< 3 U/g and < 6 U/g) respectively. Thirty patients had EPI, of whom 53, 37, and 57% had abnormal faecal enzyme levels (differences not significant). When EPI was graded as mild, moderate, or severe, 63% of patients had mild to moderate EPI, and 37% had severe EPI. In the latter group, between 73 and 91% of patients had abnormal faecal enzymes. In the group with mild to moderate EPI, abnormal test results were obtained for both faecal enzymes in less than 50% of the patients (differences not significant). Some 40% of the patients had pancreatic calcifications. There were no significant differences for either faecal enzyme between the two groups with and without pancreatic calcifications. In 62% of the patients who underwent an endoscopic retrograde cholangiopancreatography (ERCP), abnormal duct changes were found. Again, there were no significant differences for either faecal enzyme between the two groups with abnormal and normal ERCP.
Conclusion:
Estimation of faecal elastase 1 is not distinctly superior to the traditional faecal chymotrypsin estimation. The former is particularly helpful only in detecting severe EPI, but not the mild to moderate form, which poses the more frequent and difficult clinical problem and does not correlate significantly with the severe morphological changes seen in chronic pancreatitis.


Related Concept Videos
 01:27
Acute Pancreatitis I: Introduction
Acute pancreatitis is characterized by rapid inflammation of the pancreas, often caused by factors like gallstone blockage or excessive alcohol consumption. Chronic pancreatitis, on the other hand, is a slow, progressive inflammation that may result from long-term alcohol abuse, obstructions in the pancreatic duct, or genetic factors.
The causes of acute pancreatitis include:
 01:24
Chronic Pancreatitis I: Introduction
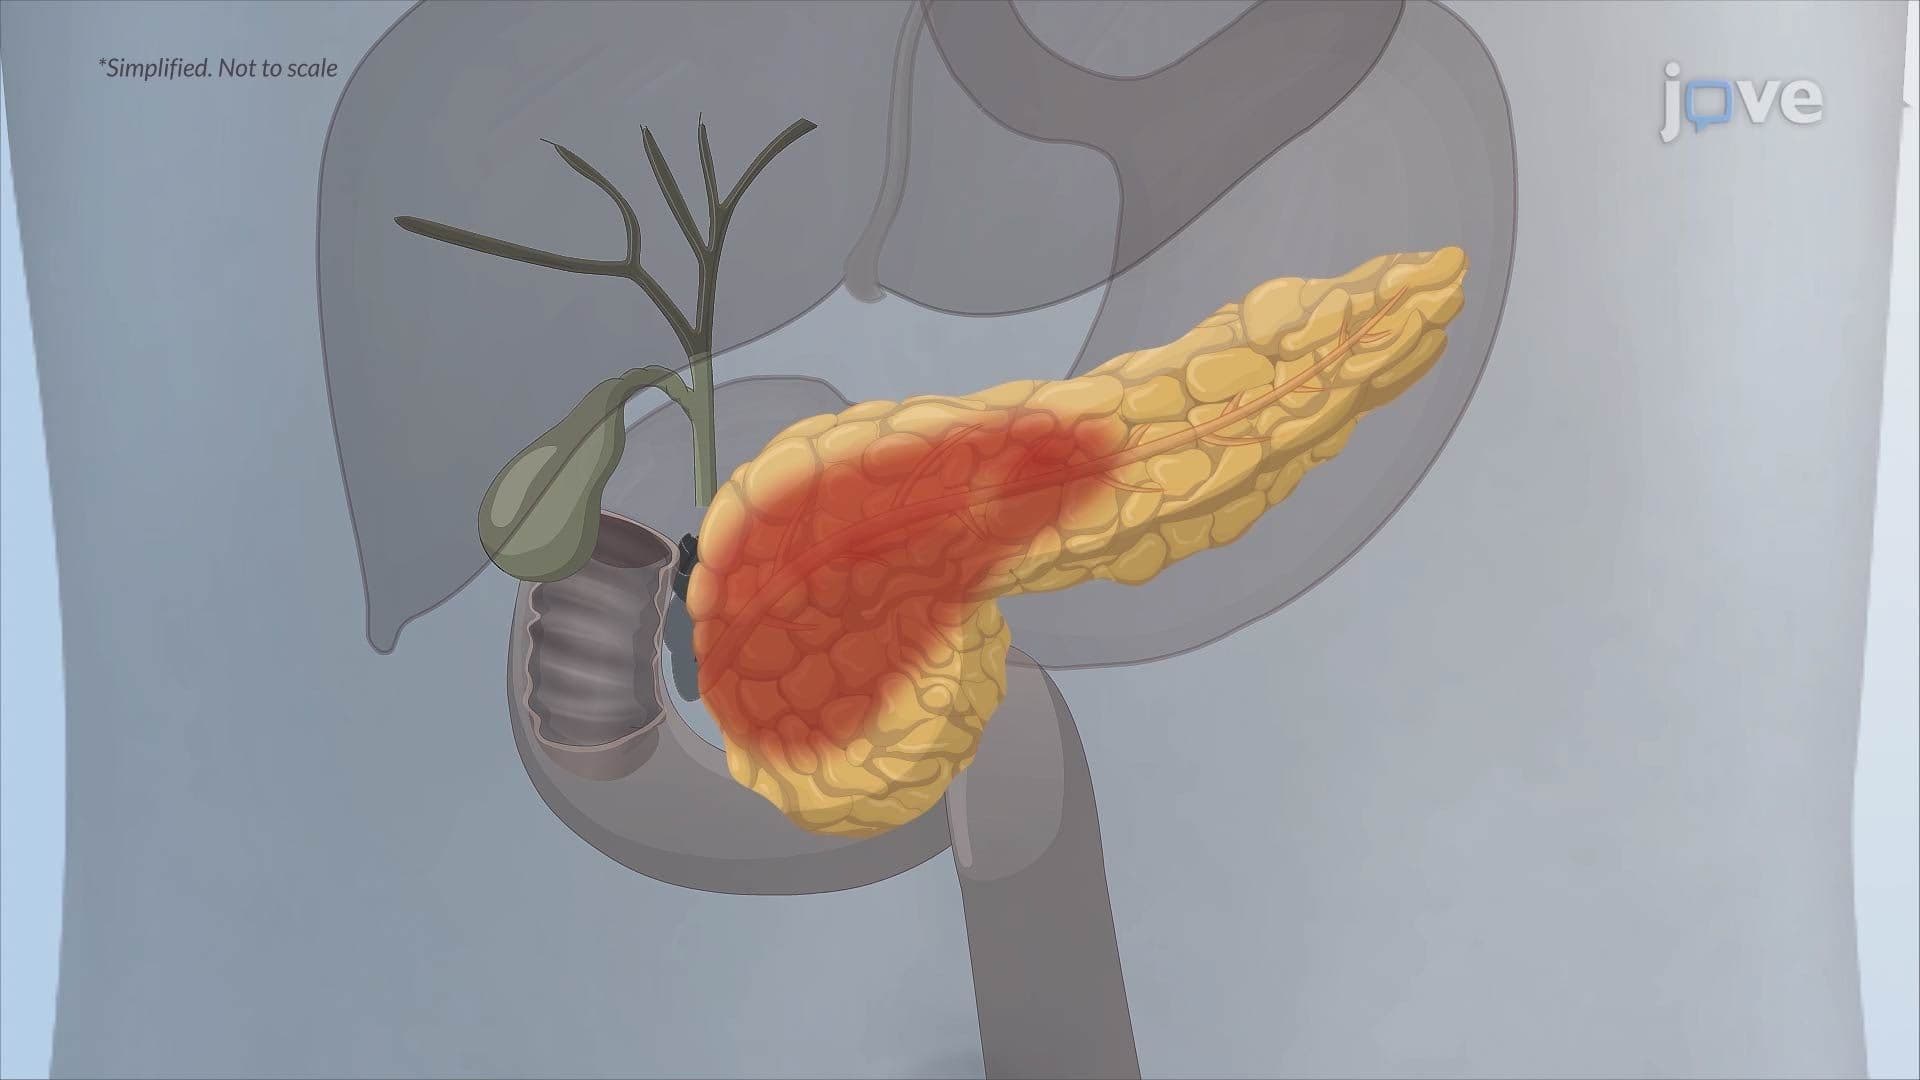
Pancreatitis is the inflammation of the pancreas, which occurs when the immune system becomes active and causes swelling, pain, and disruptions in organ function. Pancreatitis can manifest as either an acute or chronic condition.
Acute pancreatitis arises suddenly and lasts for a brief duration, while chronic pancreatitis is a long-term affliction...
 01:29
Chronic Pancreatitis II: Collaborative Care
Assessment:
 01:25
Ultrasound II: Endoscopic Ultrasound and FibroScan
Endoscopic Ultrasound (EUS):
 01:25
Acute Pancreatitis I: Introduction
 01:25
Chronic Pancreatitis I: Introduction