Related Experiment Video
Updated: Aug 11, 2026
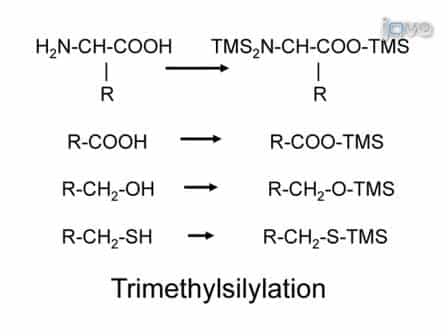
One-step Metabolomics: Carbohydrates, Organic and Amino Acids Quantified in a Single Procedure
Published on: June 25, 2010
Cobalamin (vitamin B12) and holotranscobalamin changes in plasma and liver tissue in alcoholics with liver disease
H Baker1, C B Leevy, B DeAngelis
1Department of Preventive Medicine and Community Health, University of Medicine and Dentistry, New Jersey Medical School, Newark 07107-3001, USA.

Objective:
We wanted to know if alterations in plasma cobalamin (B12) concentration and B12 carriers, e.g., holotranscobalamins (holo TC), occur in blood and liver tissue from patients with severe alcoholic liver disease. Our purpose was to test the hypothesis that liver disease may disrupt B12 distribution.
Method:
Total B12, as well as B12 bound to transcobalamin I, II, III (holo TC), were measured to determine their concentration in plasma and in liver tissue; Poteriochromonas malhamensis--a protozoan reagent served to measure only metabolically active (true) B12. Total B12 as distributed in holo TC in plasma and liver tissue of healthy subjects (controls) were compared to patients with severe alcoholic liver disease.
Results:
Severe liver disease initiates highly elevated B12 levels in plasma and a lowered liver tissue total B12 concentration. The percent of B12 distributed to holo TC II is significantly depleted during liver disease. In contrast, holo TC I and III are elevated in plasma during liver disease and contain more B12 than controls. Total B12 and B12 distributed to TC are lower in diseased liver tissue.
Conclusion:
Severe alcoholic liver disease involves leakage of total B12 from liver tissue into the plasma. Holo TC I and III concentration increases in plasma; this preserves the high plasma B12 from being excreted. However, plasma holo TC II B12 distribution is decreased, indicating that there is a depression of exogenous B12 entering the plasma and tissues. In severe liver disease, liver tissue B12 binding and storage by TC is disrupted and causes B12 to leak out of the liver into the circulation. Eventually liver disease could produce enough severe tissue B12 deficits to cause metabolic dysfunction despite elevated plasma total B12. Elevation of plasma B12, accompanied by a lowering of holo TC II distribution, seemed to be a useful index of liver disease severity suggesting preventive treatment.
More Related Videos
 03:19
Modifying Levels of Maternal Dietary Folic Acid or Choline to Study the Impact of Deficiencies on Offspring Health Outcomes
Published on: June 28, 2024
 08:37
Assessment of Glutamine as a Fuel Source for Alveolar Macrophages Exposed to Chronic Ethanol Using an Extracellular Flux Bioanalyzer
Published on: November 15, 2024
Related Concept Videos
 01:30
Liver Physiology
Metabolic Regulation:
The liver is the central organ involved in regulating blood composition. It stabilizes blood glucose levels, maintaining them within the range of 70–110 mg/dL. When these levels drop, the liver breaks down glycogen reserves and releases glucose into the bloodstream. It can also...
 01:26
Effect of Hepatic Disease on Pharmacokinetics: Drug Dosing and Hepatic Blood Flow
 01:14
Effect of Hepatic Disease on Pharmacokinetics: Active Drug, Metabolite and Fraction of Metabolized Drug
 01:22
Effect of Hepatic Disease on Pharmacokinetics: Pathophysiologic Assessment and Liver Function Test
 01:08
Effect of Hepatic Disease on Pharmacokinetics: Dose Adjustments Due to Hepatic Impairment
 01:24
Cirrhosis II: Pathophysiology