
Determinants of vancomycin clearance by continuous venovenous hemofiltration and continuous venovenous hemodialysis
M S Joy1, G R Matzke, R F Frye
1Division of Nephrology and Hypertension, University of North Carolina, School of Medicine, Chapel Hill, USA.

Abstract:
The clearance of vancomycin is significantly reduced in patients with acute, as well as, chronic renal failure. Although multiple-dosage regimen adjustment techniques have been proposed for these patients, there is little quantitative data to guide the individualization of vancomycin therapy in acute renal failure patients who are receiving continuous renal replacement therapy (CRRT). To determine appropriate vancomycin dosing strategies for patients receiving continuous venovenous hemofiltration (CVVH) and continuous venovenous hemodialysis (CVVHD), we performed controlled clearance studies in five stable hemodialysis patients with three hemofilters: an acrylonitrile copolymer 0.6 m2 (AN69), polymethylmethacrylate 2.1 m2 (PMMA), and polysulfone 0.65 m2 (PS). Patients received 500 mg of vancomycin intravenously at least 12 hours before the start of the clearance study. The concentration of vancomycin in multiple plasma and dialysate/ultrafiltrate samples was determined by EMIT (Syva, Palo Alto, CA). The diffusional clearance and sieving coefficient (SC) of vancomycin were compared by a mixed-model repeated-measures analysis of variance (ANOVA) with filter and blood (Q(B)), dialysate inflow (Q(DI)), or ultrafiltration rate (Q(UF)) as the main effects and patient as a random effect. Vancomycin was moderately protein bound in these patients; free fraction ranged from 49% to 83%. The SCs of the three filters were similar and significantly correlated with the free fraction of vancomycin (P = 0.01; r2 = 0.465). Significant linear relationships were observed between the diffusional clearance of vancomycin and Q(DI) for all three filters: AN69 (slope = 0.482; r2 = 0.880); PMMA (slope = 0.853; r2 = 0.966); and PS (slope = 0.658; r2 = 0.887). The slope of this relationship for the PMMA filter was significantly greater than that of the AN69 and PS filters. The clearance of vancomycin, urea, and creatinine, however, was essentially constant at all Q(B)s for all three filters. Thus, the clearance of vancomycin was not membrane dependent during CVVH. However, during CVVHD, membrane dependence of vancomycin clearance was noted at a Q(DI) greater than 16.7 mL/min; vancomycin clearance with PMMA at a Q(DI) of 25 mL/min was 66% and 43% greater than that with the AN69 and PS filters, respectively. CVVH (62% to 262%) and CVVHD (90% to 540%) can significantly augment the clearance of vancomycin in acute renal failure patients. Dosing strategies for individualization of vancomycin therapy in patients receiving CVVH and CVVHD are proposed.
Related Concept Videos
 01:31
Factors Affecting Renal Clearance: Drug's Physicochemical Properties and Plasma Levels
One important factor is the drug's molecular size. The kidneys readily excrete smaller molecules below 300 Daltons (Da). On the other hand, molecules weighing between 300 and 500 Da are excreted through both urine and bile. Larger molecules above 500 Da tend to be excreted less...
 01:15
Determination of Multiple Dosing Parameters: Steady-State, Minimum and Maximum Concentrations
 01:20
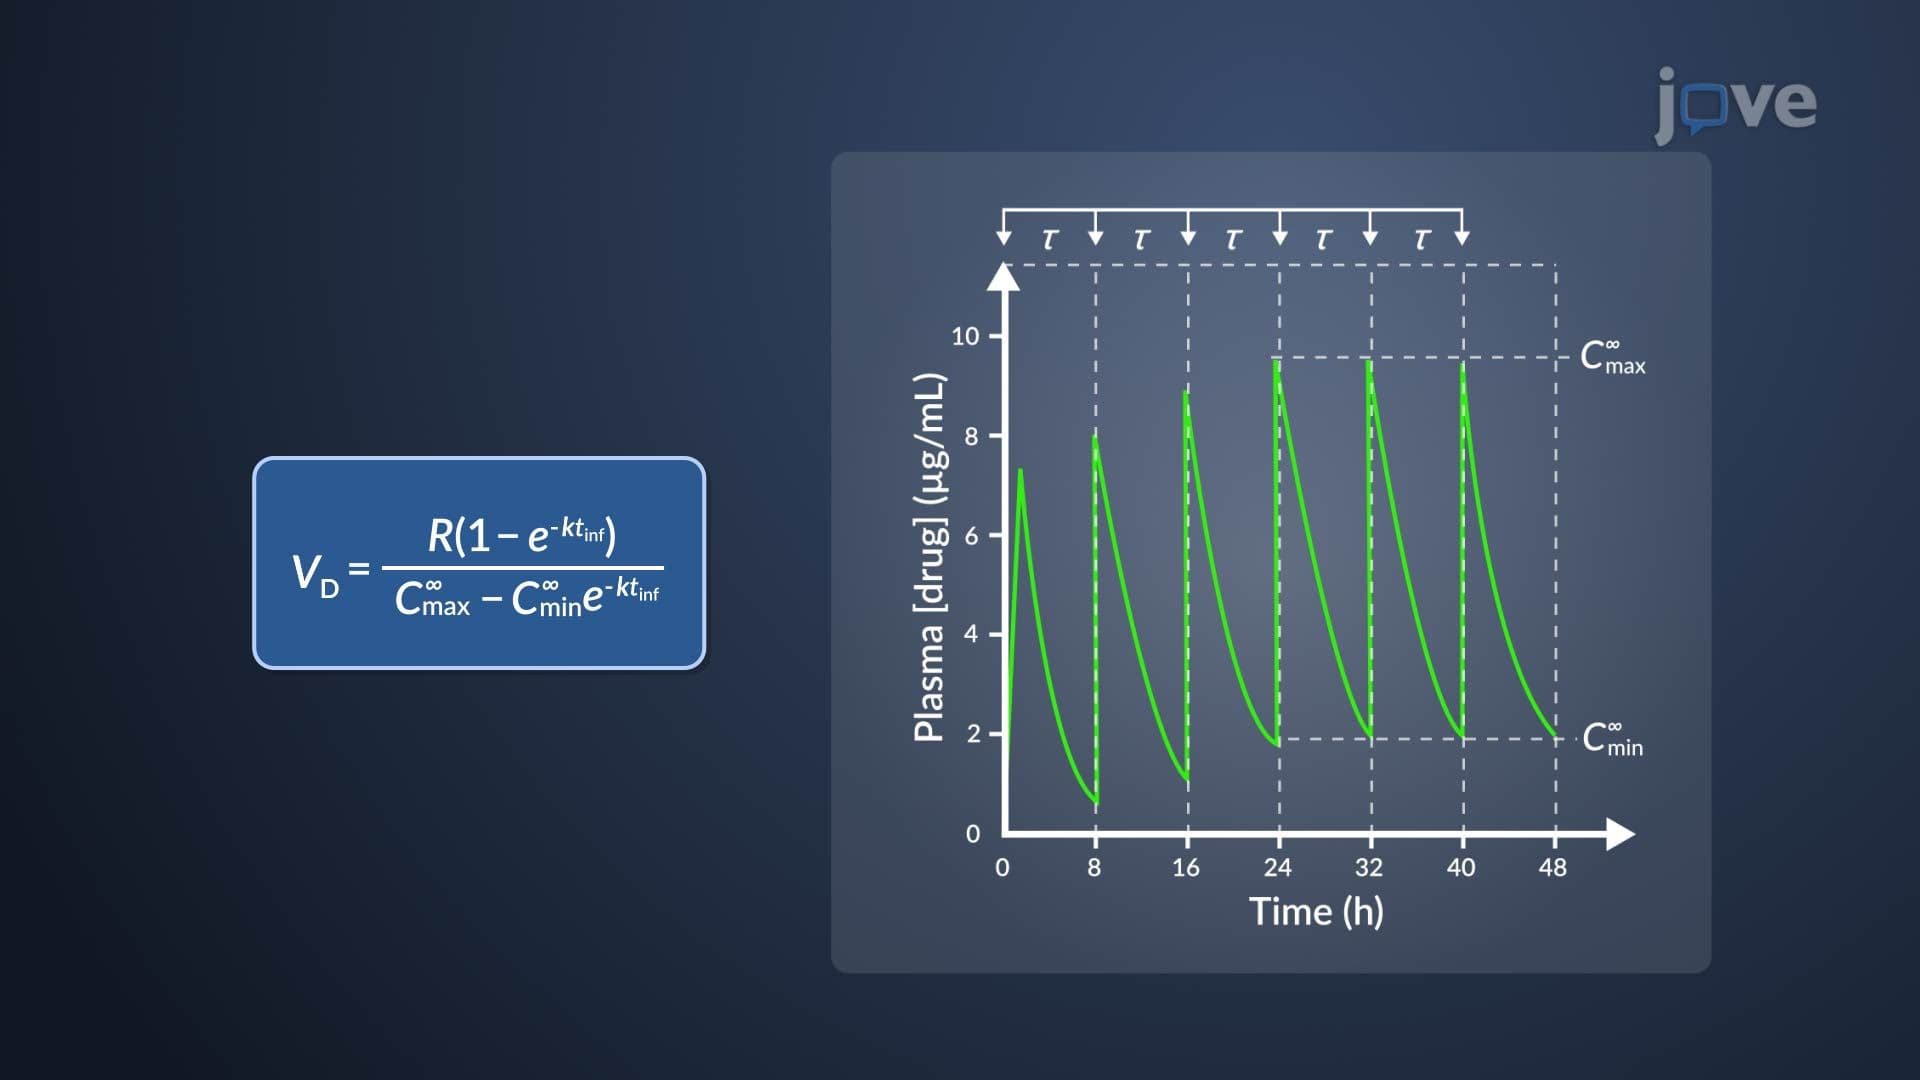
Estimation of k and VD of Aminoglycosides
 01:25
Drug Dosing in Renal Diseases: Dose Adjustments Based on Drug Clearance and Elimination Rate Constant
 01:26
Extracorporeal Removal of Drugs: Continuous Renal Replacement Therapy
 01:30
Continuous Renal Replacement Therapy