Surgical treatment of severe duodenal polyposis in familial adenomatous polyposis
Related Experiment Video
Updated: Aug 12, 2026
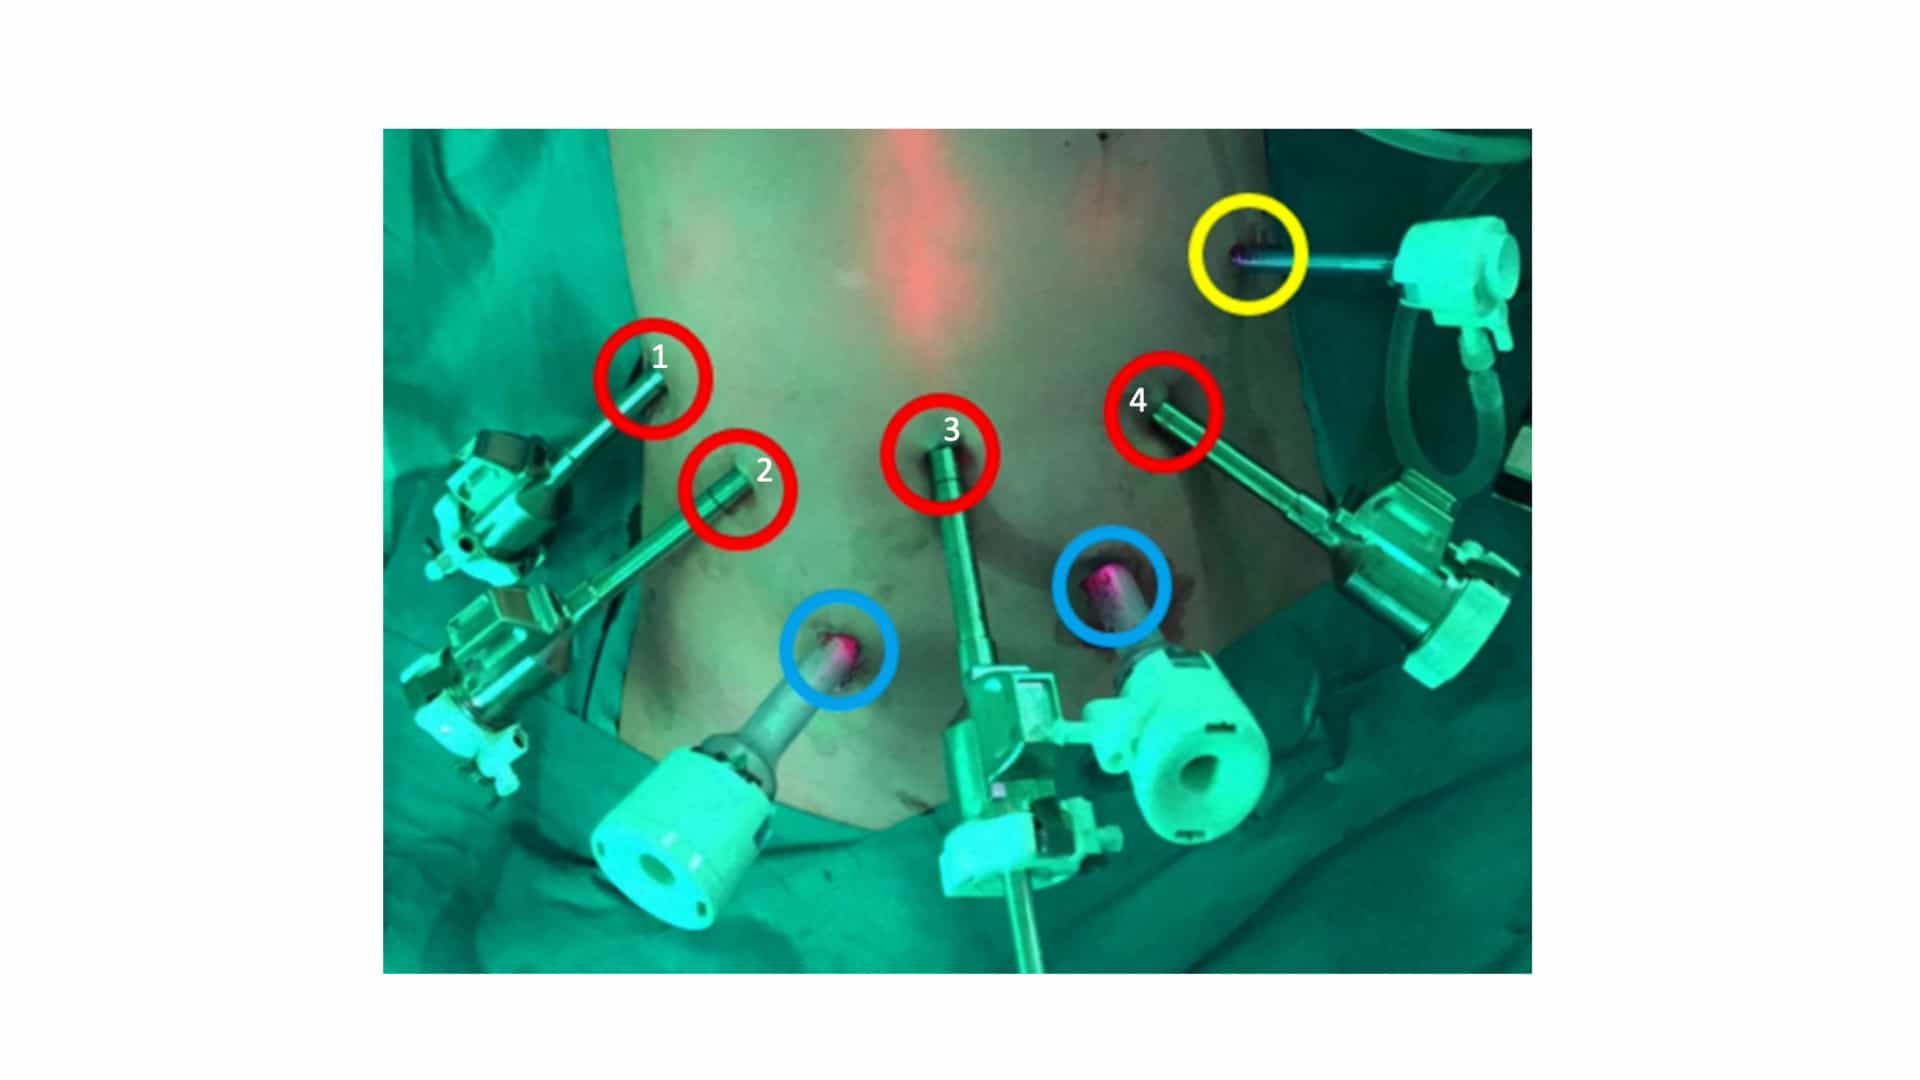
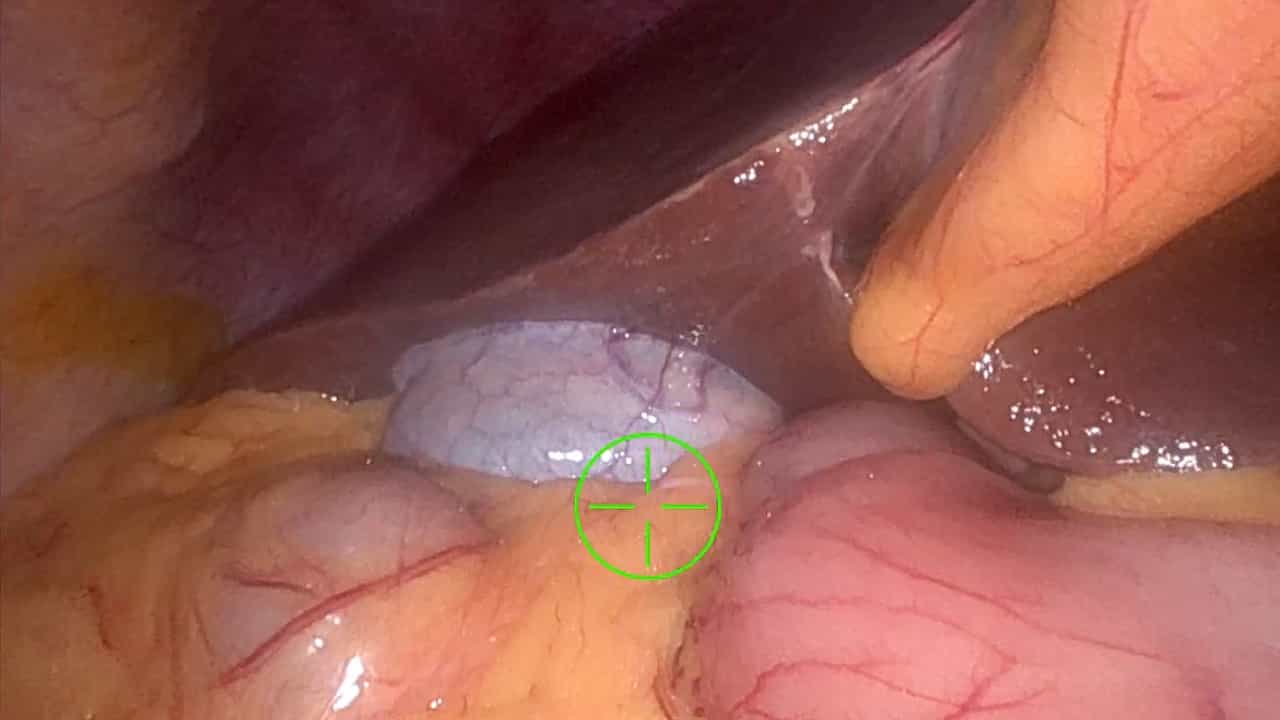
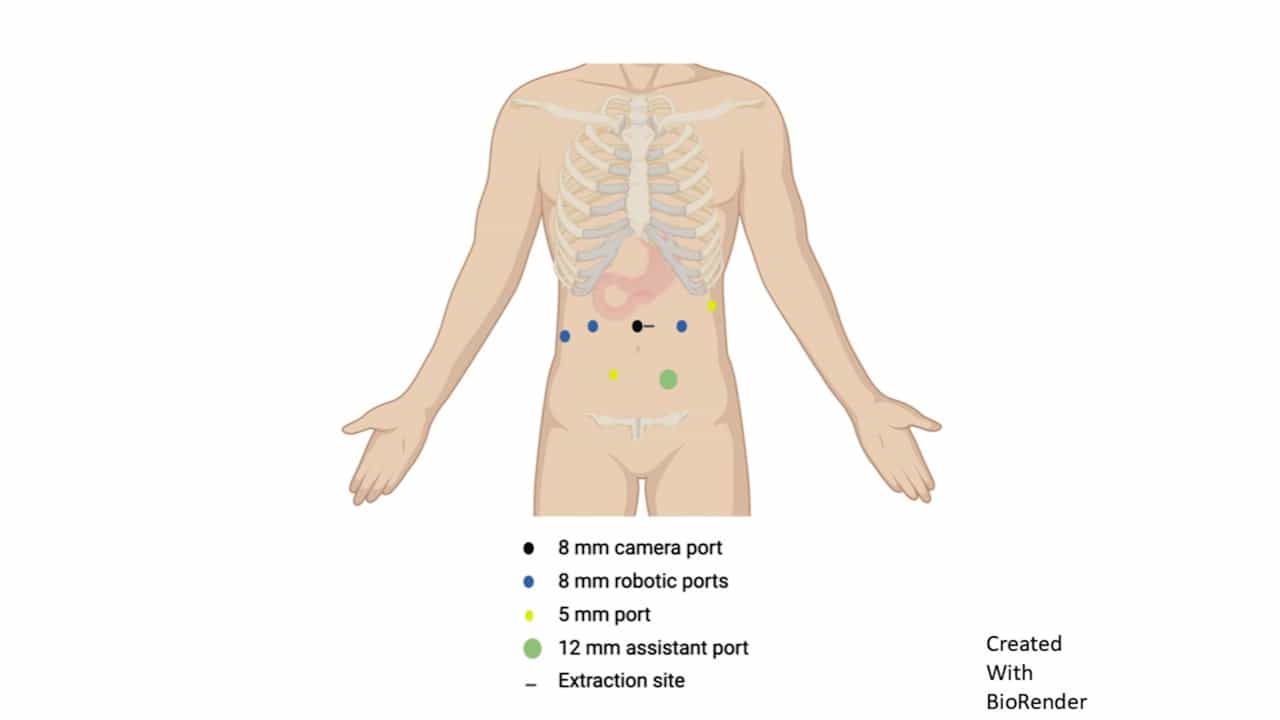
Robotic D3 Partial Duodenal Resection with Primary Side-to-Side Anastomosis
Published on: December 15, 2023
C Penna1, N Bataille, P Balladur
1Department of Digestive Surgery, Hôpital Saint-Antoine, Paris, France.

Background:
Patients with familial adenomatous polyposis (FAP) are at risk for adenomas and cancers in the duodenum but the ideal management of duodenal polyposis remains uncertain.
Methods:
The outcome of surgical resection was analysed in 18 patients with FAP who had severe duodenal polyposis.
Results:
Duodenotomy and clearance of duodenal adenomas was performed seven times in six patients. There were two duodenal leaks and, after a mean follow-up of 53 (range 36-72) months, duodenal adenomas recurred in all patients and five had severe polyposis. Pancreatoduodenectomy was performed in seven patients with severe duodenal polyposis. Histology of the specimens revealed two unsuspected duodenal carcinomas at an early stage. After a mean follow-up of 42 months all patients were alive and well, and there was no case of jejunal polyposis. Pancreatoduodenectomy was attempted in five patients with duodenal cancer and only one survived more than 4 years.
Conclusion:
Surgical excision of duodenal adenomas should be discussed before carcinoma occurs. Surgical polypectomy fails to guarantee a polyp-free duodenum and carries a risk of postoperative complications whereas pancreatoduodenectomy eliminates the risk of duodenal cancer with an acceptable morbidity rate. Pancreatoduodenectomy could be offered to some patients with large or multiple villous duodenal adenomas repeatedly showing severe dysplasia.
More Related Videos
Related Concept Videos
 01:21
Inflammatory Bowel Disease V: Surgical Management
Here are some common surgical interventions for IBD:
 01:25
Peptic Ulcer Disease V: Surgical Management and Nursing Care
Surgical Interventions for Peptic Ulcer Disease