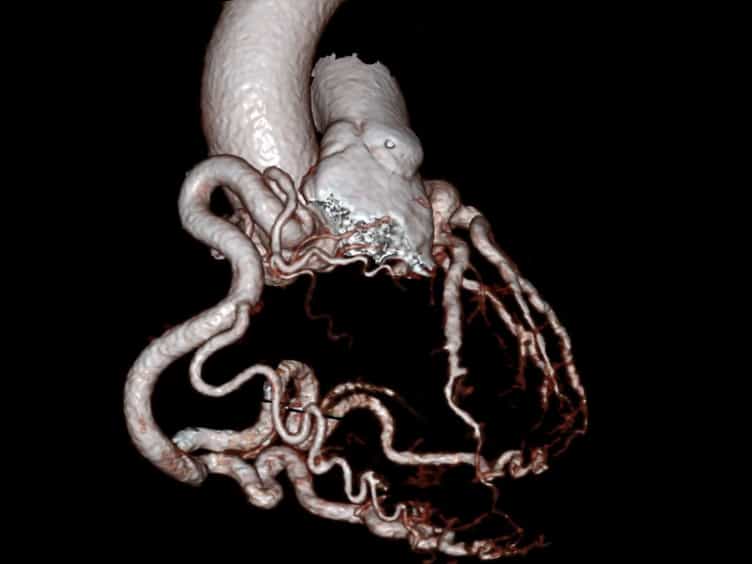
A no-touch technique for calcified ascending aorta during coronary artery surgery
Related Experiment Video
Updated: Oct 29, 2026
Novel and Innovative Hybrid Technique for Type A Aortic Dissection
Published on: March 28, 2025
B Akpinar1, M Güden, I Sanisoğlu
1Department of Cardiovascular Surgery, Florence Nightingale Hospital, Istanbul, Turkey.

Insights
This study introduces a novel cardiac surgery technique using moderate hypothermic fibrillatory arrest to reduce stroke risk. The method avoids aortic manipulation, offering effective myocardial revascularization and minimizing neurologic complications.
Area of Science:
- Cardiovascular Surgery
- Neurology
- Vascular Surgery
Background:
- Neurologic complications, including stroke, remain a significant risk after coronary artery surgery.
- Existing cardiovascular surgery techniques have not effectively reduced the incidence of these devastating complications.
Purpose of the Study:
- To describe a moderate hypothermic fibrillatory arrest technique.
- To evaluate its efficacy in reducing cerebrovascular accidents in patients with heavily calcified aortas.
Main Methods:
- A technique involving moderate hypothermic fibrillatory arrest was employed, avoiding aortic cross-clamping.
- Internal thoracic arteries and the right gastroepiploic artery were used for revascularization.
- The technique was applied to 21 patients with severe ascending aorta calcification over a 1-year period.
Main Results:
- No hemodynamic problems, lower-limb ischemia, or neurologic complications were observed in the patient cohort.
- Only one patient required reoperation for bleeding.
- One patient with incomplete revascularization showed elevated myocardial creatine kinase MB isoenzyme and a new Q wave, but no hemodynamic deterioration.
Conclusions:
- The described technique provides effective myocardial protection and revascularization.
- It appears to significantly reduce the risk of neurologic complications, such as stroke, in high-risk patients.
Abstract:
Despite improvements in cardiovascular surgery techniques over the years, the incidence of neurologic complications has not declined, and stroke remains a possible (and devastating) sequela to coronary artery surgery. In this report, we describe a moderate hypothermic fibrillatory arrest technique that avoids cross-clamping or otherwise touching the aorta; use of the internal thoracic arteries and the right gastroepiploic artery provides optimum revascularization and minimizes the risk of cerebrovascular accident. Over a 1-year period, we used the technique in 21 patients who had heavy calcifications of the ascending aorta. No hemodynamic problems, lower-limb ischemia, or neurologic complications were seen. Only 1 patient underwent reoperation (for bleeding), and another--whose revascularization was incomplete--had a high postoperative level of myocardial creatine kinase MB isoenzyme and a new Q wave, but no hemodynamic deterioration. This technique seems reasonable, because it appears to provide good myocardial protection and to reduce neurologic complications, without comprising myocardial revascularization.