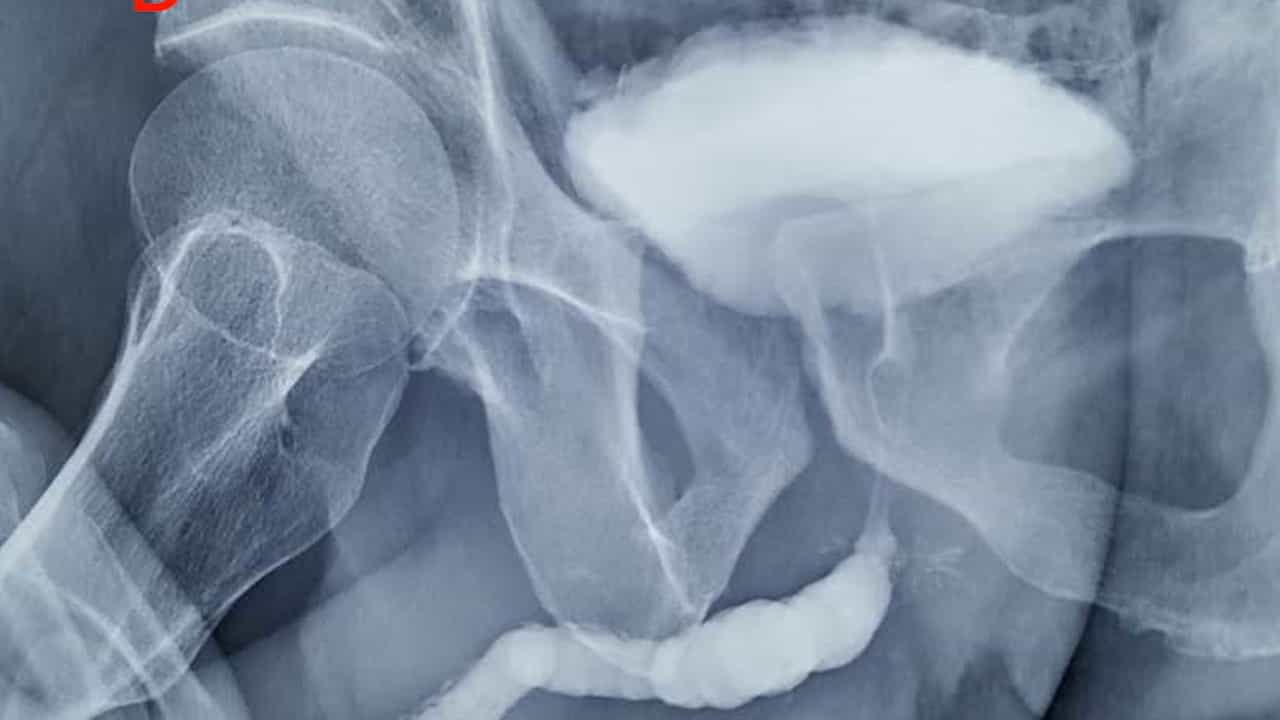
Relapse of Wegener's granulomatosis presenting as a destructive urethritis and penile ulceration

D G Ebo1, A V Mertens, L S De Clerck

  • 1Department of Immunology, Allergy and Rheumatology, University of Antwerp (UIA), Antwerpen, Belgium.

Clinical Rheumatology
|August 7, 1998
PubMed

Related Concept Videos

Peptic Ulcer Disease I: Introduction01:30

Peptic Ulcer Disease I: Introduction

Peptic Ulcer Disease (PUD) is characterized by mucosal excavation in the esophagus, stomach, pylorus, or duodenum. It can manifest as acute or chronic based on the extent and duration of mucosal involvement.
An acute ulcer, marked by superficial erosion and minimal inflammation, swiftly resolves upon identifying and addressing the underlying cause. In contrast, a chronic ulcer persists, potentially eroding through the muscular wall and forming fibrous tissue.
Peptic ulcers can also be...
Endocarditis II: Clinical Features of Infective Endocarditis01:25

Endocarditis II: Clinical Features of Infective Endocarditis

Endocarditis can present various clinical features depending on the causative organism and the patient's underlying health conditions. Initially, the clinical features of infective endocarditis develop gradually, presenting with nonspecific symptoms that can be easily mistaken for other illnesses.General SymptomsEarly symptoms of infective endocarditis are fever, chills, weakness, malaise, fatigue, and weight loss. These symptoms reflect the systemic nature of the infection and the body's...
Urinary Tract Infection II: Pathophysiology01:25

Urinary Tract Infection II: Pathophysiology

The pathophysiology of urinary tract infections (UTIs) encompasses several progressive stages, beginning with bacterial colonization and culminating in potential systemic complications if untreated. UTIs are primarily initiated by bacteria, such as Escherichia coli, which often originate from the gastrointestinal tract and migrate to the urinary system through the periurethral area. This migration can occur via several routes, including improper hygiene practices, sexual activity, or...
Peptic Ulcer01:27

Peptic Ulcer

Peptic ulcers are erosive lesions of the gastric or duodenal lining, most commonly caused by Helicobacter pylori infection. This Gram-negative, helical bacterium has adapted to survive the stomach’s acidic environment by producing urease, which converts urea into ammonia and carbon dioxide. The ammonia neutralizes gastric acid in the bacterium’s immediate environment, allowing colonization of the gastric mucosa. H. pylori attaches to mucus-secreting epithelial cells, penetrates the mucus...
Gastritis II: Pathophysiology01:26

Gastritis II: Pathophysiology

The pathophysiology of gastritis begins with the colonization of the stomach lining by Helicobacter pylori (H. pylori). This bacterium spreads mainly via the oral-oral route through saliva or shared utensils, and can also be transmitted in overcrowded or unhygienic environments through contaminated water, despite its brief survival outside the body.ColonizationOnce ingested, H. pylori enters the stomach and begins colonization by navigating through the mucus layer lining the stomach wall. It...
Peptic Ulcer Disease III: Clinical Manifestations and Complications01:25

Peptic Ulcer Disease III: Clinical Manifestations and Complications

Duodenal UlcersDuodenal ulcers are the most common form of peptic ulcer disease, presenting with chronic, intermittent epigastric pain. Pain typically appears 2–3 hours after meals, especially when the stomach is empty, often waking patients at night. It is characteristically relieved by food or antacids (“pain–food–relief”). Some patients remain asymptomatic until complications like bleeding or perforation emerge, particularly with NSAID or anticoagulant use.Gastric UlcersGastric ulcers share...