Related Experiment Video
Updated: Oct 13, 2026

Early Detection of Drug-Induced Renal Hemodynamic Dysfunction Using Sonographic Technology in Rats
Published on: March 11, 2016
Successful treatment of cisplatin-induced hemolytic uremic syndrome with therapeutic plasma exchange
J Palmisano1, M Agraharkar, A A Kaplan
1Division of Nephrology, University of Connecticut Health Center, Farmington 06030, USA. palmisano@nso.uchc.edu

Cisplatin is a known cause of hemolytic uremic syndrome (HUS). The acute, fulminant form of cisplatin-induced HUS is almost always fatal. We present a 67-year-old Hispanic woman who was treated with cisplatin for squamous cell carcinoma of the tongue. Three days after receiving the treatment, she presented with increasing fatigue, decreased urine output, and confusion. Physical examination was remarkable for tachycardia of 130 beats/min, peripheral edema, and mental obtundation. Laboratory investigations showed a white cell count of 5,500/microL, hemoglobin level of 9.6 g/dL, hematocrit of 29.6%, and platelet count of 13,000/microL. Schistocytes were present on peripheral smear. Screening for disseminated intravascular coagulation was negative. Serum chemistry values included blood urea nitrogen 111 mg/dL, creatinine 3.8 mg/dL, and lactate dehydrogenase (LDH) 927 IU. The patient underwent hemodialysis and therapeutic plasma exchange (TPE), using fresh frozen plasma (FFP). Dialysis was no longer required after the fifth day. TPE was performed daily until the platelet count normalized on the 13th day, after which intertreatment intervals were extended until normalization of LDH levels on the 50th day. We conclude that the normally fatal, fulminant form of cisplatin-induced HUS can be successfully treated with standard TPE, using FFP replacement.
Cisplatin is a known cause of hemolytic uremic syndrome (HUS). The acute, fulminant form of cisplatin-induced HUS is almost always fatal. We present a 67-year-old Hispanic woman who was treated with cisplatin for squamous cell carcinoma of the tongue. Three days after receiving the treatment, she presented with increasing fatigue, decreased urine output, and confusion. Physical examination was remarkable for tachycardia of 130 beats/min, peripheral edema, and mental obtundation. Laboratory investigations showed a white cell count of 5,500/microL, hemoglobin level of 9.6 g/dL, hematocrit of 29.6%, and platelet count of 13,000/microL. Schistocytes were present on peripheral smear. Screening for disseminated intravascular coagulation was negative. Serum chemistry values included blood urea nitrogen 111 mg/dL, creatinine 3.8 mg/dL, and lactate dehydrogenase (LDH) 927 IU. The patient underwent hemodialysis and therapeutic plasma exchange (TPE), using fresh frozen plasma (FFP). Dialysis was no longer required after the fifth day. TPE was performed daily until the platelet count normalized on the 13th day, after which intertreatment intervals were extended until normalization of LDH levels on the 50th day. We conclude that the normally fatal, fulminant form of cisplatin-induced HUS can be successfully treated with standard TPE, using FFP replacement.


Related Concept Videos
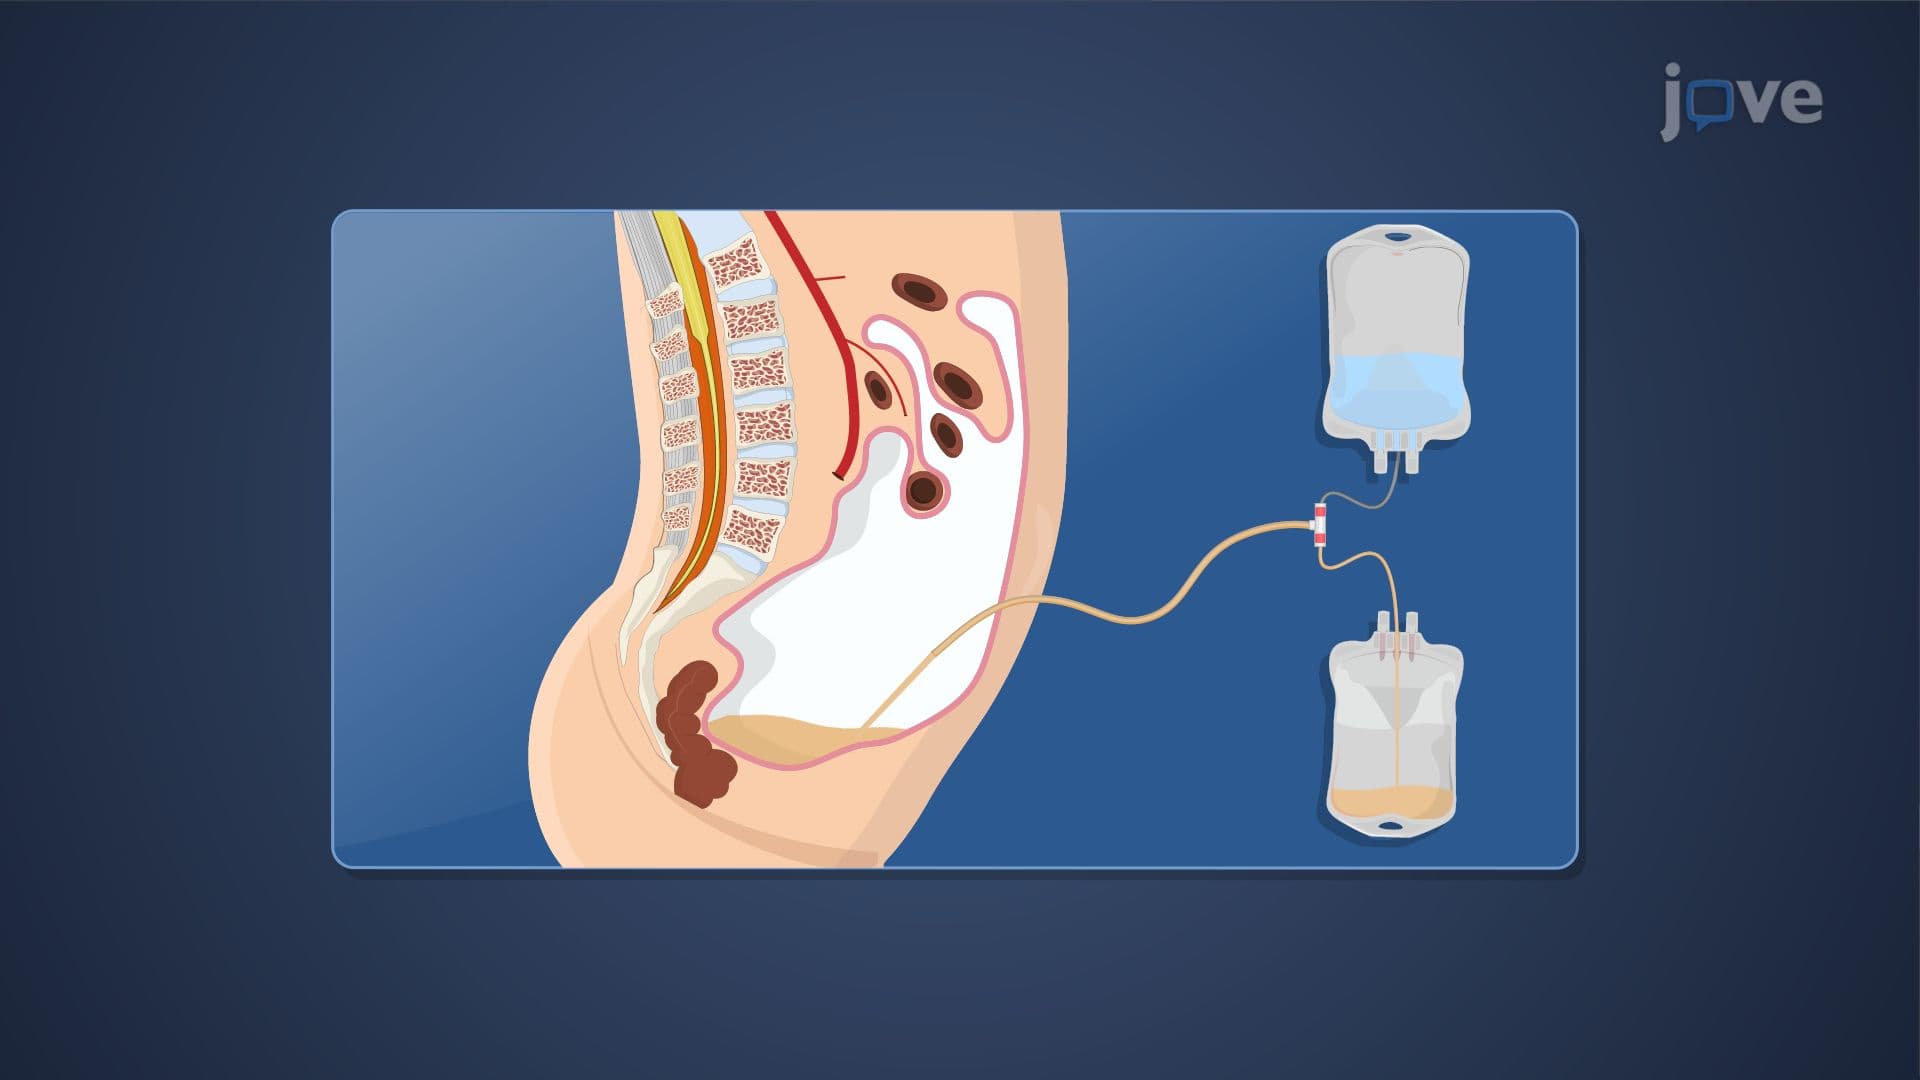 01:30
Extracorporeal Removal of Drugs: Peritoneal Dialysis and Hemodialysis
 01:25
Extracorporeal Removal of Drugs: Hemoperfusion and Hemofiltration
 01:26
Extracorporeal Removal of Drugs: Continuous Renal Replacement Therapy
 01:30
Continuous Renal Replacement Therapy
 01:26
Kidney Transplant II: Surgical Procedure