

Cardiovascular risks to young persons on the athletic field
1Minneapolis Heart Institute Foundation, Minnesota 55407, USA.

Abstract:
Sudden cardiac deaths of young athletes, which are usually associated with physical exertion, continue to achieve high public visibility and generate considerable concern. Despite broad community participation in sports, such catastrophes are uncommon, occurring in about 1/200000 high school athletes per academic year. Various unsuspected congenital cardiovascular diseases are usually responsible; the most common lesions are hypertrophic cardiomyopathy and several congenital coronary artery anomalies. Selected reports suggest that arrhythmogenic right ventricular dysplasia may be a more common cause of these deaths than previously suspected. In some trained athletes with borderline increases in thickness of the left ventricular wall, mild morphologic expression of hypertrophic cardiomyopathy can often be distinguished from the physiologic consequences of athlete's heart by noninvasive clinical assessment and testing. In addition, the recognized cardiovascular risks of the athletic field are now extended to include cardiac arrest resulting from relatively modest, nonpenetrating chest blows produced by projectiles (such as baseballs) or bodily contact in the absence of underlying cardiac disease and without structural injury to the chest wall or heart. These uncommon but usually fatal events seem to result when chest impact occurs precisely during the vulnerable phase of repolarization, and they may be reduced by use of softer baseballs. Preparticipation screening for cardiovascular disease, consisting of standard history and physical examination, is customary practice for most high school and college athletes in the United States. Evidence suggests, however, that the present screening process for cardiovascular disease in high school athletes may be largely inadequate, given the content of the approved screening questionnaires (which serve as guidelines for the process) and the use of examiners with little cardiovascular training. This emphasizes the need for national standardization of preparticipation screening. The recommendations of the 26th Bethesda Conference for disqualification from competitive athletics are now a standard for management decisions when cardiovascular abnormalities are identified in trained athletes.


Related Concept Videos
 01:30
Factors Influencing Heart Rate
Let us explore the significant factors affecting heart rate, including age, body temperature, posture, acute pain, chemical influences,...
 01:17
Exercise and Cardiac Output
Sustained exercise increases the muscles' oxygen demand, which can be...
 01:20
Exercise and Cardiovascular Response
Light to moderate physical activity initiates a series of interconnected responses in the body. The heart rate modestly increases in anticipation of the workout, followed by widespread vasodilation as oxygen consumption by skeletal muscles increases. This results in decreased peripheral resistance, increased capillary blood flow, and accelerated...
 01:23
Assessment of the Cardiovascular System I: Subjective Data
Initial Enquiry
Ask the patient about their primary concern and thoroughly explore all reported symptoms.
Medical History
Investigate past illnesses affecting the cardiovascular system, such as angina, anemia, rheumatic fever, congenital heart disease, stroke, thrombophlebitis, dysrhythmias, varicosities
Inquire about symptoms...
 01:26
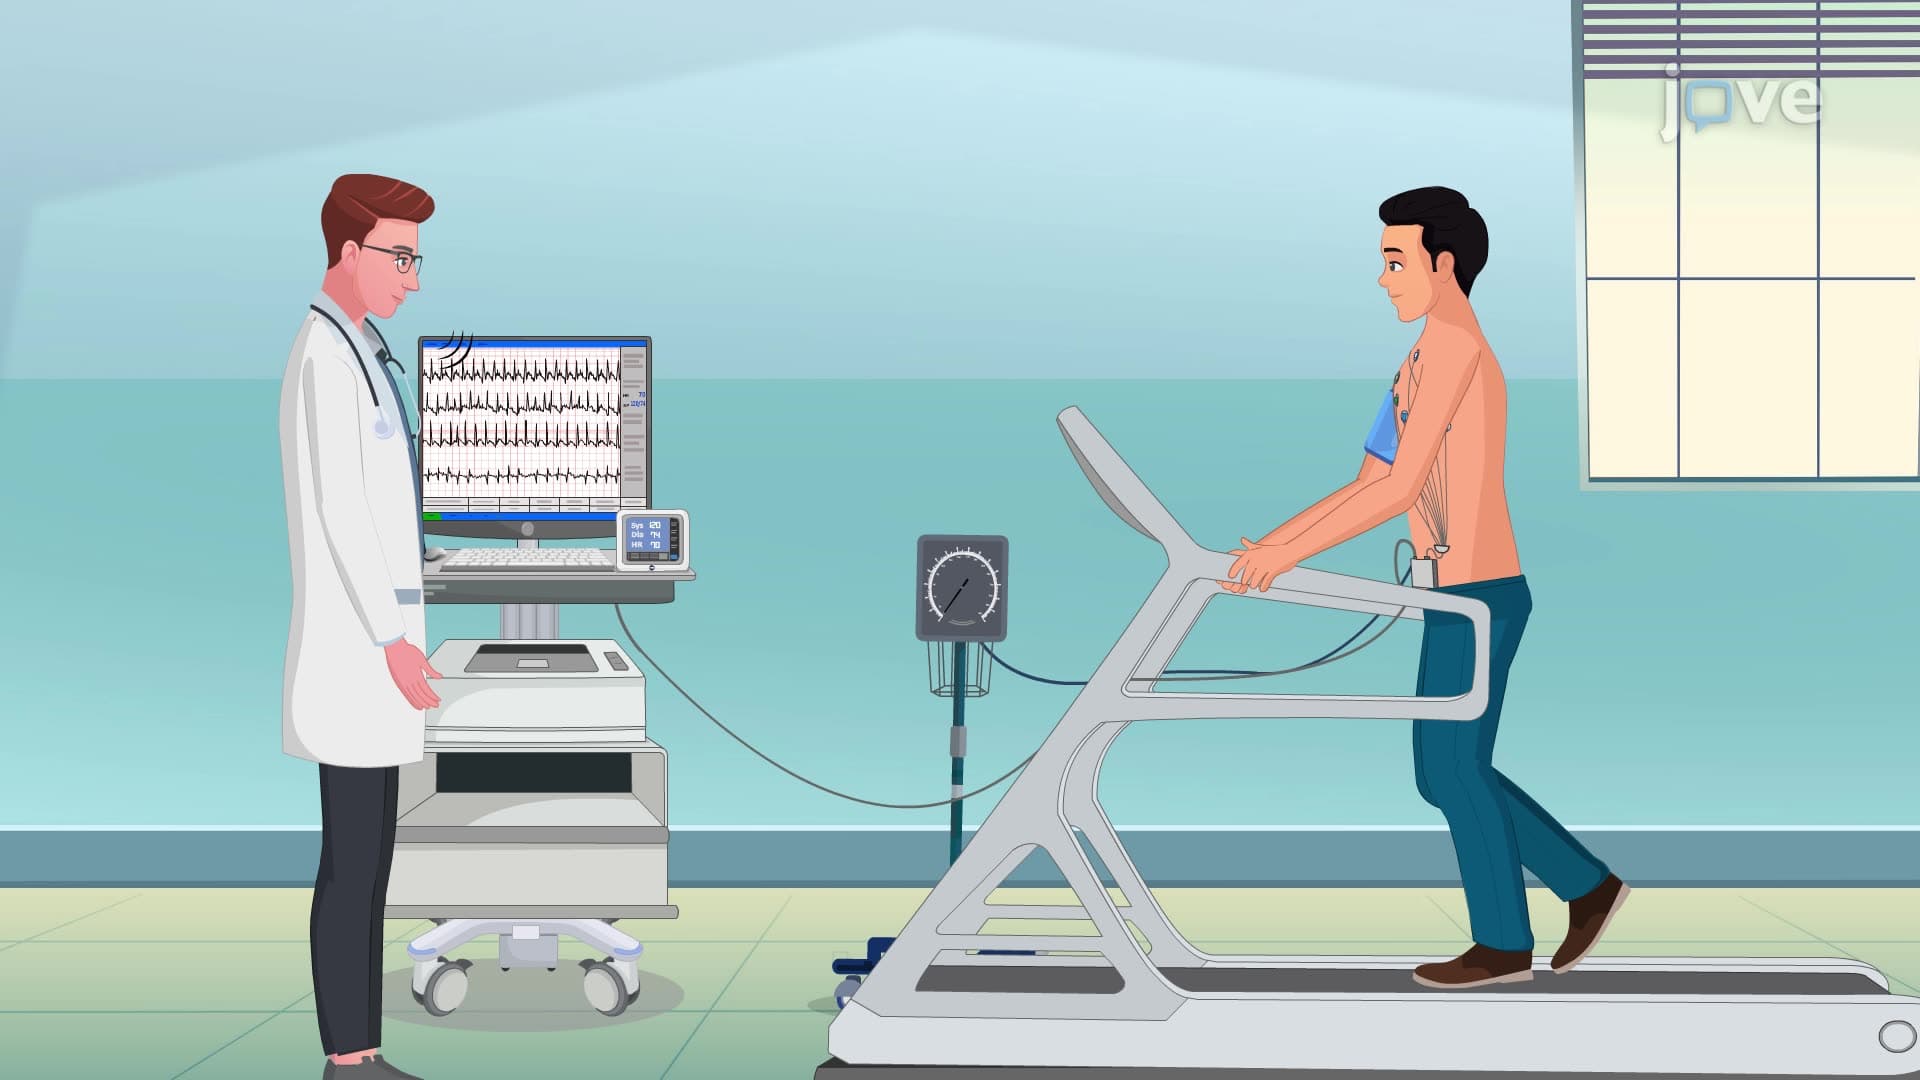
Exercise Stress Test
Exercise stress testing, commonly known as a treadmill test, is a noninvasive procedure used to evaluate cardiovascular function and diagnose heart conditions.
Definition
An exercise stress test measures the heart's response to exertion using a treadmill or stationary bicycle. Chest electrodes record the heart's electrical activity through an ECG, and blood pressure is monitored regularly.
Purposes
 01:27
Psychoneuroimmunology: Cardiovascular Disease
A key area of focus in PNI is the relationship between stress and coronary...