Related Experiment Video
Updated: Oct 28, 2026

Two Methods for Establishing Primary Human Endometrial Stromal Cells from Hysterectomy Specimens
Published on: May 23, 2014
Differential effect of exogenous human chorionic gonadotrophin on progesterone production from normal or
M Momoeda1, O Tsutsumi, Y Morita
1Department of Obstetrics and Gynecology, University of Tokyo, Japan.

Abstract:
To examine whether luteal phase defect is, in part, causally related to insufficient gonadotrophin stimulation, we compared the relation of the increment of serum progesterone concentrations in response to human chorionic gonadotrophin (HCG) with its basal level at mid-luteal phase. Thirty-eight naturally cycling infertile women aged between 27-41 years old were evaluated for hormonal responses to HCG injection at the mid-luteal phase. We measured luteinizing hormone (LH), follicle stimulating hormone (FSH), oestradiol and progesterone concentrations, before and 1, 2 and 3 h after the administration of HCG (5000 IU, i.m.) 7 days after ovulation verified by ultrasonography. Eleven out of 38 women exhibited progesterone concentrations below 10 ng/ml (low progesterone group), and those remaining showed progesterone concentrations of > or = 10 ng/ml (normal progesterone group). The basal LH, FSH and oestradiol concentrations were essentially the same in both groups. Progesterone concentrations rose significantly 1 h after the injection and levelled off thereafter. The increment of progesterone concentrations at 1 h in the normal progesterone group was 5.7 ng/ml on the average, whereas that in low progesterone group was 1.1 ng/ml. Furthermore, the percentage increase in progesterone concentrations at 1 h in the normal progesterone group was significantly greater than that in the low progesterone group. Both groups equally exhibited significant but marginal increases in oestradiol concentrations 1 h after the injection. LH and FSH concentrations at 3 h decreased significantly in both groups. In summary, HCG readily stimulates progesterone production in normally functioning corpus luteum whereas its stimulatory effect is minimal on malfunctioning corpus luteum. This suggests that luteal phase defect is not caused by inadequate gonadotrophin stimulation and, therefore, does not benefit from HCG administration.

Related Concept Videos
 01:27
Ovarian Cycle
 01:22
Hormonal Regulation of the Menstrual Cycle
At puberty, GnRH begins a pulsatile release pattern, which triggers the anterior pituitary gland to secrete follicle-stimulating hormone (FSH) and luteinizing hormone (LH). The frequency and amplitude of GnRH pulses vary across the menstrual cycle, with faster pulses favoring LH release and slower pulses favoring FSH release.
 01:24
Gonadal and Placental Hormones
In males, testosterone is the primary gonadal androgen. It plays a central role in the maturation of male reproductive organs — the penis and testes. Additionally, testosterone is instrumental in the development of secondary sexual characteristics — a deep voice as well as facial and pubic hair growth — and...
 01:30
Hormonal Control of the Ovarian Cycle
Before puberty, the hypothalamus releases GnRH in a low frequency, low amplitude pulsatile manner. This along with the immature hypothalamic-pituitary-gonadal axis activity, results in low estrogen levels and the absence of a fully functional ovarian cycle. At puberty, GnRH secretion increases in both frequency and...
 01:22
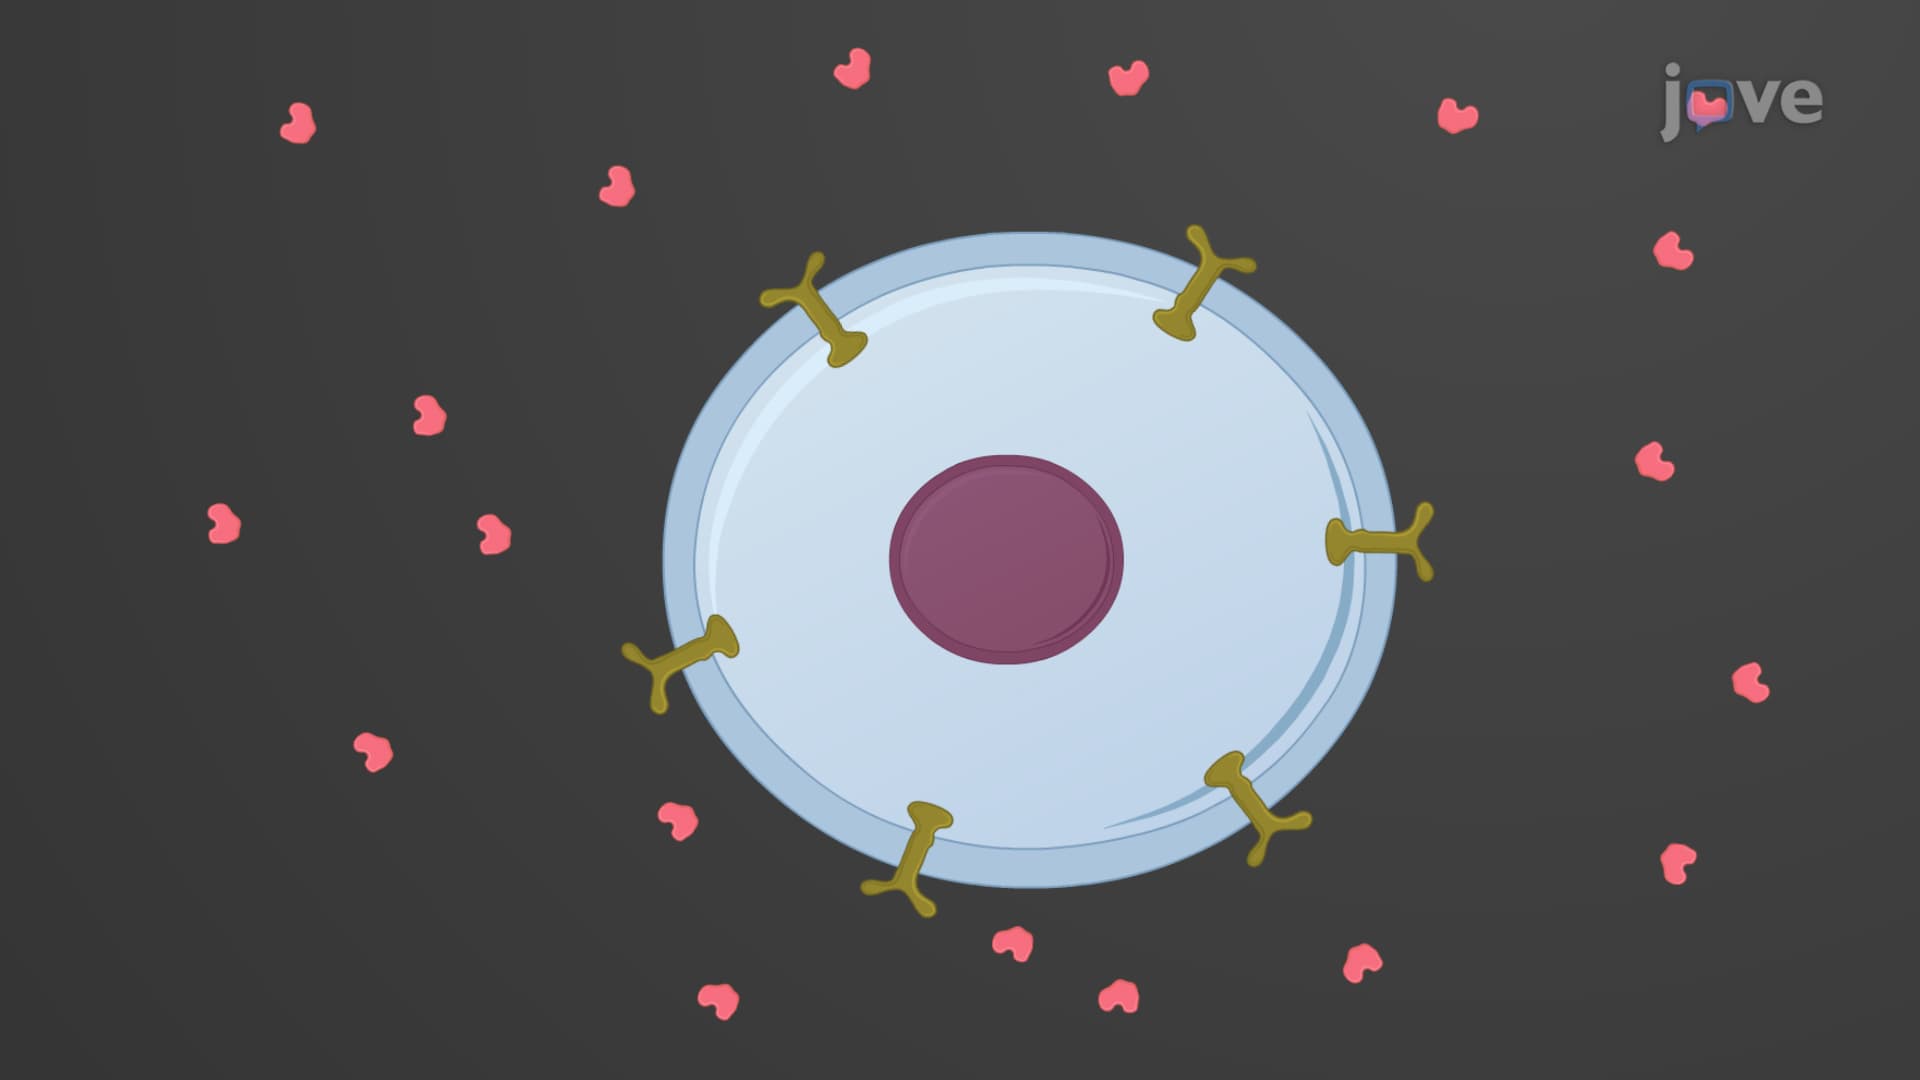
Target Cell Response to Hormones
Notably, the cellular response can be regulated by altering the number of receptors expressed in the cell. For example, prolonged exposure to elevated hormone levels results in a gradual decline or down-regulation in the number of receptors for that specific hormone on the cell surface. Conversely, in response to low hormone levels, cells may use up-regulation, producing an...
 01:01
Feedback Loops