Related Experiment Video
Updated: Aug 10, 2026
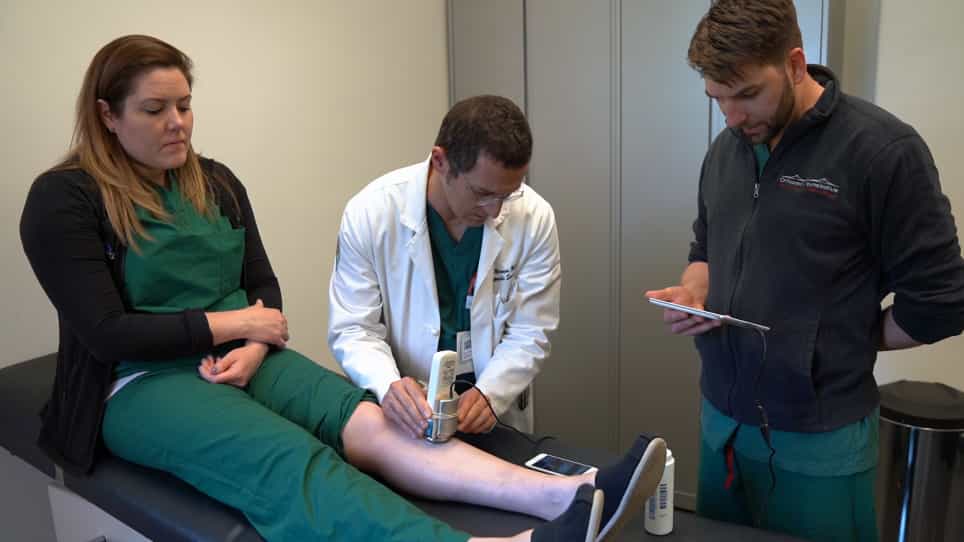

A Novel Non-invasive Method for the Detection of Elevated Intra-compartmental Pressures of the Leg
Published on: May 31, 2019
A historical review of compartment syndrome and Volkmann's ischemic contracture
1Division of Orthopaedic Surgery, Scripps Clinic and Research Foundation, La Jolla, California, USA.

Insights
Compartment syndrome, a condition recognized since the 1800s, has seen significant advancements in understanding its cause, diagnosis, and treatment. Modern treatment focuses on relieving intracompartment pressure to prevent contractures.
Area of Science:
- Orthopedics
- Trauma Surgery
- Vascular Surgery
Background:
- Compartment syndrome has been a recognized clinical entity since the mid-nineteenth century.
- Over a century of research and clinical observation has deepened the understanding of this complex condition.
- Clinician contributions have established current perspectives on pathogenesis, diagnosis, and treatment.
Observation:
- Volkmann's early work over 100 years ago identified increased "pressure" as a potential cause.
- Clinical observations have been pivotal in understanding the disease process.
- The evolution of treatment strategies is based on these observations.
Findings:
- The pathogenesis of compartment syndrome is complex and has been extensively studied.
- Diagnosis has improved through dedicated clinical efforts.
- Treatment strategies have evolved significantly over the past century.
Implications:
- Current treatment concepts aim to prevent contractures by managing increased intracompartment pressure.
- The understanding of compartment syndrome continues to evolve through ongoing research.
- Effective management relies on a thorough grasp of its pathophysiology and timely intervention.
Abstract:
Compartment syndrome has been a recognized disease entity since the mid-nineteenth century. Extensive research and clinical observation have allowed for a better understanding of this uniquely complex disease process. Outstanding contributions by clinicians over the past century have provided the basis for our current perspective on its pathogenesis, diagnosis, and treatment. Although Volkmann's early reference to increased "pressure" as the cause of this syndrome was made over 100 years ago, today's modern concept of treatment to prevent contracture based on increased intracompartment pressure has evolved only through the combined efforts of various committed clinicians during the past century.

Related Concept Videos
 01:16
Vascular Spasm
 01:27
Assessment of the Cardiovascular System III: Palpation
Jugular Venous Pressure (JVP) Measurement
Position the patient at a thirty- to forty-five-degree angle or in a semi-fowler's position. Look for the highest point of pulsation in the internal jugular vein and measure the vertical distance to the angle of Loius or sternal angle. A normal JVP is 3-4 cm above the...
 01:21
Peripheral Arterial Disease II: Clinical Manifestations and Diagnostic Evaluation
 01:23
Peripheral Artery Disease V: Postoperative Nursing Management
 01:20
Venous Thrombosis II: Clinical Manifestations and Diagnostic Studies
 01:24
Healing II: Complications