Related Experiment Video
Updated: Aug 9, 2026


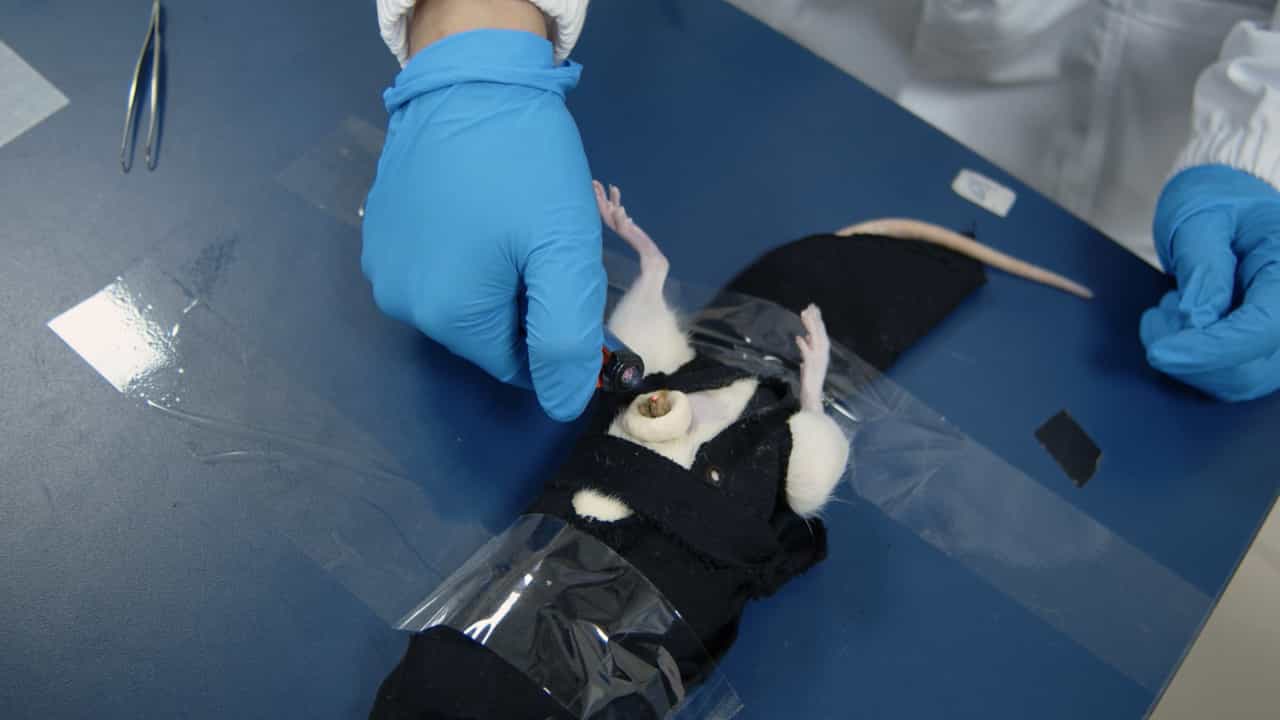
Introduction of Intracapsular Rotary-cut Procedures (IRCP): A Modified Hysteromyomectomy Procedures Facilitating Fertility Preservation
Published on: January 17, 2019
Treatment Decisions in the Management of Menorrhagia
1Family Medicine at Quillen College of Medicine, East Tennessee State University.

Abstract:
Menorrhagia--menstrual periods lasting longer than 7 days and totaling blood losses greater than 80mL--affects 9%-14% of otherwise healthy women, and it can signal cancer, an endocrinologic disorder, or gynecologic disease. Blood loss can be high enough to result in anemia, fatigue, and syncope. Most often, abnormal uterine bleeding such as menorrhagia involves a disruption in the hypothalamic-pituitary axis, the ovary, and/or the uterus. Other identified causes include medications (especially psychotropics) that cross the blood-brain barrier; chronic diseases such as cancer, diabetes, and liver and kidney dysfunction; endocrine disorders, perimenopausal anovulation, polycystic ovary disease, pituitary tumors, and abnormal estrogen cycling caused by morbid obesity; and anatomic abnormalities of the uterus. Routine tests include hematocrit or hemoglobin to detect and evaluate anemia, thyroid stimulating hormone (TSH) level to evaluate thyroid function as a possible cause, and a pregnancy test to rule out an incomplete, spontaneous abortion as a cause. A Pap test is recommended to screen for dysplasia that can suggest a gynecologic cancer cause. Additional screening for endocrine disorders that may be causing menorrhagia include tests of thyroid, liver, and kidney function, and tests of follicle stimulating hormone (FSH), prolactin, and cortisol levels. Treatment can be medical or surgical. Medical treatment includes prostaglandin inhibitors, specifically nonsteroidal antiinflammatory drugs (NSAIDs), and hormonal therapy with estrogen, progesterone, gonadotropin-releasing hormone agonists, or oral contraceptives such as medroxyprogesterone (Depo-Provera). Surgical treatment includes hysteroscopic endometrial ablation by physical agents, laser electrodiathermy, and "roller ball," or surgical, resection. Hysterectomy is the treatment of last resort.
More Related Videos

Related Concept Videos
 01:28
Esophageal Varices-II: Clinical Features and Management
In the initial assessment, a thorough review of the patient's medical history is vital to identify risk factors such as liver disease, alcohol abuse, or...
 01:26
Peptic Ulcer Disease IV: Management
The therapeutic approach involves ensuring adequate rest, implementing drug therapy, promoting smoking cessation, making dietary modifications, and emphasizing long-term follow-up care.
Pharmacological management
The prevailing therapy for peptic ulcers involves a combination of managing the patient's current medication...
 01:25
Mitral Regurgitation III: Medical Management
 01:26
Mitral Stenosis III: Medical Management
 01:26
Varicose Veins II: Diagnostic Studies and Interprofessional Care
 01:29
Venous Thrombosis III: Interprofessional Care