Helicobacter pylori infection in recurrent abdominal pain
Related Experiment Video
Updated: Oct 28, 2026

Gastric Mucosa Quantitative Polymerase Chain Reaction Analysis for Detecting Helicobacter pylori and Antibiotic Resistance
Published on: March 7, 2025
D Bansal1, A K Patwari, V L Malhotra
1Department of Pediatrics and Microbiology, Lady Hardinge Medical College, New Delhi.

Insights
Helicobacter pylori (Hp) infection is not strongly linked to recurrent abdominal pain (RAP) in children, with similar infection rates found in both affected children and healthy controls. The rapid urease test (RUT) is a reliable method for diagnosing Hp.
Area of Science:
- Pediatric Gastroenterology
- Infectious Diseases
Background:
- Recurrent abdominal pain (RAP) is a common pediatric complaint.
- Helicobacter pylori (Hp) infection is a potential, though not fully established, cause of gastrointestinal issues in children.
Purpose of the Study:
- To investigate the association between Helicobacter pylori infection and recurrent abdominal pain in children.
- To assess the efficacy of different diagnostic methods for Helicobacter pylori.
Main Methods:
- A prospective case-control study was conducted in a teaching hospital.
- Children aged 3-12 with RAP underwent upper gastrointestinal endoscopy with biopsy.
- Diagnostic tests included histopathology, rapid urease test (RUT), and serum IgG antibodies against Hp, compared to age-matched controls.
Main Results:
- Helicobacter pylori colonization was found in 23% of children with RAP, which was not significantly higher than the 19% seroprevalence in controls.
- A significant correlation was observed between Hp colonization and chronic antral gastritis and chronic duodenitis.
- The rapid urease test (RUT) demonstrated reliability in detecting Hp infection.
Conclusions:
- Helicobacter pylori does not appear to be a common cause of recurrent abdominal pain in this pediatric population.
- Chronic antral gastritis and chronic duodenitis are significantly associated with Hp colonization.
- The rapid urease test (RUT) is a dependable diagnostic tool for Helicobacter pylori detection.
Objective:
To study the relationship between Helicobacter pylori (Hp) infection and recurrent abdominal pain (RAP) and to evaluate various modalities to diagnose Hp infection.
Design:
Prospective case control study.
Setting:
Teaching hospital.
Methods:
Children between 3-12 years of age with RAP in whom upper gastrointestinal endoscopic examination was indicated were studied. Endoscopic biopsy specimen were collected from duodenum, antrum and esophagus. Apart from histopathological examination of biopsy material, rapid urease test (RUT) of the antral biopsy specimen and blood examination to estimate specific IgG antibodies to Hp by Indirect Solid Phase Enzyme Immunoassay was performed. The results of Hp IgG antibodies was compared with age matched controls.
Results:
Thirty one children with RAP were subjected to endoscopic examination and their anti Hp IgG antibodies status compared with 26 controls. Hp colonization was detected in 7 children (23%) with RAP; by RUT in 23% and antral biopsy in 16% of cases. Anti Hp IgG antibodies were also positive in almost equal proportion (19%) of controls (p = 0.757). Endoscopic examination revealed esophagitis in 16% of cases and none had evidence of gastric or duodenal erosion, ulcer or cobblestone appearance of antrum. A significant correlation of Hp was noticed with chronic antral gastritis (p = 0.002), chronic duodenitis (p = 0.02) and age > 10 years (p = 0.02). No significant correlation was noticed between Hp colonization and various socioeconomic risk factors.
Conclusion:
Hp does not seem to be commonly associated with RAP in our patient population as Hp colonization was detected in only 23% of cases which was not significantly higher than the seroprevalence of anti Hp IgG antibodies in the controls. However, a small sample size of our study limits drawing any firm conclusions. Antral gastritis and chronic duodenitis had a significant correlation with Hp colonization. RUT was found to be a reliable diagnostic test to detect Hp.
Related Concept Videos
 01:26
Gastritis II: Pathophysiology
 01:28
Peptic Ulcer Disease III: Clinical Manifestations and Diagnostic Studies
Few clinical manifestations differentiate gastric ulcers from duodenal ulcers. Distinctions in the location, timing, and pain relief are crucial for healthcare providers in differentiating between gastric and duodenal ulcers during clinical assessments.
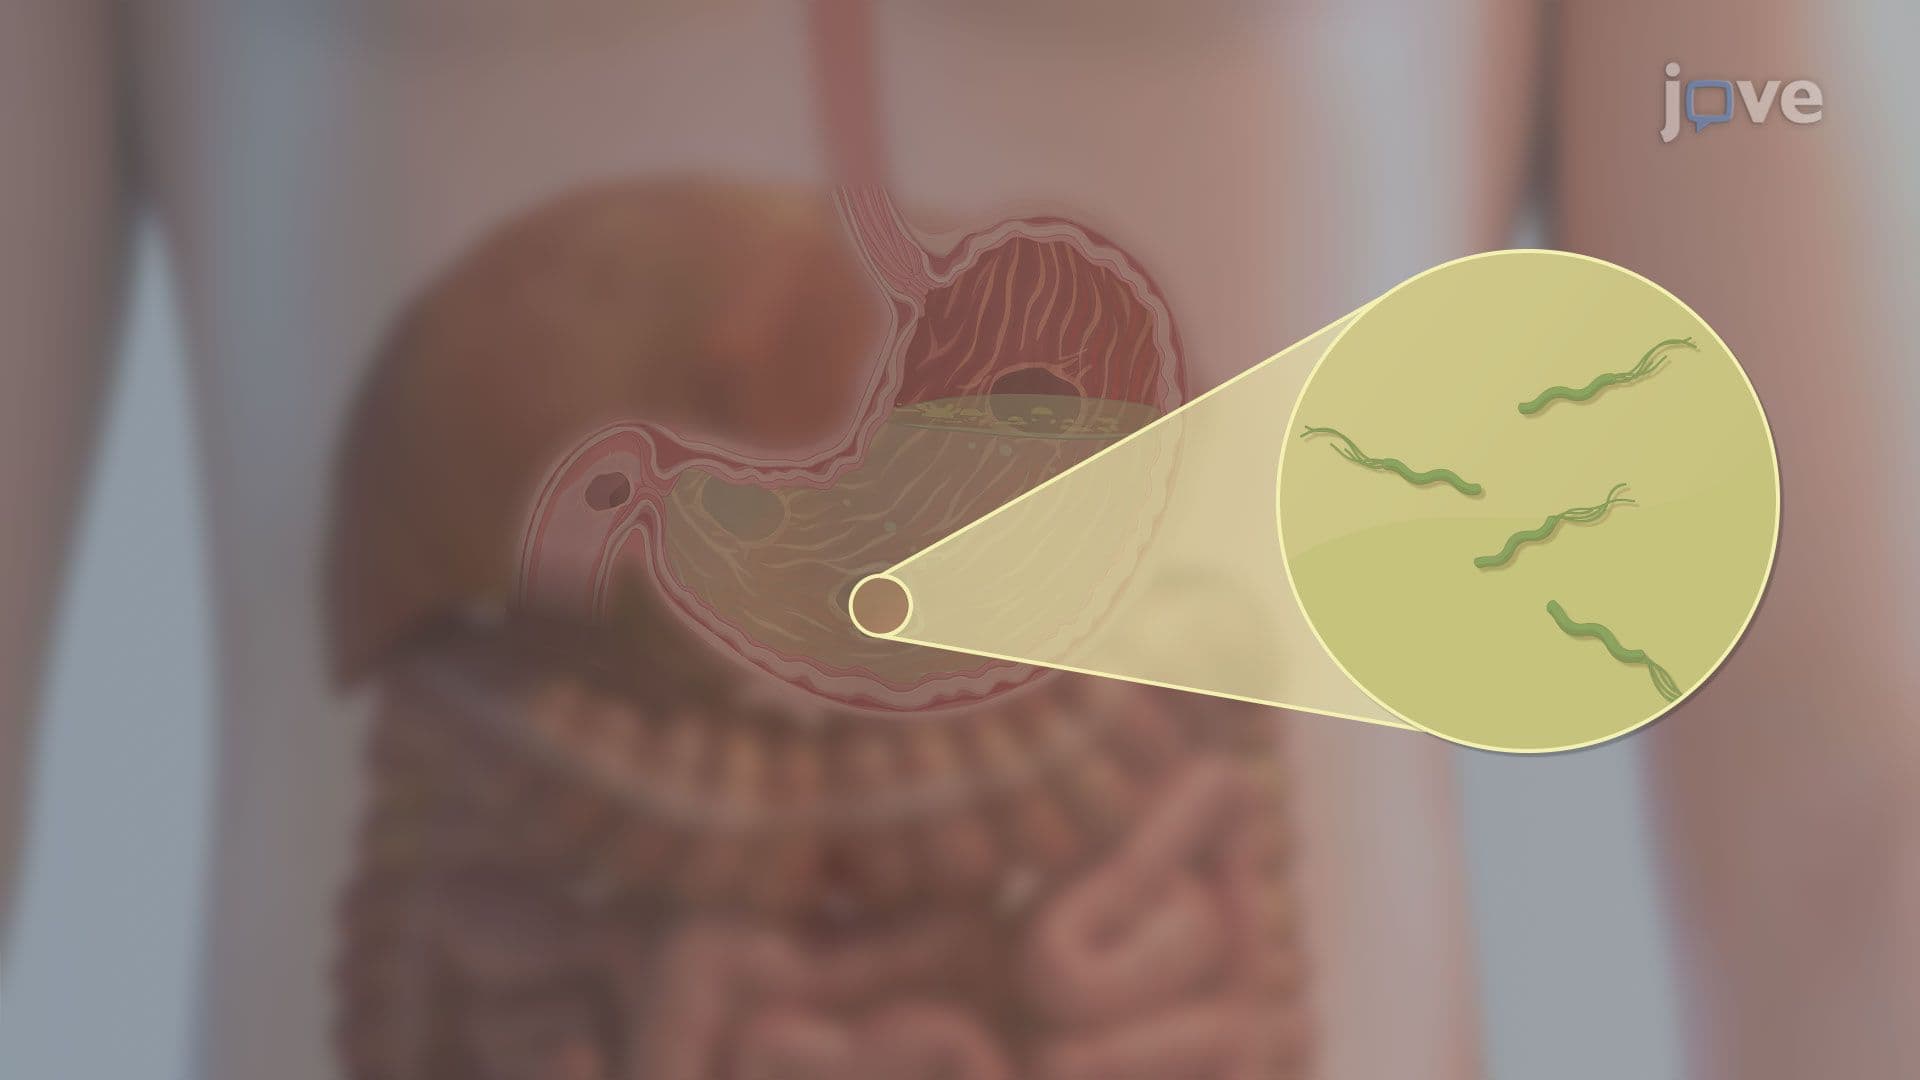 01:27
Peptic Ulcer
 01:16
Treating Helicobacter pylori in Peptic Ulcers: Antimicrobial Therapy
 01:22
Pathophysiology of Peptic Ulcer Disease: Injurious Factors
In the antrum region, G cells secrete the gastrin hormone that binds to gastrin-cholecystokinin-B (CCK2) receptors on parietal and enterochromaffin-like (ECL) cells in the fundic glands. Simultaneously, the vagus nerve releases acetylcholine, which binds to M3...
 01:24
Peptic Ulcer Disease II: Pathophysiology