Pyloric stenosis due to Crohn's disease
Related Experiment Video
Updated: Oct 28, 2026
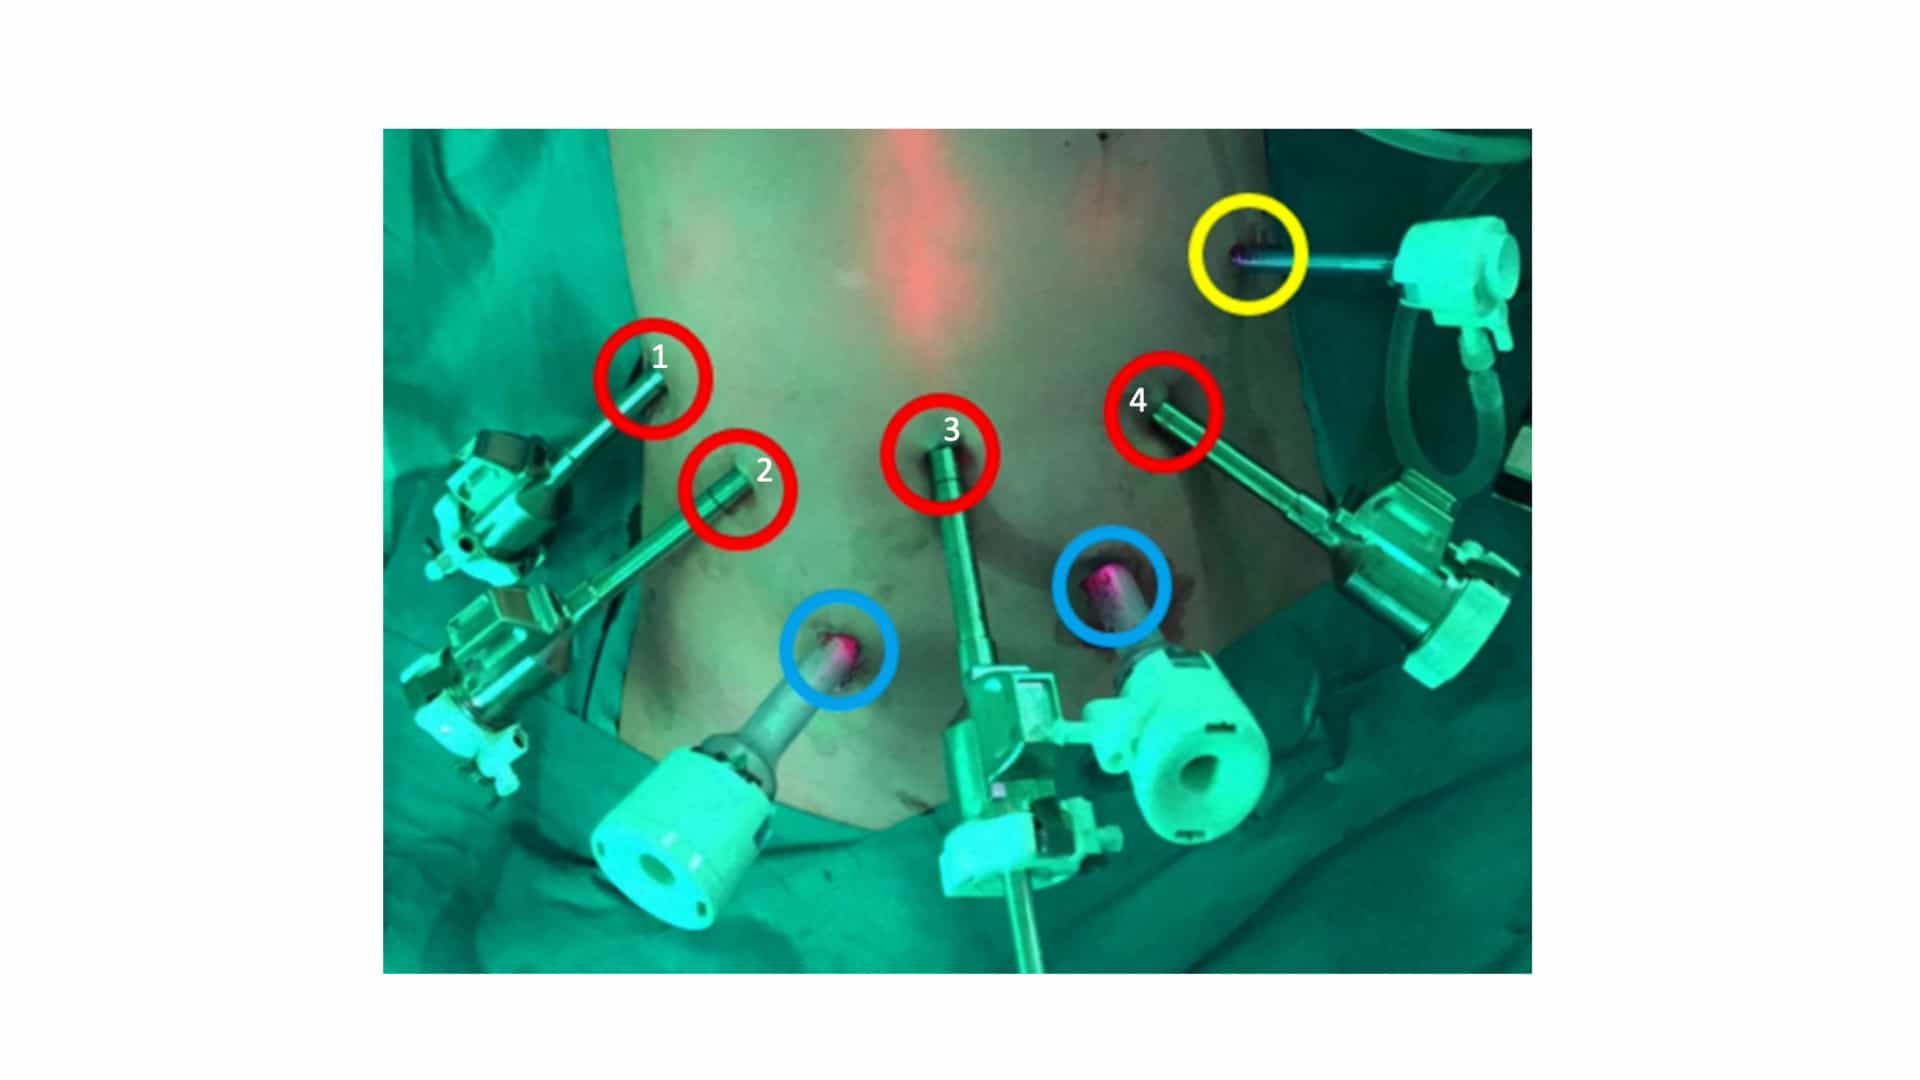
Robotic D3 Partial Duodenal Resection with Primary Side-to-Side Anastomosis
Published on: December 15, 2023
1First Department of Internal Medicine, Yamaguchi University School of Medicine, Kogushi, Ube, Japan.

Insights
Corticosteroids effectively reduced pyloric stenosis in a Crohn's disease patient unresponsive to other treatments. This finding offers a potential non-surgical option for managing this rare gastrointestinal complication.
Area of Science:
- Gastroenterology
- Inflammatory Bowel Disease
- Digestive System Disorders
Background:
- Crohn's disease, a chronic inflammatory condition, can affect the gastroduodenal region, though this is uncommon.
- Pyloric stenosis, a narrowing of the stomach's exit, is a potential complication of gastroduodenal Crohn's disease.
- Medical and surgical interventions are considered for pyloric stenosis, with varying success rates.
Observation:
- A 44-year-old male patient presented with pyloric stenosis attributed to Crohn's disease.
- The patient's condition was refractory to treatment with a proton-pump inhibitor.
- Helicobacter pylori infection was ruled out as a causative factor.
Findings:
- Corticosteroid therapy demonstrated a significant positive impact on reducing the severity of pyloric stenosis.
- The patient experienced marked improvement following corticosteroid administration.
- Non-response to proton-pump inhibitors highlights the specific challenges in managing this Crohn's complication.
Implications:
- Corticosteroids may represent a viable therapeutic option for managing Crohn's disease-induced pyloric stenosis.
- This case suggests a potential non-surgical approach for patients with refractory gastroduodenal Crohn's disease.
- Further research is warranted to explore the efficacy and mechanisms of corticosteroid treatment in similar cases.
Abstract:
Gastroduodenal involvement by Crohn's disease is relatively rare and occasionally causes pyloric stenosis, for which medical therapy may be ineffective and surgery may be required. We report on a 44-year-old man patient in whom corticosteroids had a marked effect in reducing pyloric stenosis caused by Crohn's disease. A proton-pump inhibitor was not effective, and Helicobacter pylori was negative.
Related Concept Videos
 01:25
Inflammatory Bowel Disease III: Crohn's Disease
 01:30
Inflammatory Bowel Disease II: Crohn's Disease
Inflammatory bowel disease, commonly known as IBD, refers to a collection of disorders that lead to persistent inflammation of the gastrointestinal tract. The two types of IBD are ulcerative colitis, which impacts the colon, and Crohn's disease, which can involve any part of the gastrointestinal segment.
Crohn's disease
Crohn's disease is a chronic, systemic inflammatory bowel disease (IBD) that predominantly affects the gastrointestinal tract. It is marked by transmural...
 01:28
Peptic Ulcer Disease II: Pathophysiology
Damaging agents such as Helicobacter pylori, gastric acid, pepsin, and nonsteroidal anti-inflammatory drugs (NSAIDs) can weaken the mucosal defense, allowing hydrogen ions to infiltrate back and harm epithelial cells.
 01:24
Peptic Ulcer Disease II: Pathophysiology
 01:17
Gastritis-II: Pathophysiology
In acute gastritis, the gastric mucosa becomes swollen and red and undergoes superficial erosion. Superficial ulceration may lead to bleeding.
In chronic gastritis, persistent or repeated insults lead to chronic inflammatory changes and, eventually, thinning or atrophy of the gastric tissue.
Gastritis can stem from various causes, each...
 01:26
Gastritis II: Pathophysiology