Modifying effects of amlodipine on cyclosporin A-induced changes in renal function in patients with psoriasis
Related Experiment Video
Updated: Oct 27, 2026

Quantification of the Immunosuppressant Tacrolimus on Dried Blood Spots Using LC-MS/MS
Published on: November 8, 2015
G V Raman1, S K Campbell, A Farrer
1Wessex Renal and Transplant Unit and the University of Southampton, UK.

Objective:
To assess the benefit of amlodipine, a calcium channel blocker, on renal function and vasoactive hormones in individuals with normal kidneys and blood pressure and who were being treated with cyclosporin A for refractory psoriasis.
Design:
An open-label, two-stage, longitudinal study was employed.
Methods:
Patients were divided into two groups: Group I received cyclosporin A, 5 mg/kg per day for 6 months titrated down to 2.5-3.5 mg/kg per day for 6 months, then concomitant amlodipine 5 mg/day for 6 months; and Group II received concomitant cyclosporin A, 5 mg/kg per day, and amlodipine, 5 mg/day, for 6 months. Blood pressure, serum creatinine, glomerular filtration rate, urinary magnesium, plasma renin activity and urinary kallikrein excretion were measured before and after treatment.
Results:
Eighteen patients were enrolled, and 12 completed the study. In Group I (n = 7), 12 months of cyclosporin A therapy significantly increased systolic blood pressure and significantly decreased glomerular filtration rate, plasma renin activity and active urinary kallikrein. Amlodipine reversed these changes. In Group II (n = 5), 6 months of concomitant cyclosporin A and amlodipine significantly reduced active urinary kallikrein levels. No significant changes occurred in the other measured parameters in either group.
Conclusions:
Cyclosporin A produces a sustained and significant fall in glomerular filtration rate and urinary kallikrein excretion, even in patients with normal kidneys and blood pressure. Amlodipine is potentially capable of reversing these nephrotoxic effects.
Related Concept Videos
 01:08
Effect of Hepatic Disease on Pharmacokinetics: Dose Adjustments Due to Hepatic Impairment
 01:29
Drugs for Treatment of Crohn's Disease in IBD Using Immunomodulatory Agents
 01:26
Heart Failure Drugs: Inhibitors of Renin-Angiotensin System
 01:25
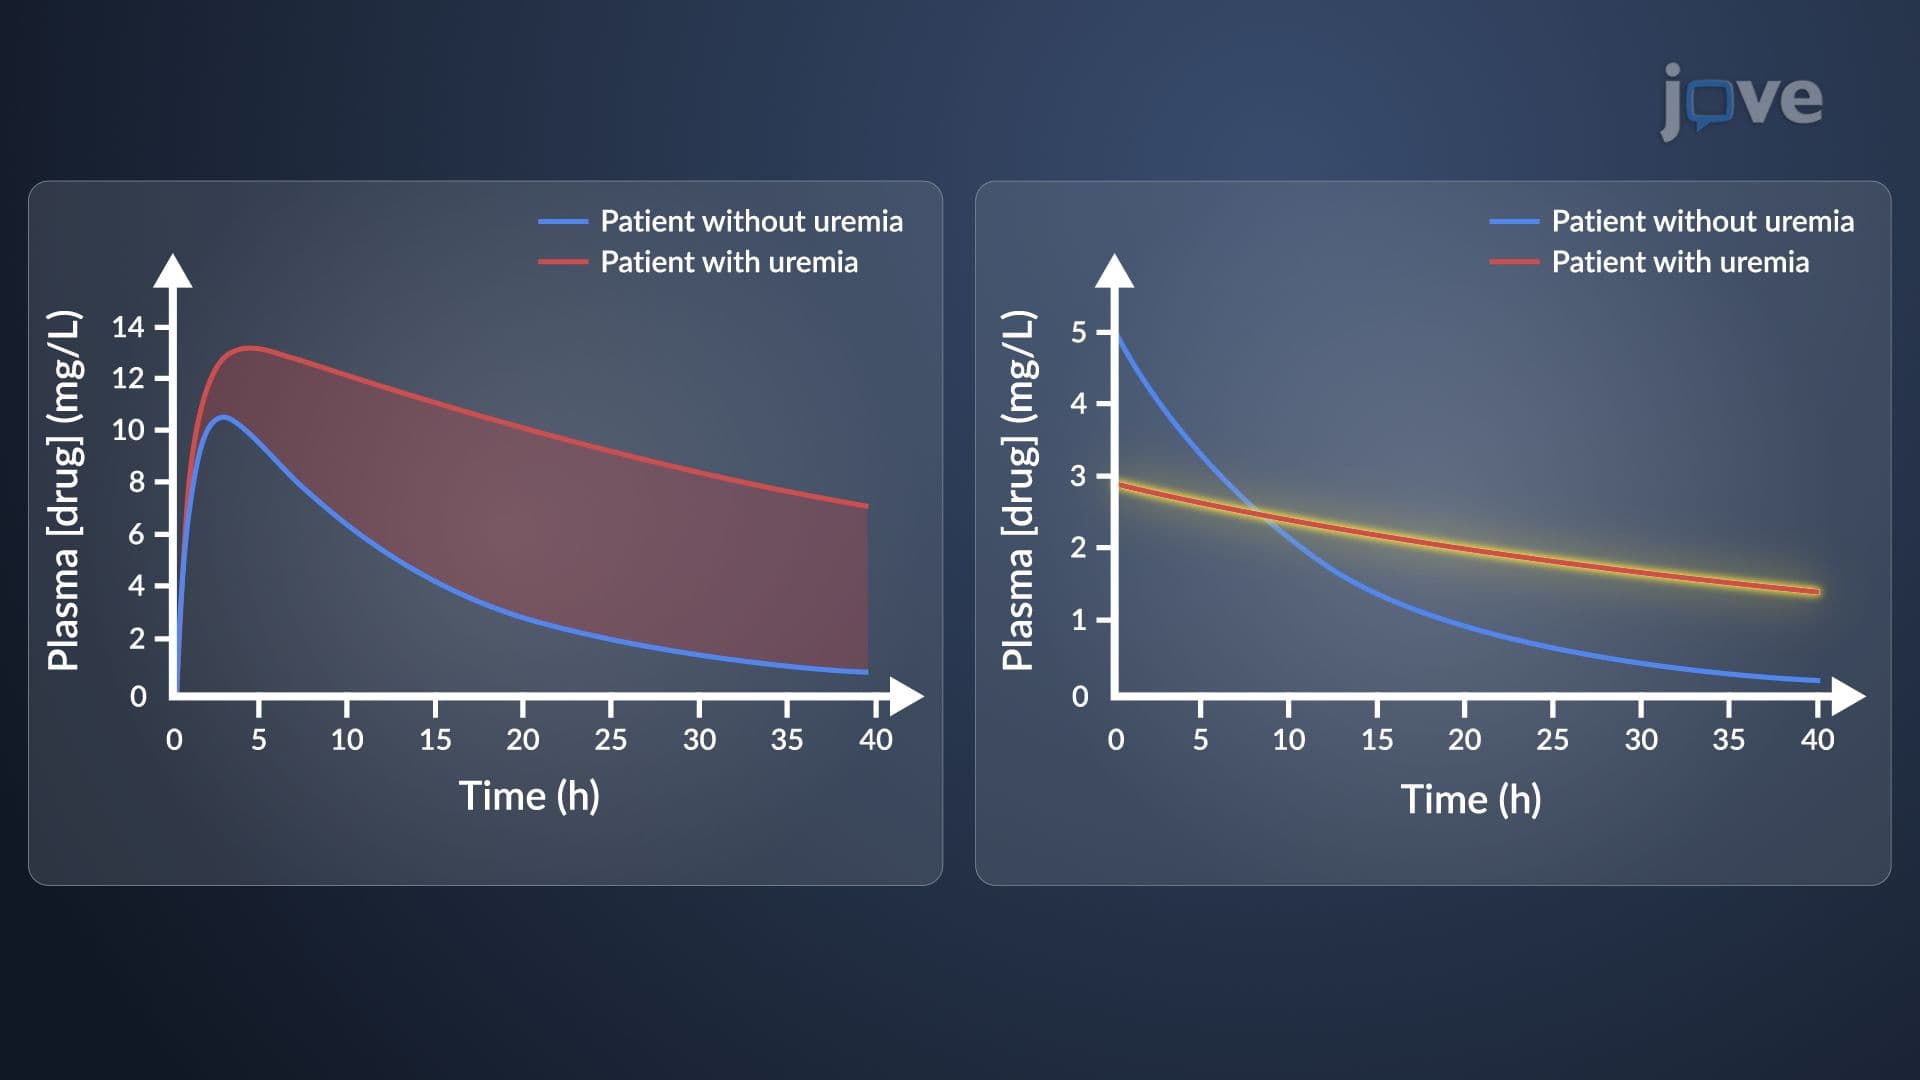
Drug Dosing in Renal Diseases: Dose Adjustments Based on Drug Clearance and Elimination Rate Constant
 01:25
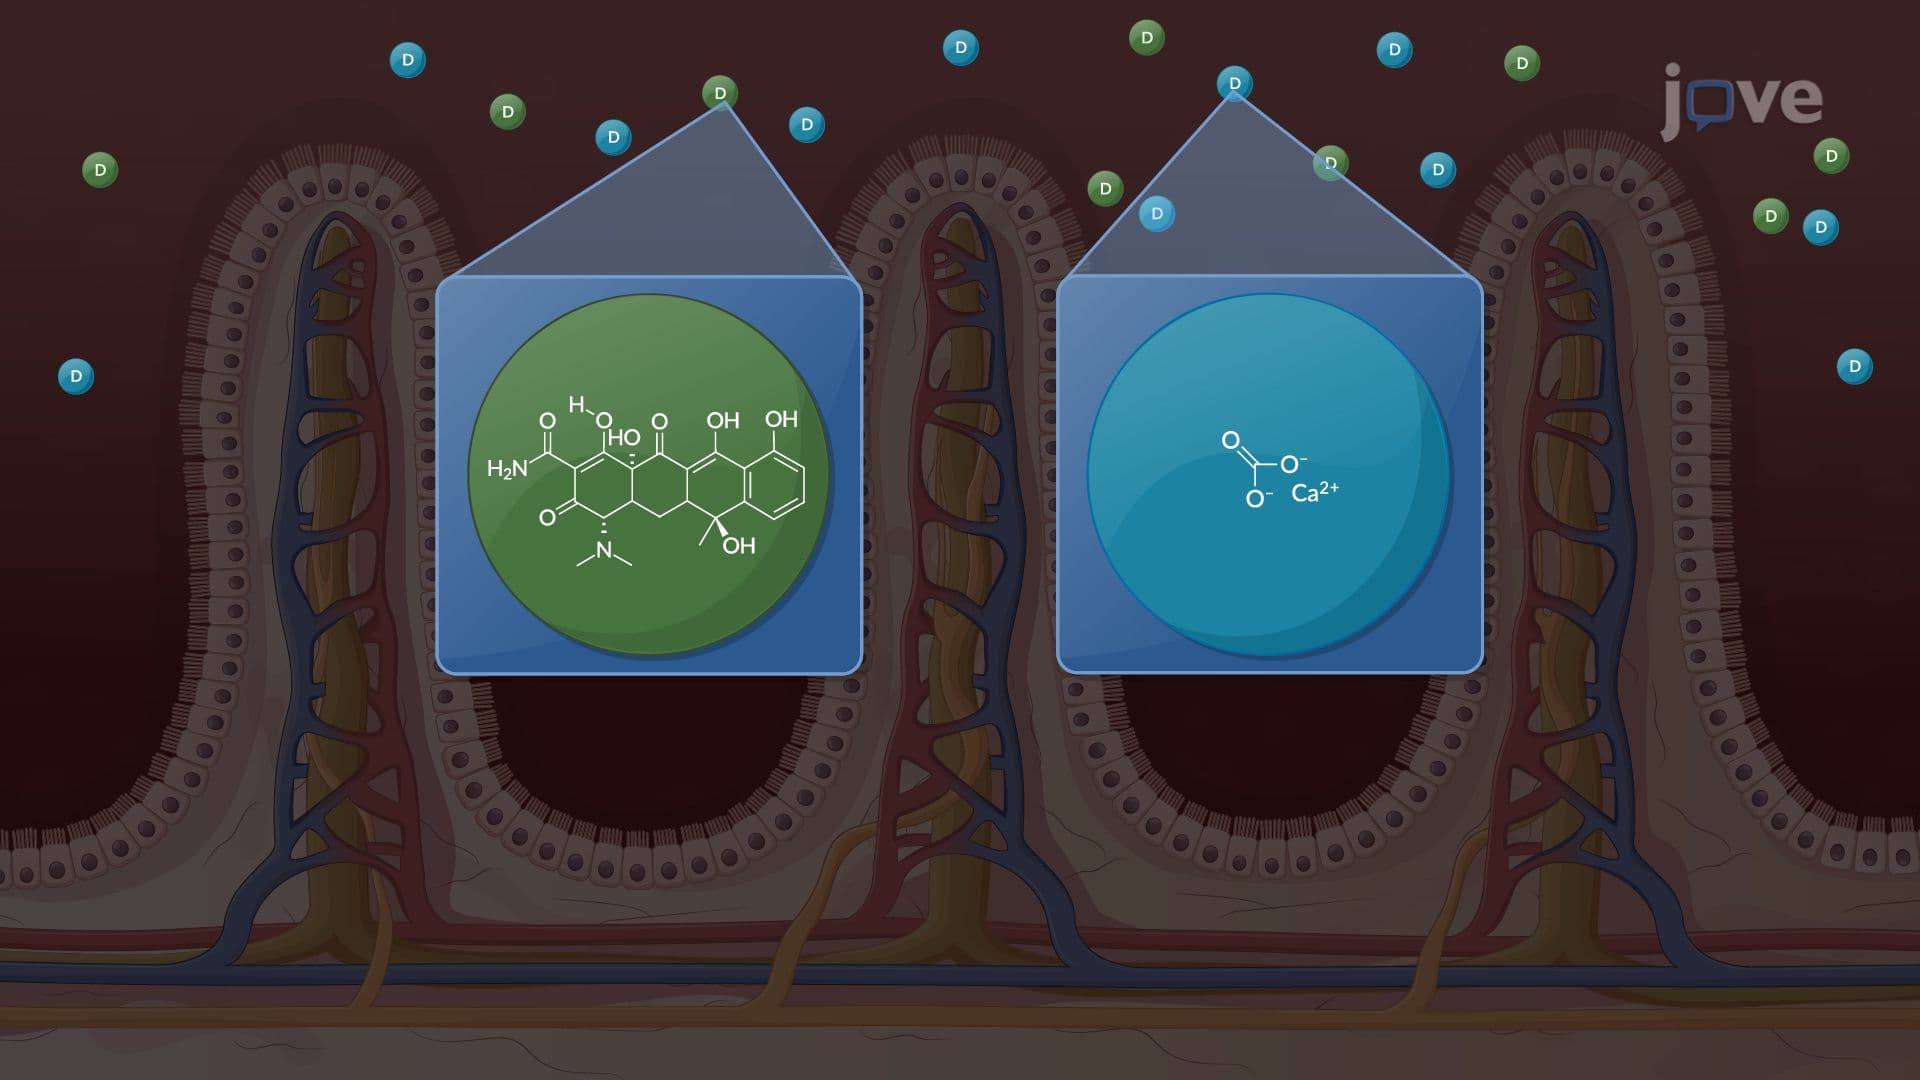
Pharmacokinetics: Drug–Drug Interactions
 01:29
Pharmacogenetic Phenotypes: Alterations in Pharmacokinetics, Drug Targets and Biologic Milieu