Related Experiment Video
Updated: Aug 9, 2026
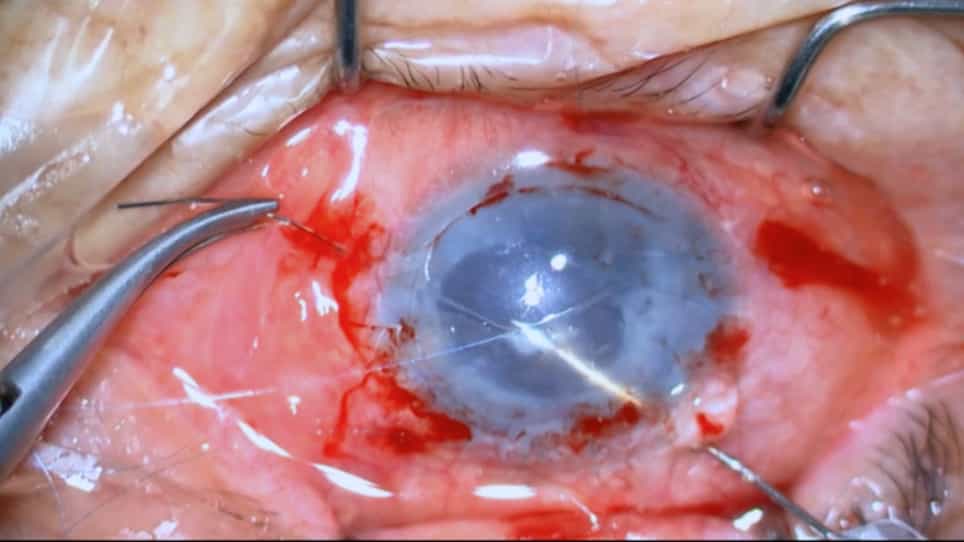
Three Different Protocols of Corneal Collagen Crosslinking in Keratoconus: Conventional, Accelerated and Iontophoresis
Published on: November 12, 2015
Combined interrupted and continuous versus single continuous adjustable suturing in penetrating keratoplasty: a
C H Karabatsas1, S D Cook, F C Figueiredo
1Department of Ophthalmology, Bristol Eye Hospital, England.

Objective:
To compare postoperative astigmatism induced by two different suturing techniques in penetrating keratoplasty (PKP).
Design:
A monocenter, prospective, randomized clinical trial with a longitudinal 1-year follow-up.
Participants:
A total of 95 eyes undergoing PKP were randomized into 2 groups. Of these, 51 eyes were allocated to the combined interrupted and continuous suturing group (ICS) and 44 eyes to the single continuous adjustable suturing (SCAS) group.
Intervention:
In the ICS group, suturing was with a combination of 12 interrupted 10-0 nylon and 1 continuous 11-0 nylon sutures. Eyes in the SCAS group had been sutured with a single running 24-bite 10-0 nylon. Selective suture removal started no earlier than 10 weeks after surgery; suture adjustment could start as soon as possible after surgery.
Main Outcome Measures:
Astigmatism was measured by topography, keratometry, and refraction at 3-, 6-, 9-, and 12-month postoperative intervals.
Results:
The difference in mean time of suture manipulation between groups was significant (P = 0.0001), with the SCAS starting earlier. A significant decrease in astigmatism occurred by either interrupted suture removal (6.69 +/- 3.11 diopter [D] before to 4.76 +/- 2.99 D after, P = 0.0002) or suture adjustment (7.18 +/- 3.12 D before to 4.46 +/- 3.24 D after, P = 0.0001). However, the net astigmatic reduction in the SCAS group was not significantly greater (P = 0.250) than in the ICS group. Vector change was 7.40 +/- 4.17 D and 6.28 +/- 4.14 D for SCAS and ICS, respectively (P = 0.13). At no interval (3, 6, 9, or 12 months) was there significant difference in astigmatism between the two groups. Refractive astigmatism (cyl, D) at 1 year was 2.66 +/- 1.70 for the ICS and 3.12 +/- 2.62 for the SCAS, but there was no significant treatment effect (P = 0.945). Furthermore, 66% of the ICS eyes and 58% of the SCAS eyes (P = 0.295) were within the astigmatic target of the study (<3.5 D).
Conclusions:
Postkeratoplasty astigmatism can be decreased similarly with either adjustment of a single running suture or selective removal of interrupted sutures. No advantage of the SCAS over ICS in terms of fewer manipulations or less astigmatism was seen as suggested previously.