

Gastroparesis after celiac plexus block
1Department of Internal Medicine, Mayo Clinic and Foundation, Rochester, Minnesota 55905, USA.

A 36-yr-old woman with metastatic mucinous cystadenocarcinoma of the pancreas underwent neurolytic celiac plexus block with 100% ethanol and 0.5% bupivacaine for intractable back pain. Several hours after the procedure she developed severe nausea and vomiting, which persisted for days despite cessation of opioid analgesics, and administration of intravenous metoclopramide and ondansetron. Both esophagogastroduodenoscopy and barium examination of the stomach and small intestine showed excess gastric fluid but no evidence of mechanical obstruction. A radionuclide study revealed delayed gastric emptying of solids. Treatment with oral cisapride 10 mg p.o. q.i.d. resulted in considerable symptomatic improvement. We document the first reported case of gastroparesis after celiac plexus block and discuss possible etiological mechanisms.
A 36-yr-old woman with metastatic mucinous cystadenocarcinoma of the pancreas underwent neurolytic celiac plexus block with 100% ethanol and 0.5% bupivacaine for intractable back pain. Several hours after the procedure she developed severe nausea and vomiting, which persisted for days despite cessation of opioid analgesics, and administration of intravenous metoclopramide and ondansetron. Both esophagogastroduodenoscopy and barium examination of the stomach and small intestine showed excess gastric fluid but no evidence of mechanical obstruction. A radionuclide study revealed delayed gastric emptying of solids. Treatment with oral cisapride 10 mg p.o. q.i.d. resulted in considerable symptomatic improvement. We document the first reported case of gastroparesis after celiac plexus block and discuss possible etiological mechanisms.


Related Concept Videos
 01:20
Gastrointestinal Motility Disorders
 01:16
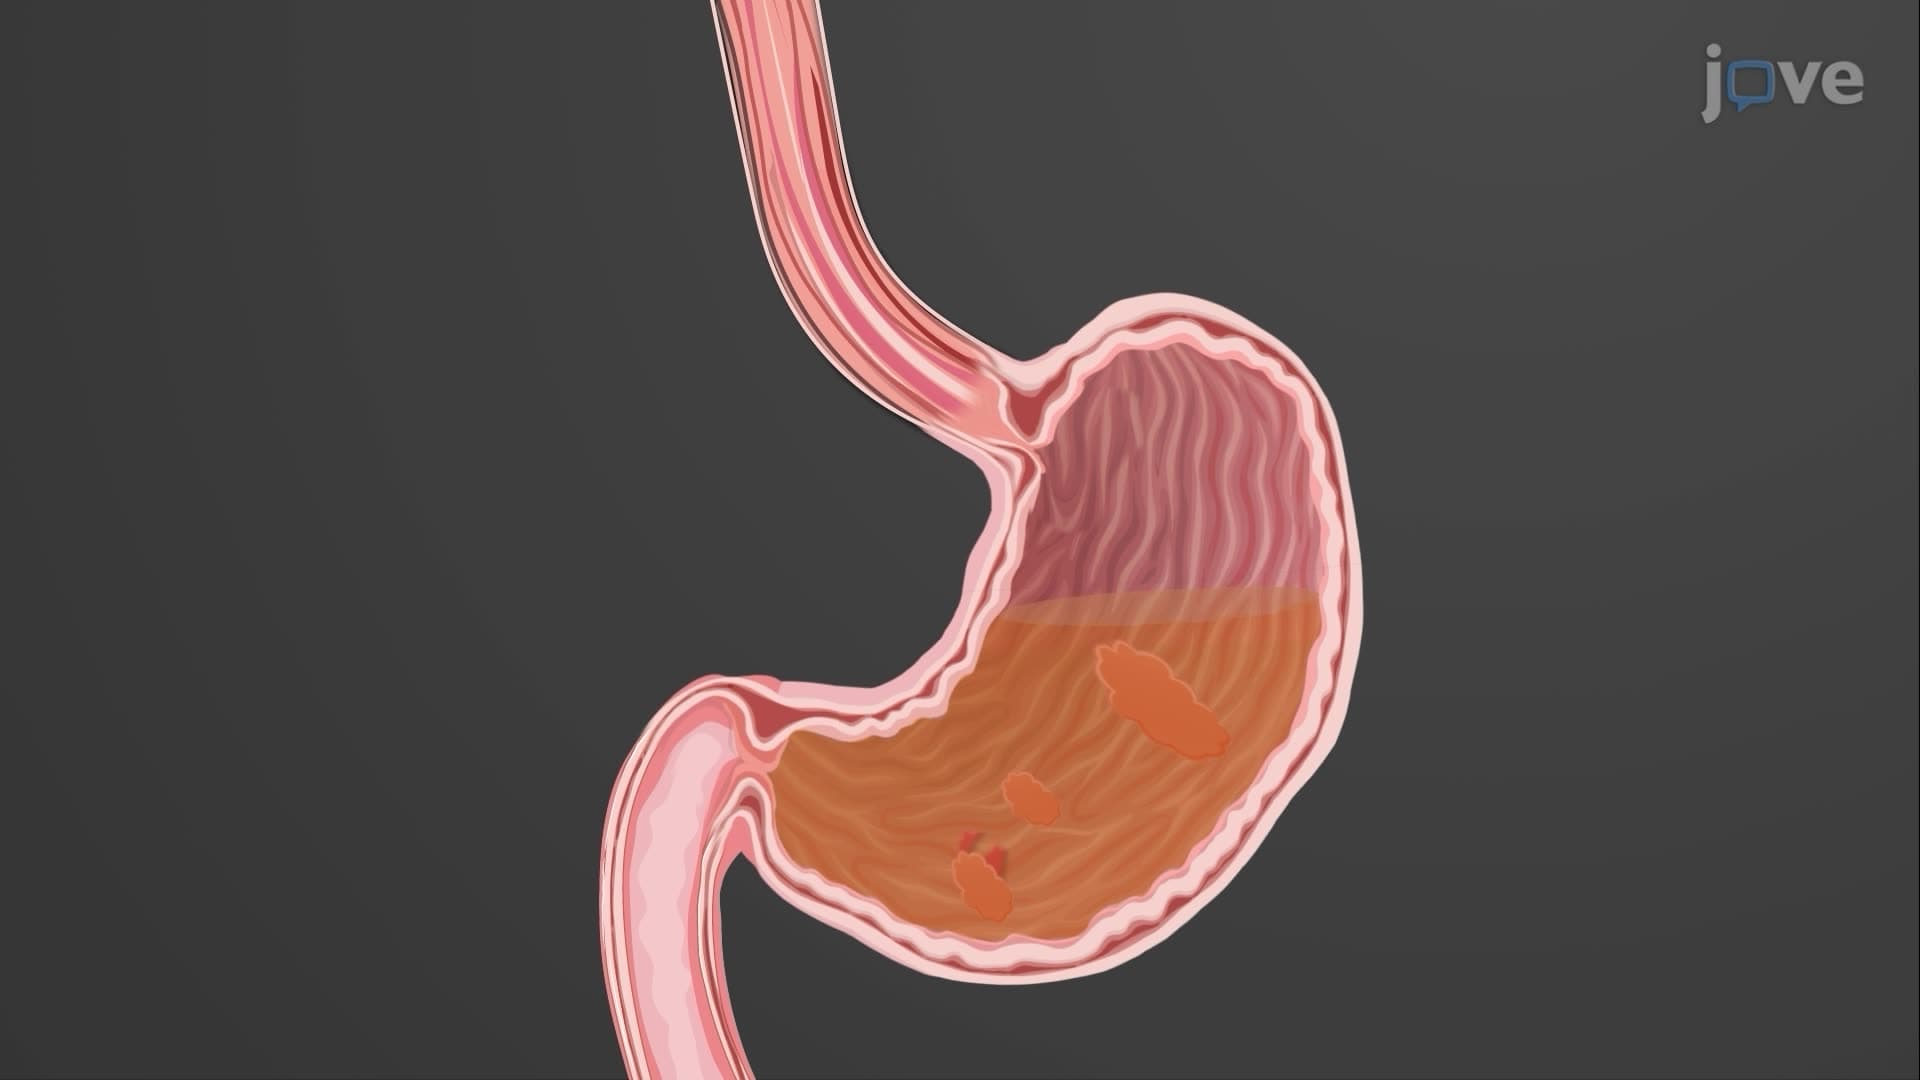
Gastric Emptying
 01:26
Endoscopic Procedures IV: Sigmoidoscopy and Laproscopy
Sigmoidoscopy
Sigmoidoscopy is a diagnostic procedure that uses a flexible sigmoidoscope equipped with a light source and camera to examine the rectum and sigmoid colon. The procedure involves inserting the tube through the anus...
 01:22
Aneurysm IV: Nursing Management
 01:27
Esophageal Achalasia
 01:11
Pyloric Obstruction