Related Experiment Video
Updated: Aug 16, 2026
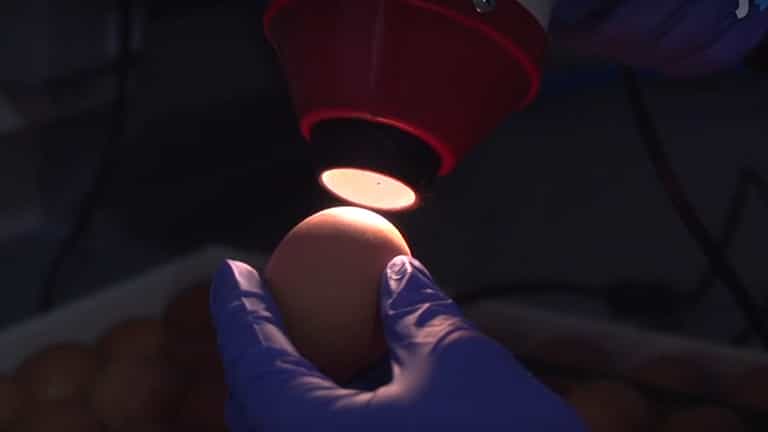

An In Ovo Model for Testing Insulin-mimetic Compounds
Published on: April 23, 2018
Novel hepatoselective insulin analogues: studies with covalently linked thyroxyl-insulin complexes
F Shojaee-Moradie1, H Eckey, N C Jackson
1Department of Medicine, UMDS, Guy's and St Thomas's Hospital, London, UK.

To explore the possibility that insulin analogues designed to have restricted access to peripheral tissues may display relative hepatoselectivity in vivo, Nalphabeta1-thyroxyl-insulin (B1-T4-Ins) and Nalphabeta1-thyroxyl-aminohexanoyl insulin (B1-T4-AHA-Ins) were synthesized. These insulin analogues bind thyroid hormone binding proteins to form high molecular weight complexes. Effects of intravenous infusions of B1-T4-Ins; B1-T4-AHA-Ins; combined thyroxine binding globulin (TBG) and B1-T4-Ins and combined TBG and B1-T4-AHA-Ins were compared with those of insulin infusion in hyperinsulinaemic euglycaemic clamp protocols in anaesthetized beagles (n=4 and n=3 for combined TBG infusions). Glucose turnover rates were measured using D-[3-3H]glucose infusion. With all 5 protocols the rate of glucose disappearance (Rd) was increased and the rate of endogenous glucose production (Ra) decreased from basal level 13.53+/-0.60 micromol kg(-1) min(-1)(p<0.05). Insulin-like activity for Ra and Rd was calculated as the area between the basal values of each variable and the subsequent values plotted graphically against time (AUC). For insulin, B1-T4-Ins, B1-T4-AHA-Ins, combined infusions of TBG+B1-T4-Ins, and TBG+B1-T4-AHA-Ins, respectively, AUC for Rd values were 6.30+/-0.69, 3.35+/-0.53, 4.40+/-0.64, 2.82+/-0.40 and 3.46+/-0.95 (mmol kg(-1)), all analogue infusions being different from insulin (p<0.05). AUC for Rd was further reduced by addition of TBG to B1-T4-AHA-Ins (p<0.05). In contrast the effect of all analogues on AUC for Ra was similar to that of insulin. These observations are compatible with the suggestion that insulin analogues which bind to thyroid hormone binding proteins retain access to hepatic insulin receptors which primarily control Ra. The reduced peripheral insulin-like effect (Rd) could be due to reduced transcapillary access to peripheral insulin receptor sites.
To explore the possibility that insulin analogues designed to have restricted access to peripheral tissues may display relative hepatoselectivity in vivo, Nalphabeta1-thyroxyl-insulin (B1-T4-Ins) and Nalphabeta1-thyroxyl-aminohexanoyl insulin (B1-T4-AHA-Ins) were synthesized. These insulin analogues bind thyroid hormone binding proteins to form high molecular weight complexes. Effects of intravenous infusions of B1-T4-Ins; B1-T4-AHA-Ins; combined thyroxine binding globulin (TBG) and B1-T4-Ins and combined TBG and B1-T4-AHA-Ins were compared with those of insulin infusion in hyperinsulinaemic euglycaemic clamp protocols in anaesthetized beagles (n=4 and n=3 for combined TBG infusions). Glucose turnover rates were measured using D-[3-3H]glucose infusion. With all 5 protocols the rate of glucose disappearance (Rd) was increased and the rate of endogenous glucose production (Ra) decreased from basal level 13.53+/-0.60 micromol kg(-1) min(-1)(p<0.05). Insulin-like activity for Ra and Rd was calculated as the area between the basal values of each variable and the subsequent values plotted graphically against time (AUC). For insulin, B1-T4-Ins, B1-T4-AHA-Ins, combined infusions of TBG+B1-T4-Ins, and TBG+B1-T4-AHA-Ins, respectively, AUC for Rd values were 6.30+/-0.69, 3.35+/-0.53, 4.40+/-0.64, 2.82+/-0.40 and 3.46+/-0.95 (mmol kg(-1)), all analogue infusions being different from insulin (p<0.05). AUC for Rd was further reduced by addition of TBG to B1-T4-AHA-Ins (p<0.05). In contrast the effect of all analogues on AUC for Ra was similar to that of insulin. These observations are compatible with the suggestion that insulin analogues which bind to thyroid hormone binding proteins retain access to hepatic insulin receptors which primarily control Ra. The reduced peripheral insulin-like effect (Rd) could be due to reduced transcapillary access to peripheral insulin receptor sites.


Related Concept Videos
 01:25
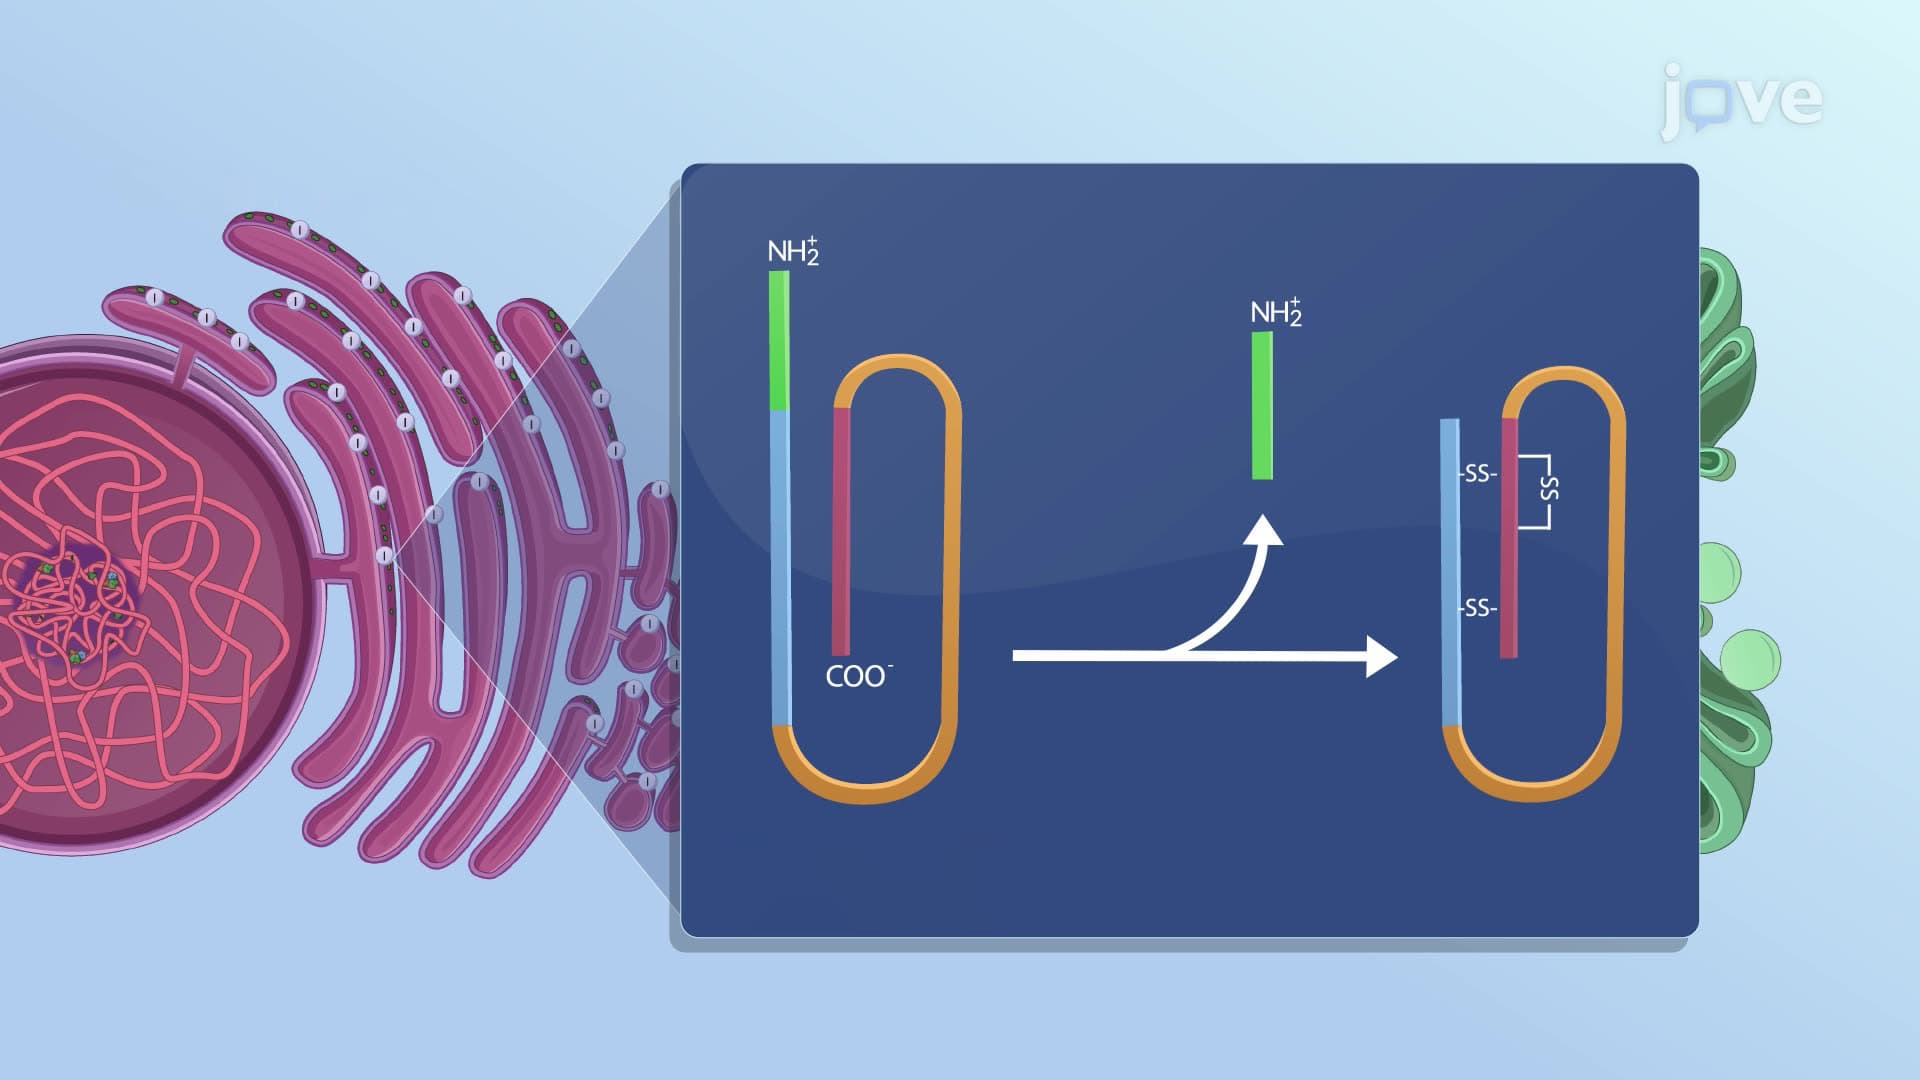
Insulin: Biosynthesis, Chemistry, and Preparation
Damage or functional impairment of β-cells inhibits insulin production, leading to diabetes. Diabetes treatment primarily uses...
 01:27
Insulin Formulations: Types and Delivery
Short-acting insulins are divided into rapid-acting...
 01:16
Insulin: Dosing Regimen and Adverse Effects
The basal dose constitutes about 40%-50% of the total daily dose, with the rest as premeal insulin. The mealtime insulin dose should mirror...
 01:17
Oral Hypoglycemic Agents: Sulfonylureas
 01:06
Oral Hypoglycemic Agents: Glinides
 01:24
Glucagon-like Receptor Agonists
GLP-1, when administered in high doses intravenously, triggers insulin secretion, inhibits glucagon release, slows gastric emptying, reduces food intake, and restores normal insulin secretion. However, its rapid inactivation by the...