Related Experiment Video
Updated: Aug 6, 2026


Assessment of Child Anthropometry in a Large Epidemiologic Study
Published on: February 2, 2017
Association of blood pressure in adolescence with birthweight
P O Pharoah1, C J Stevenson, C R West
1Department of Public Health, University of Liverpool.

Insights
Adolescents born with very low birthweight (VLBW) have higher systolic blood pressure. This finding suggests fetal development influences adolescent blood pressure, potentially linked to socioeconomic factors and maternal smoking.
Area of Science:
- Pediatric Health
- Cardiovascular Research
- Developmental Origins of Health and Disease
Background:
- Infants with very low birthweight (VLBW) face long-term health challenges.
- Understanding adolescent cardiovascular health in VLBW survivors is crucial for preventative strategies.
Purpose of the Study:
- To compare adolescent blood pressure in individuals born with very low birthweight (VLBW) against normal birthweight controls.
- To investigate the influence of fetal development and early-life factors on adolescent blood pressure.
Main Methods:
- A longitudinal cohort study followed VLBW infants born in Merseyside (1980-1) to age 15.
- Matched case-control analysis compared systolic and diastolic blood pressure, adjusting for anthropometric measures.
- Socioeconomic variables, maternal, and child smoking histories were documented.
Main Results:
- VLBW survivors exhibited significantly higher systolic blood pressure (mean difference 3.2 mm Hg) compared to controls.
- Controls were taller and heavier; no significant difference in body mass index.
- Adjusting for anthropometrics amplified systolic blood pressure differences; socioeconomic factors and smoking prevalence differed slightly.
Conclusions:
- Adolescent systolic blood pressure variations may originate during fetal development.
- Socioeconomic disparities and maternal smoking could contribute to observed blood pressure differences.
Aims:
To compare the blood pressure of very low birthweight infants with that of normal birthweight controls in adolescence.
Methods:
A cohort of all infants of birthweight < or = 1500 g born to women resident in the county of Merseyside in 1980-1 was followed up at age 15 years with age, sex, and school matched controls. Growth indices and blood pressures were measured under standard conditions. The smoking history of mothers and children and their status for several socioeconomic variables were documented. In a matched pairs analysis systolic and diastolic blood pressures were compared for cases and controls before and after adjusting for height, weight, and body mass index.
Results:
There were 172 singleton 15 year old survivors of birthweight < 1500 g out of 40,321 live births of Merseyside residents in 1980-1. Of the 172 survivors, 128 (74%) who had no clinical disability and 11 (6%) with a clinical disability but attending normal schools, were assessed with individually matched age, sex, and school controls. Twenty three (13%) had a clinical disability and were attending special schools; these were assessed without controls. Ten (6%) children refused or were unavailable for assessment. The systolic blood pressure was significantly higher in cases than in controls; the mean of the difference was 3.2 mm Hg. The diastolic blood pressure was also higher in the cases, but the difference was not significant. The controls were significantly heavier (4.4 kg), taller (4.0 cm), with larger head circumference (1.5 cm) than the cases. The difference in body mass index was not significant. Adjusting for height, weight, or body mass index increased the difference in systolic blood pressure between cases and controls. There were no significant differences in the socioeconomic variables, but what differences did exist favoured the controls. There was also a higher prevalence of smoking among the children and the mothers of the cases than the controls.
Conclusions:
The study supports the hypothesis that in adolescents variation in systolic blood pressure has its origins in fetal development. Some of the variation could be attributed to socioeconomic differences.

Related Concept Videos
 01:30
Blood Pressure
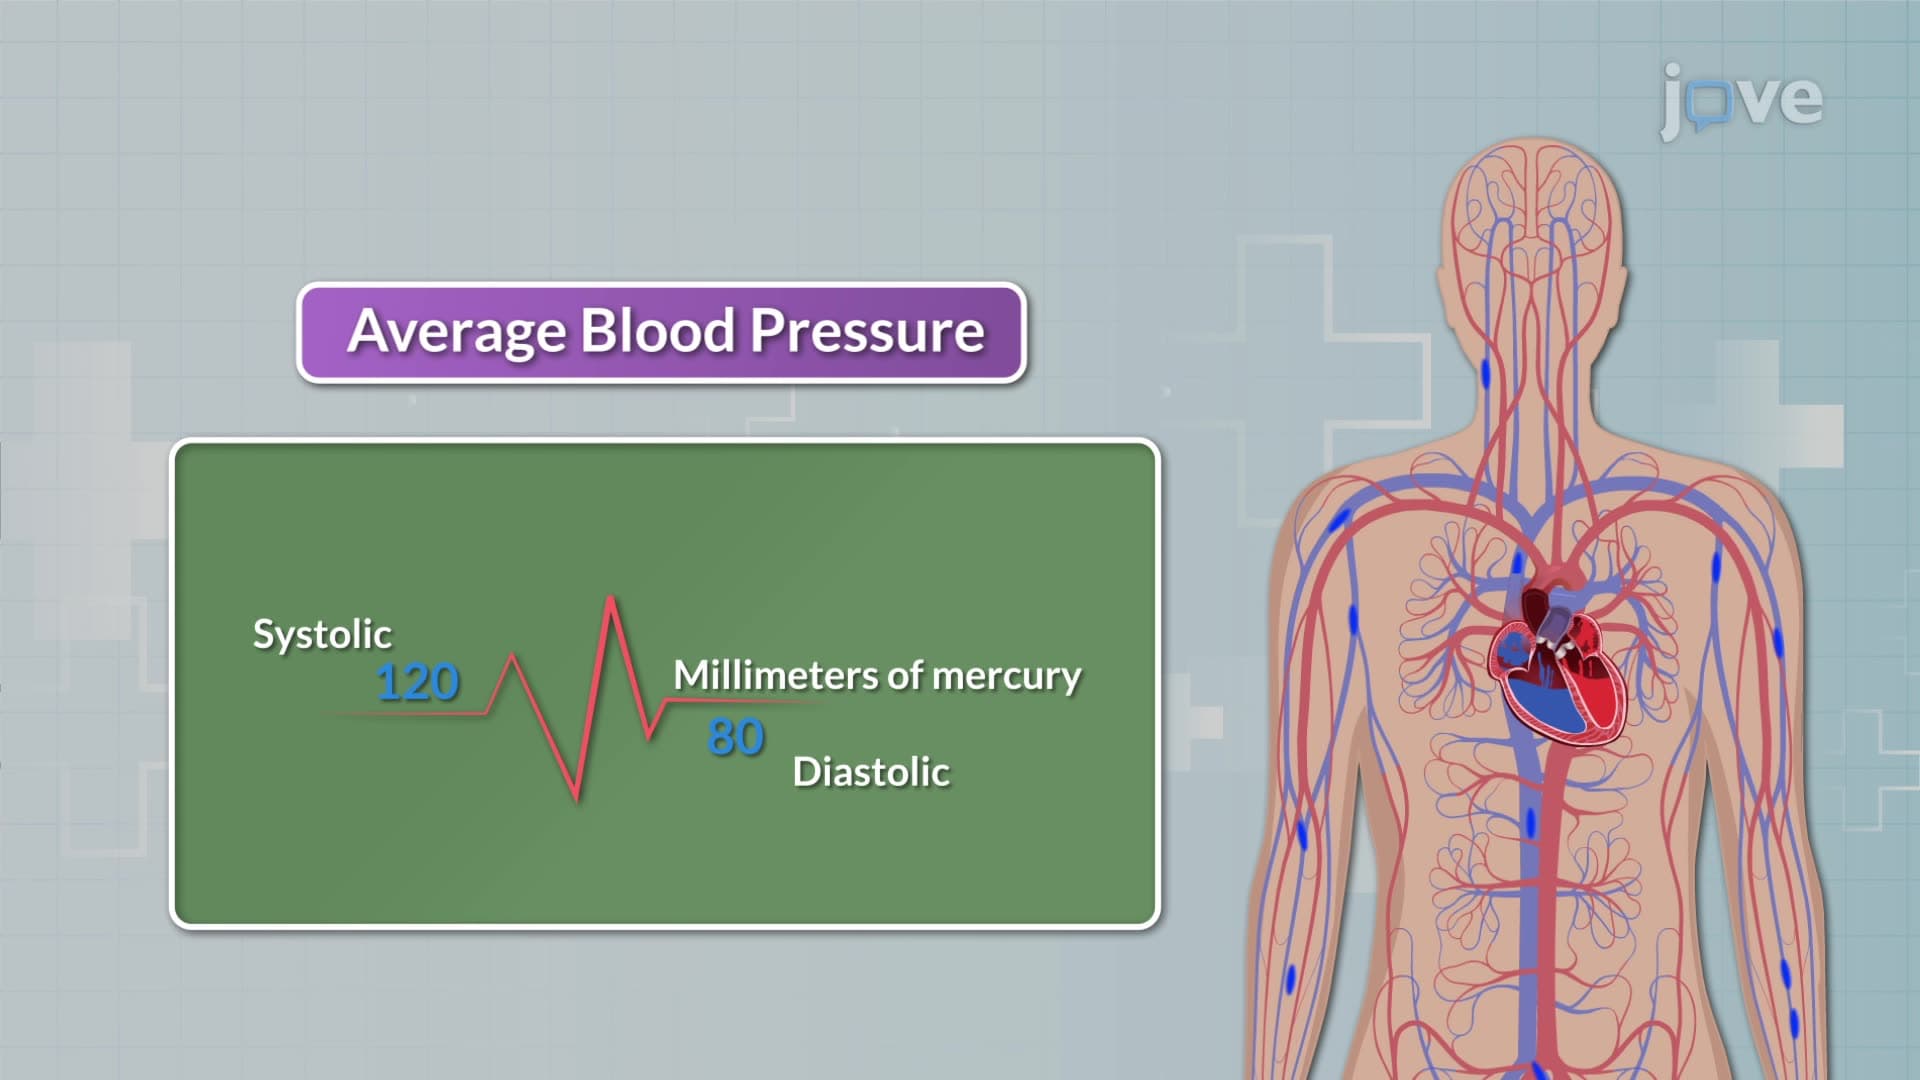
The average BP in an adult is typically around 120/80 mmHg (millimeters of mercury). In this measurement, the numerator (120) indicates the systolic pressure, which is the pressure in the arteries during the contraction of the heart's ventricles as blood is expelled. The denominator (80) represents the diastolic...
 01:28
Factors affecting Blood pressure
Physiological Factors:
 01:28
Special considerations while measuring blood pressure
Monitoring Both Arms:
Monitoring BP in both arms during the initial assessment is advisable, as the systolic value may differ by five to ten mm Hg between arms. For subsequent BP assessments, use the arm with the higher reading.
 01:18
Hypertension and Regulation of Blood Pressure
 01:24
Blood Pressure
 01:17
Measurement of Blood Pressure