Randomized long-term evaluation of bicarbonate-buffered CAPD solution
Related Experiment Video
Updated: Oct 20, 2026

Expired CO2 Measurement in Intubated or Spontaneously Breathing Patients from the Emergency Department
Published on: January 29, 2011
M Feriani1, J Kirchgessner, G La Greca
1Department of Nephrology, St. Bortolo Hospital, Vicenza, Italy and Fresenius AG Medical Science Department, Oberursel, Germany. mferani@goldne.it

Background:
Over the past 15 years, lactate has been used successfully as a buffer in peritoneal dialysis solutions, although its effectiveness in the correction of uremic acidosis and its biocompatibility on peritoneal resident cells have been questioned. In addition, some investigators have suggested other potential adverse metabolic effects resulting from the unphysiologically high lactate flux into the body during CAPD. These potential problems associated with lactate-containing CAPD solution prompted the search for alternative buffer-containing solutions. Bicarbonate, the physiological buffer, was considered when the problem of calcium and magnesium carbonate solubility was solved by the use of a two-compartment bag system, allowing the mixing of bicarbonate and divalent cations immediately before infusion. The long-term tolerance, safety, efficacy and therapeutic value of a bicarbonate-buffered peritoneal dialysis solution were evaluated in this study.
Methods:
This open, randomized, controlled, multicenter study comparing a 34 mmol/liter bicarbonate- with a 35 mmol/liter lactate-buffered peritoneal dialysis solution was performed in two consecutive 12-week-treatment phases. Fourteen Centers participated in this trial.
Results:
A total of 69 out of initially 123 randomized patients completed the six-month study period (36 patients in the bicarbonate group and 33 in the lactate group). While the arterial acid base status of the total study population did not change during the study period and no significant difference was observed between the two treatment groups, the acid-base status of patients in the bicarbonate group entering the study with a metabolic acidosis significantly improved (mean +/- SD; blood pH: baseline = 7.361 +/- 0.05, week 12 = 7.380 +/- 0.04, P < 0.05; week 24 = 7.388 +/- 0.03 P < 0.05; plasma bicarbonate: baseline = 19.49 +/- 3.01 mmol/liter, week 12 = 21.16 +/- 2.63 mmol/liter, P < 0.01; week 24 = 21.51 +/- 2.42 mmol/liter, P < 0.01). No significant changes were recorded in acidotic patients treated with the conventional lactate-buffered solution. The changes in plasma bicarbonate from baseline during the study was significantly different between the groups (week 12: lactate = +0.11 +/- 2.21 mmol/liter, bicarbonate = +1.69 +/- 2.55 mmol/liter, P < 0.05, 95% confidence interval for the difference 0.21 to 2.94 mmol/liter; week 24: lactate = +0.03 +/- 2.48 mmol/liter, bicarbonate = +1.82 +/- 2. 96 mmol/liter, P < 0.05, 95% confidence interval for the difference 0.16 to 3.42 mmol/liter). The normalized protein catabolic rate (nPCR) slightly but significantly decreased in the lactate group (baseline -0.90 +/- 0.23 g/kg/day, week 24 -0.83 +/- 0.21 g/kg/day, P < 0.01) and increased in the bicarbonate group (baseline +0.89 +/- 0.28 g/kg/day, week 24 +0.92 +/- 0.26 g/kg/day, P < 0.05). Changes from baseline between groups were significant (week 24, lactate = -0. 099 +/- 0.15 g/kg/day, bicarbonate = 0.049 +/- 0.12 g/kg/day, P < 0. 01, 95% confidence interval for the difference 0.068 to 0.229 g/kg/day). Other evaluated parameters (biochemical profile, peritoneal function parameters, dialysate protein loss) did not differ significantly between the two groups. No adverse effects related to the study solution were recorded.
Conclusions:
These results support the efficacy and safety of bicarbonate-buffered peritoneal solutions in a controlled randomized comparison for up to six months. Peritoneal dialysis solutions containing the physiological buffer bicarbonate might effectively replace conventional lactate-buffered CAPD solutions.

Related Concept Videos
 02:58
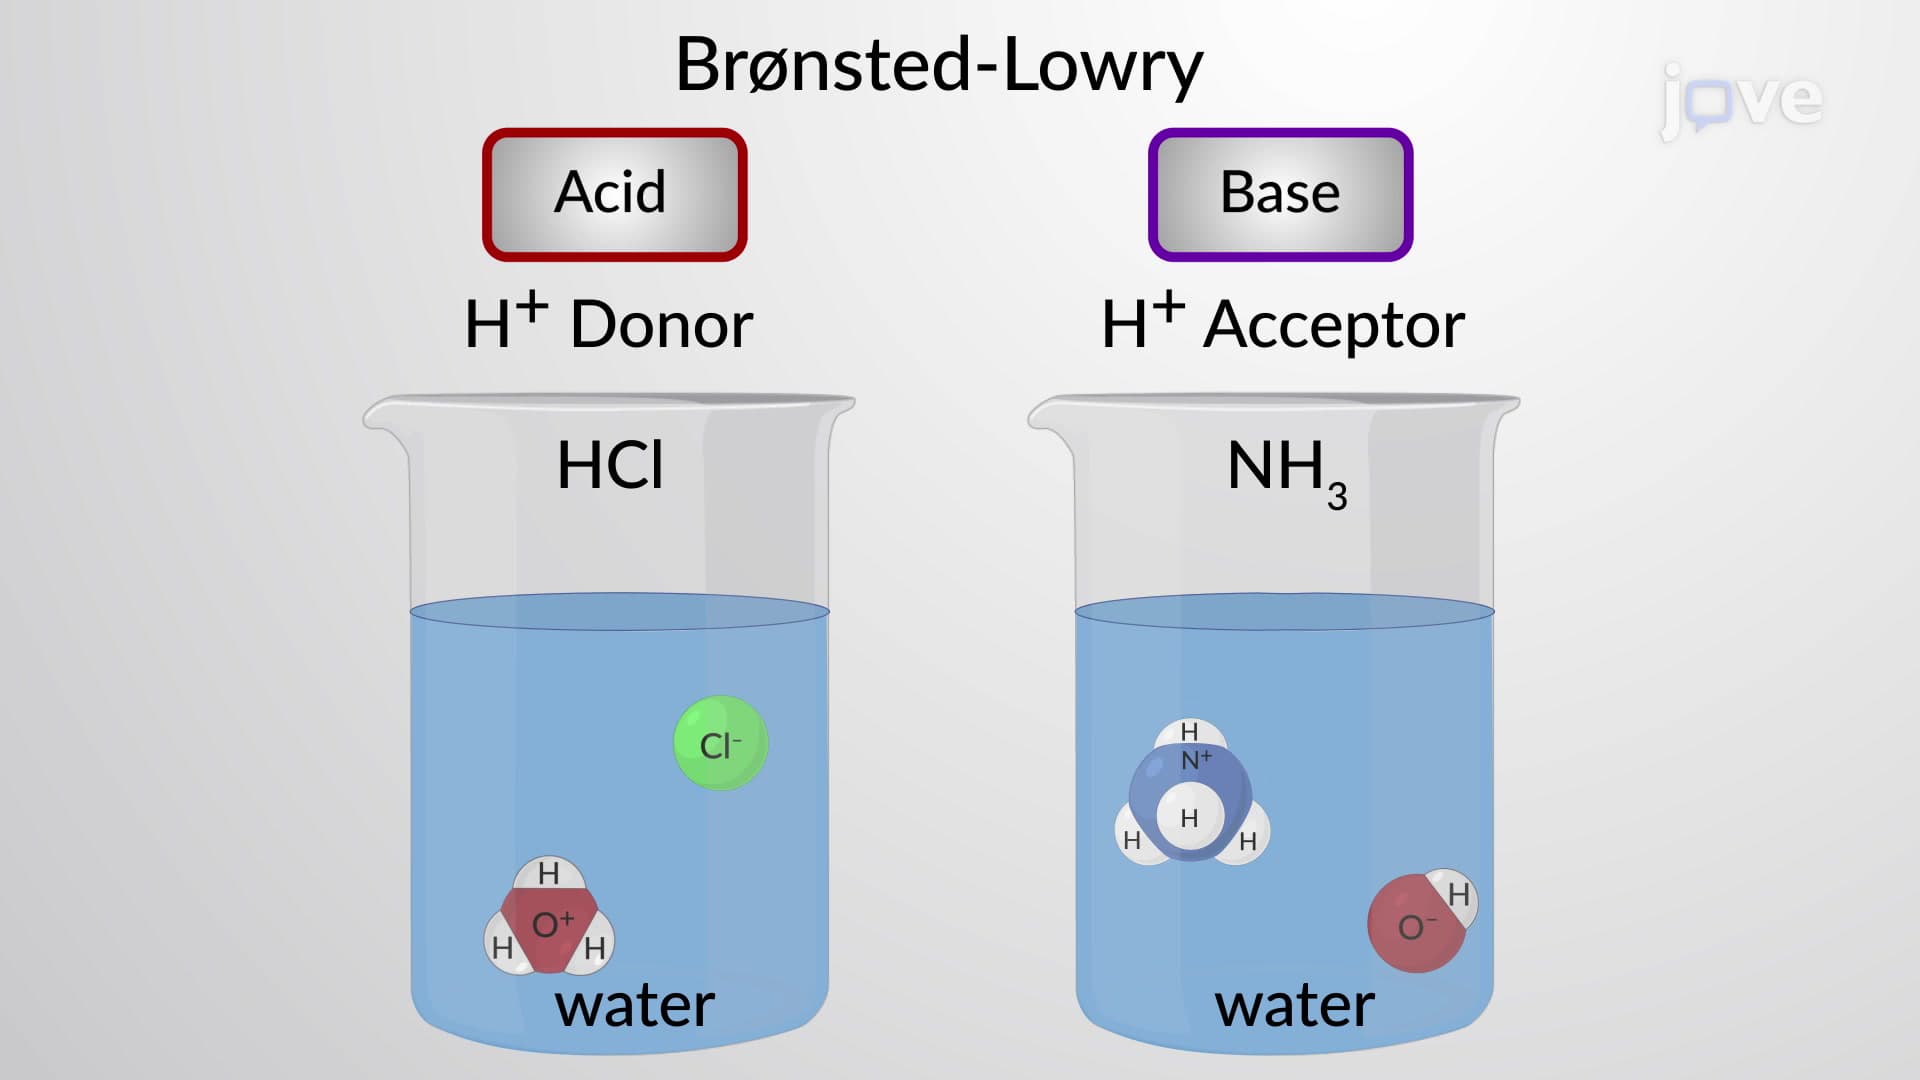
Bronsted-Lowry Acids and Bases
 01:17
Assessment of Diffusion and Perfusion
The Role of Diffusion in Respiration
Diffusion is the process by which molecules move from an area of higher concentration to an area of lower concentration. In the respiratory system, this principle...
 01:18
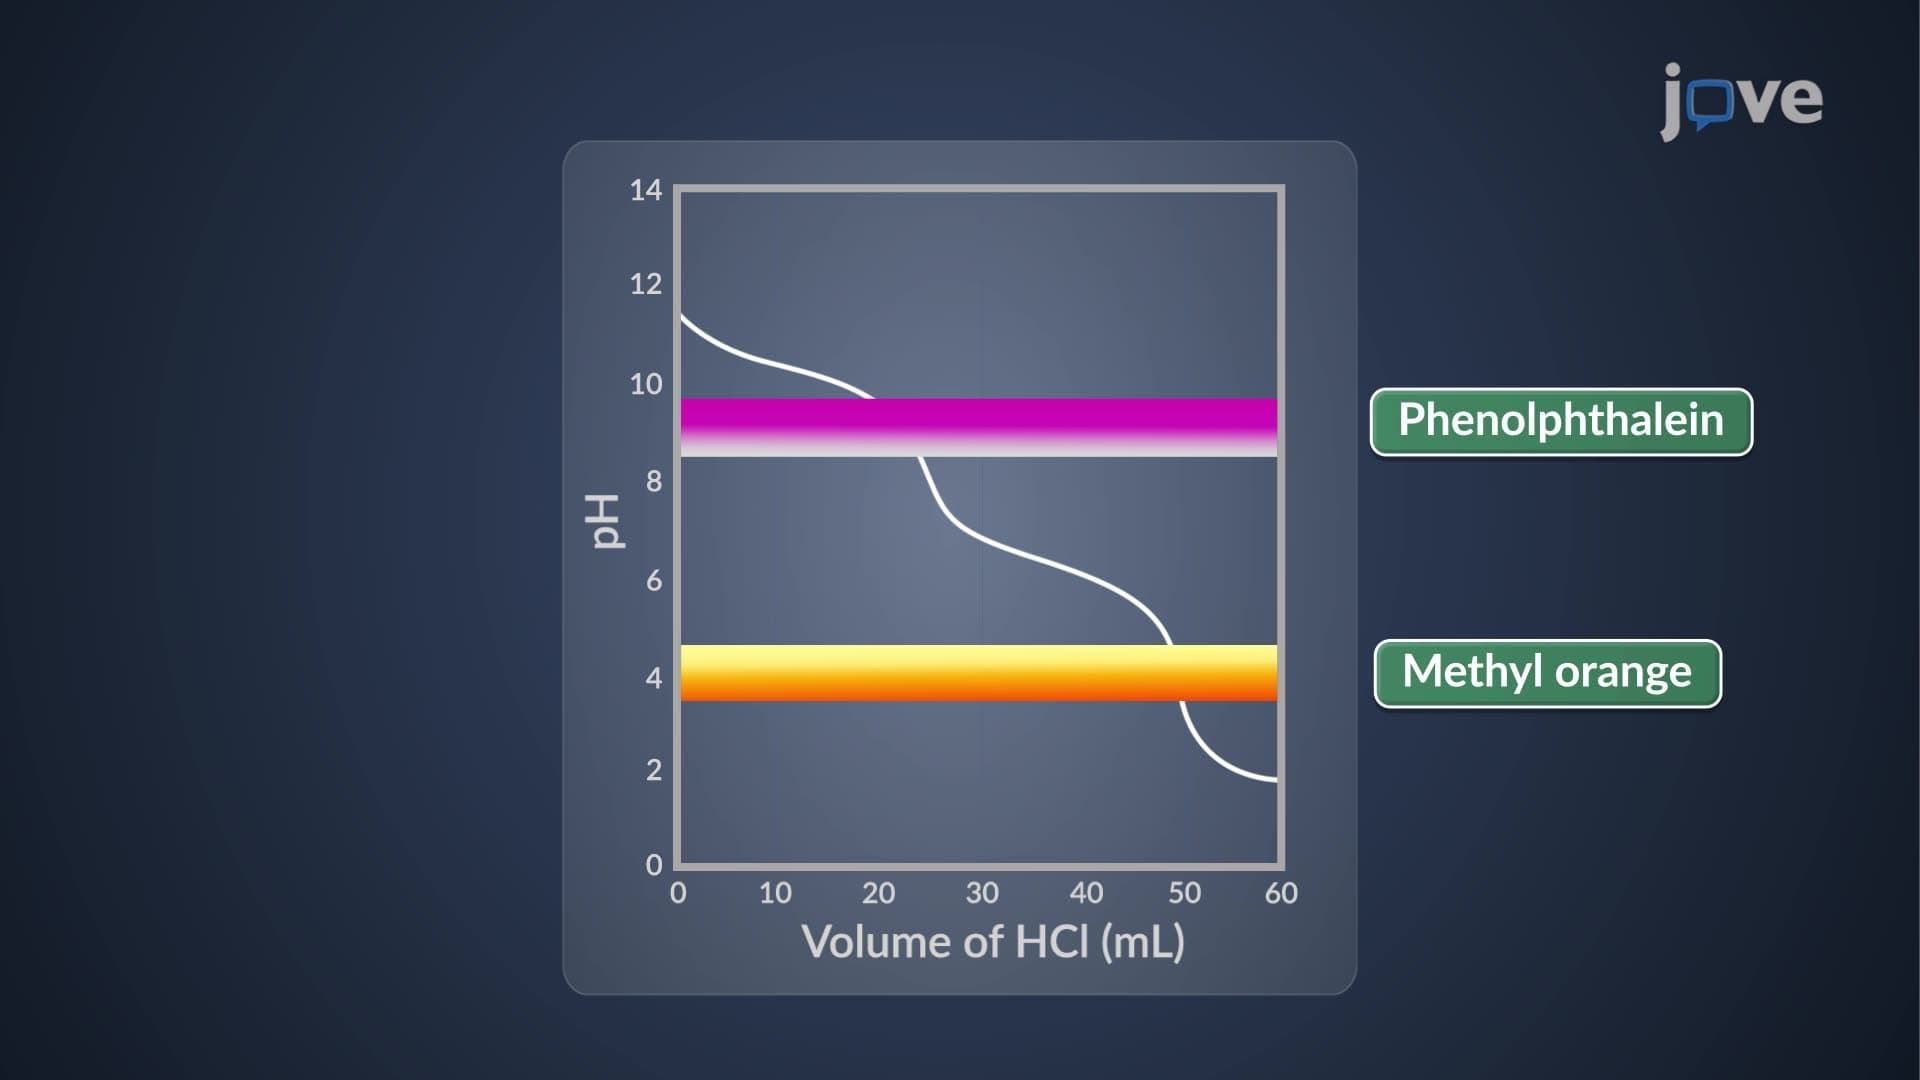
Titration of Polyprotic Base with a Strong Acid
 01:22
Bicarbonate-Carbonic Acid Buffer
 01:24
Diagnosing Acidosis and Alkalosis
First, the pH level is assessed to determine whether the blood pH is normal (7.35–7.45), low (acidosis), or high (alkalosis).
Next, the PCO2 and HCO3− values are examined to...
 01:30
Acute Respiratory Failure-III