Related Experiment Video
Updated: Jul 28, 2026

Continuous Manual Exchange Transfusion for Patients with Sickle Cell Disease: An Efficient Method to Avoid Iron Overload
Published on: March 14, 2017
Safety and efficacy of total dose iron dextran administration in patients on home renal replacement therapies
J A Sloand1, M A Shelly, A L Erenstone
1Department of Medicine, Highland Hospital, University of Rochester School of Medicine and Dentistry, New York 14620, USA.

Objective:
To determine the safety and efficacy of intravenous total dose iron (TDI) replacement in patients treated with home renal replacement therapy.
Design:
Prospective open-label study on end points in the population studied.
Setting:
Institutional outpatient home dialysis program.
Patients:
The study included 20 end-stage renal disease (ESRD) patients, performing chronic peritoneal or home hemodialysis, with iron deficiency defined as ferritin < 100 ng/mL and/or an iron saturation < 20%.
Intervention:
The total dose of iron dextran was calculated and infused at a rate not exceeding 6 mg/min. Hemoglobin, hematocrit, iron studies, and liver function tests (LFTs) were obtained before and 3 to 4 weeks after TDI infusion. Hematocrit of patients failing to achieve an increase in Hct over this period was re-examined 2 to 4 weeks later looking for a delayed response.
Main Outcome Measures:
Primary end points for efficacy were changes in Hct, ferritin, and iron saturation. Toxicity was measured as reported immediate and delayed symptoms and elevated transaminases and/or alkaline phosphatase levels.
Results:
A median iron dose of 1000 mg (range, 325-1500 mg) was administered. The infusions were generally well tolerated. Clinical adverse effects were seen in 2 patients weighing less than 50 kg. No increase in LFT results was seen. Hematocrit increased 2.2% (95% CI, 0.5%-3.9%) from 29.0% to 31.2% (p = 0.01) within 4 weeks of infusion. Significant increases also occurred in iron saturation (from 13% to 22%, p = 0.001) and ferritin (from 234 to 305 ng/mL, p = 0.008). Among the 9 patients who did not respond with a significant increase in Hct, 2 had a delayed response, increasing the overall response from 63% at 4 weeks to 71%, 8 weeks after TDI. Inadequate erythropoietin dosing and low-grade infectious/inflammatory disorders may have contributed to a poor response in several patients.
Conclusion:
Total dose iron is a safe and effective means of restoring iron and erythropoietic response in ESRD patients weighing more than 50 kg who receive their renal replacement therapy at home.


Related Concept Videos
 01:11
Renal Failure: Dose Adjustments
Reduced renal clearance and elimination rate are common outcomes of renal impairment. These alterations lead to a prolonged elimination half-life and an altered apparent volume of distribution for drugs. As a result, dosage adjustments are typically necessary to maintain optimal drug levels in the body.
However, dosage adjustments...
 01:25
Drug Dosing in Renal Diseases: Dose Adjustments Based on Drug Clearance and Elimination Rate Constant
 01:30
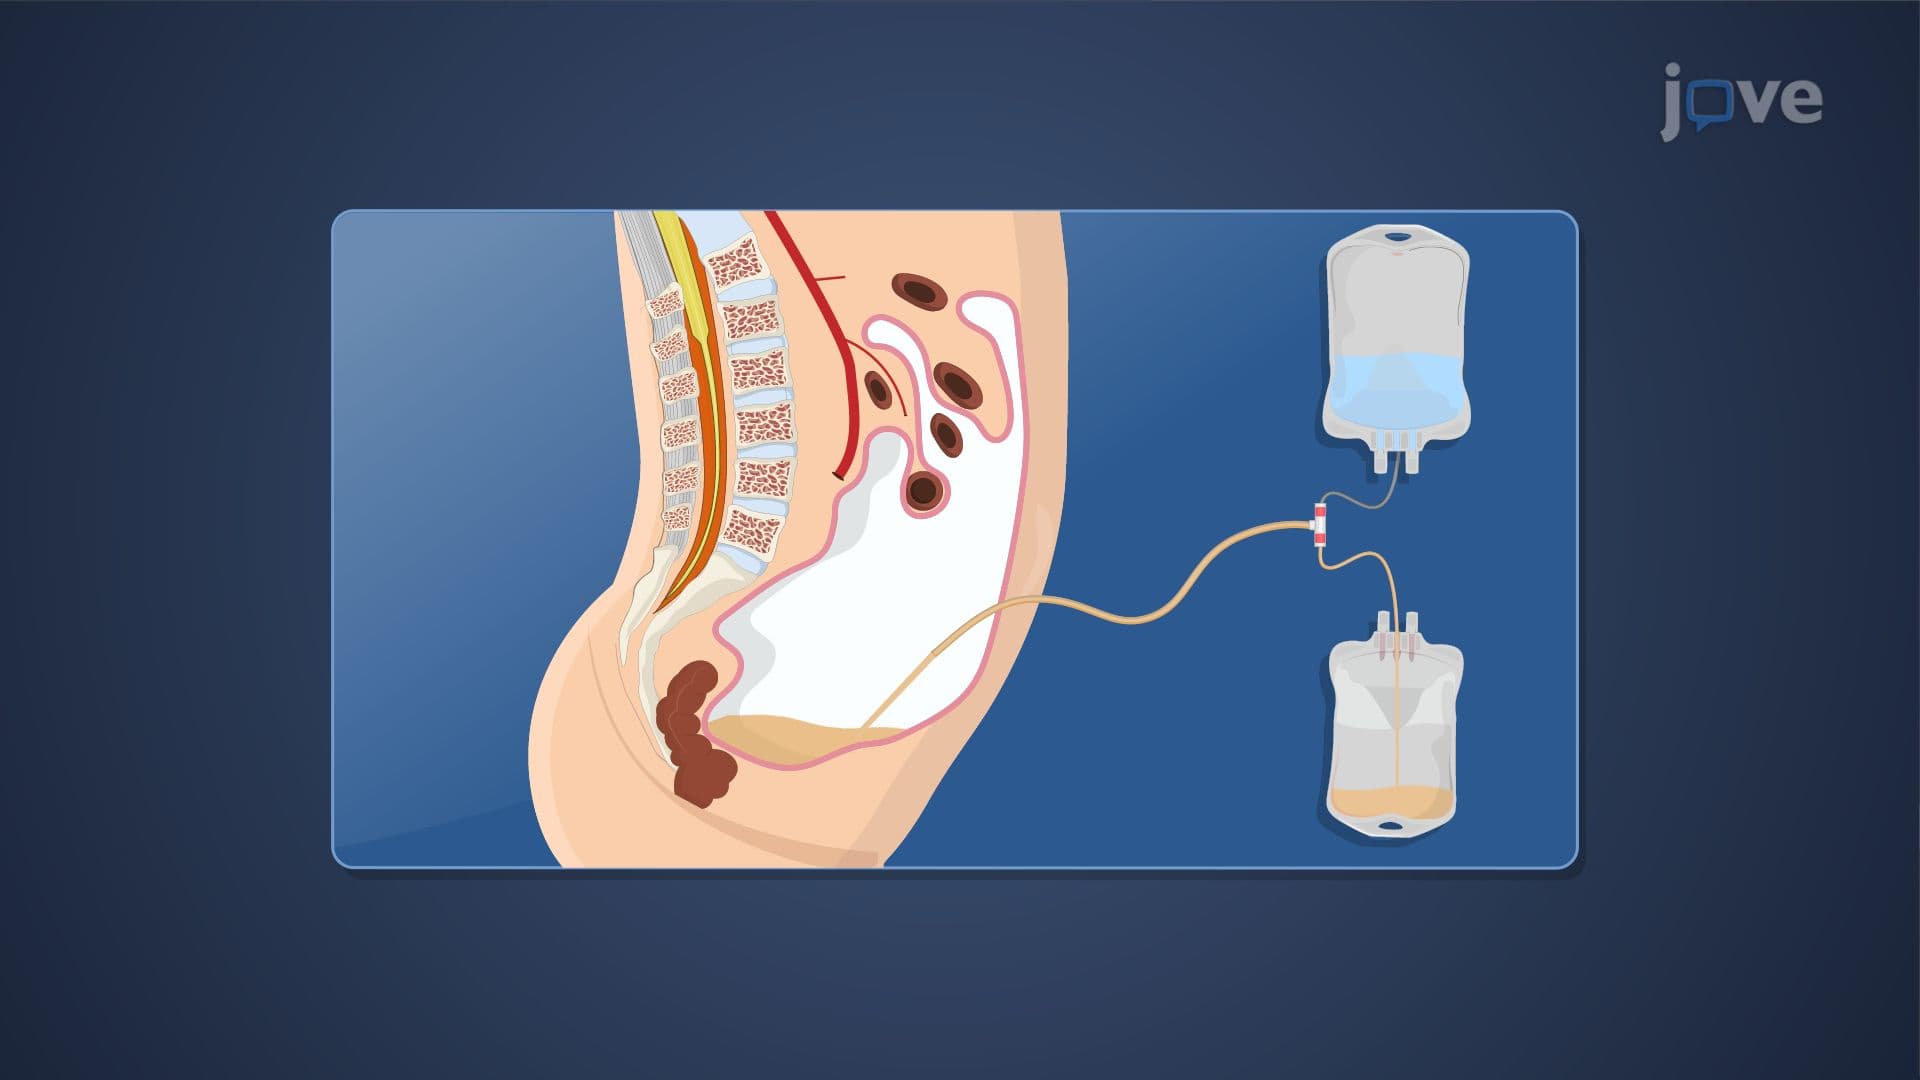
Extracorporeal Removal of Drugs: Peritoneal Dialysis and Hemodialysis
 01:25
Extracorporeal Removal of Drugs: Hemoperfusion and Hemofiltration
 01:26
Extracorporeal Removal of Drugs: Continuous Renal Replacement Therapy
 01:30
Continuous Renal Replacement Therapy