Related Experiment Video
Updated: Aug 13, 2026


Benefits of Cardiac Resynchronization Therapy in an Asynchronous Heart Failure Model Induced by Left Bundle Branch Ablation and Rapid Pacing
Published on: December 11, 2017
Electrocardiographic changes after alcohol septal ablation in hypertrophic obstructive cardiomyopathy
J Kazmierczak1, Z Kornacewicz-Jach, M Kisly
1Department of Cardiology, Pomeranian Medical School, Szczecin, Poland.

Insights
Alcohol septal ablation for hypertrophic obstructive cardiomyopathy (HOCM) causes significant ECG changes, including new Q waves and bundle branch block. These findings highlight important electrocardiographic alterations post-procedure.
Area of Science:
- Cardiology
- Interventional Cardiology
- Electrophysiology
Background:
- Hypertrophic obstructive cardiomyopathy (HOCM) is a condition characterized by left ventricular hypertrophy and outflow tract obstruction.
- Alcohol septal ablation is a minimally invasive procedure used to treat symptomatic HOCM by inducing necrosis of the septal myocardium.
Purpose of the Study:
- To document acute and mid-term electrocardiographic (ECG) changes following alcohol septal ablation in HOCM patients.
- To correlate these ECG findings with changes in left ventricular outflow tract (LVOT) pressure gradients.
Main Methods:
- Prospective analysis of ECGs (baseline, post-procedure, 6-month follow-up) in nine HOCM patients.
- 24-hour ambulatory ECG monitoring was performed.
- Correlation of ECG parameters with LVOT pressure gradients.
Main Results:
- Most patients exhibited significant ECG alterations, including new Q waves, right bundle branch block, and transient ST segment elevation.
- One patient developed complete atrioventricular block requiring pacing.
- Transient PR interval prolongation and QT/QTc interval prolongation were observed; JT/JTc dispersions were also transiently prolonged.
Conclusions:
- Alcohol septal ablation in HOCM patients induces substantial and varied ECG changes.
- These changes occur despite the ablation of a relatively small septal artery.
- The observed ECG modifications are important considerations for monitoring patients post-ablation.
Objective:
To report acute and mid-term electrocardiographic changes in patients with hypertrophic obstructive cardiomyopathy (HOCM) after alcohol ablation of the first large septal branch of the left anterior descending coronary artery; and to relate electrocardiographic data with the left ventricular outflow tract pressure gradients.
Patients:
Nine consecutive symptomatic patients with HOCM (mean (SD) age 45 (12) years).
Methods:
Analysis of baseline and post-procedure ECGs and 24 hour ambulatory monitoring (up to six months). ECG data were related to left ventricular outflow tract pressure gradients.
Results:
One patient developed complete atrioventricular block requiring permanent pacing. The PR interval was significantly prolonged up to third month after ablation. Immediately after the procedure all patients developed right bundle branch block. At the sixth month of follow up, right bundle branch block was present in four patients. New anterior ST elevation developed immediately after ablation in five of the nine patients, and new Q waves in four. The QRS duration was significantly prolonged immediately after ablation and during follow up. There was significant but transient prolongation of QT-mean and QTc-mean intervals. QT dispersion, QTc dispersion, and JTc-mean interval were not affected. JT and JTc dispersions were transiently prolonged. No serious ventricular arrhythmias were recorded during Holter monitoring, either before or after the procedure. There were no significant correlations between the left ventricular outflow tract pressure gradient and QTc, QT-d, QTc-d, JTc, JT-d, JTc-d, or QRS duration before and after ablation.
Conclusions:
Alcohol septal ablation for HOCM induces significant changes in the resting ECG in most patients, despite the occlusion of a relatively small artery. The changes include new Q waves, new bundle branch block, transient anterior ST segment elevation, atrioventricular block, and transient prolongation of QT interval.

Related Concept Videos
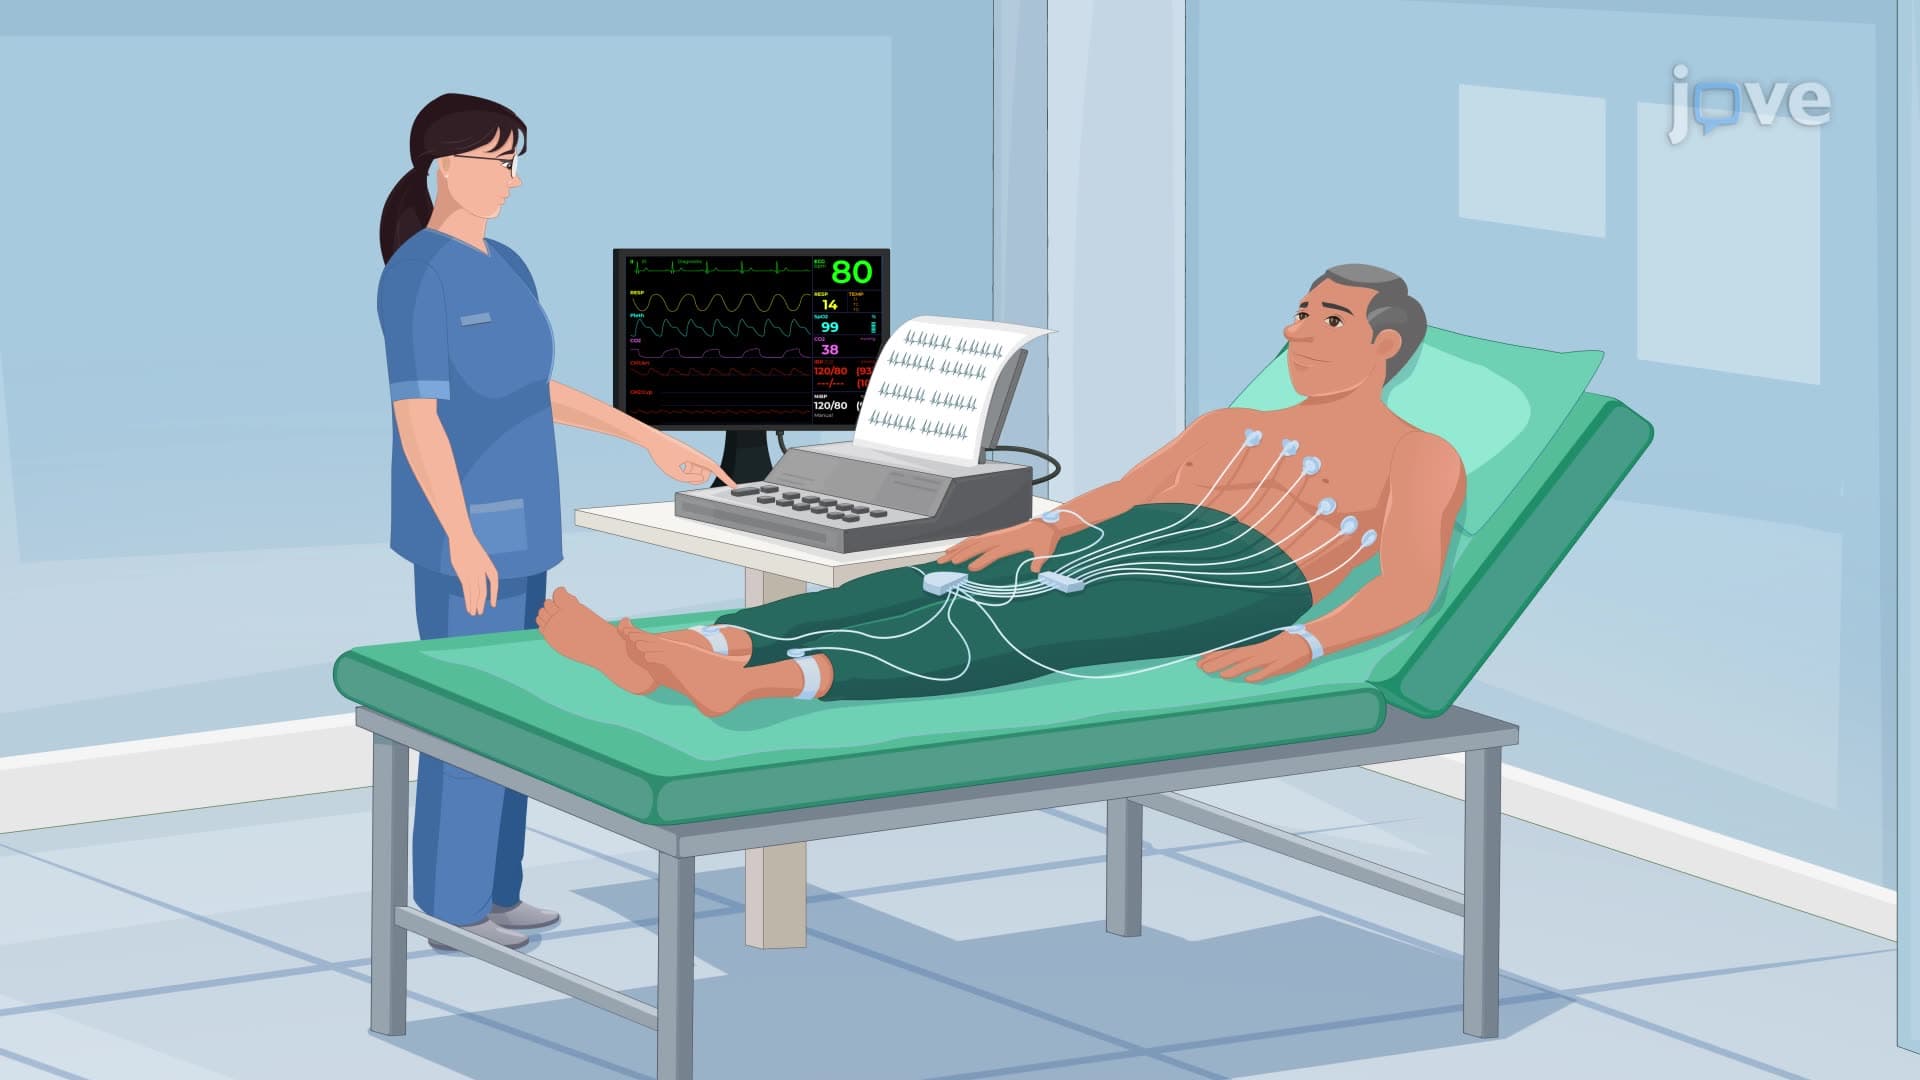 01:29
Electrocardiogram
Three major waveforms are present in a typical ECG recording: the P wave, the QRS complex, and the T...
 01:30
Cardiomyopathy II: Dilated Cardiomyopathy
 01:29
Cardiomyopathy III: Hypertrophic Cardiomyopathy
 01:29
Cardiomyopathy IV: Restrictive Cardiomyopathy
 01:29
Cardiomyopathy V: Interprofessional Care
 01:25
ECG Interpretation of Arrhythmias II: Atrial, Junctional and Ventricular Arrhythmias