Related Experiment Video
Updated: Oct 25, 2026
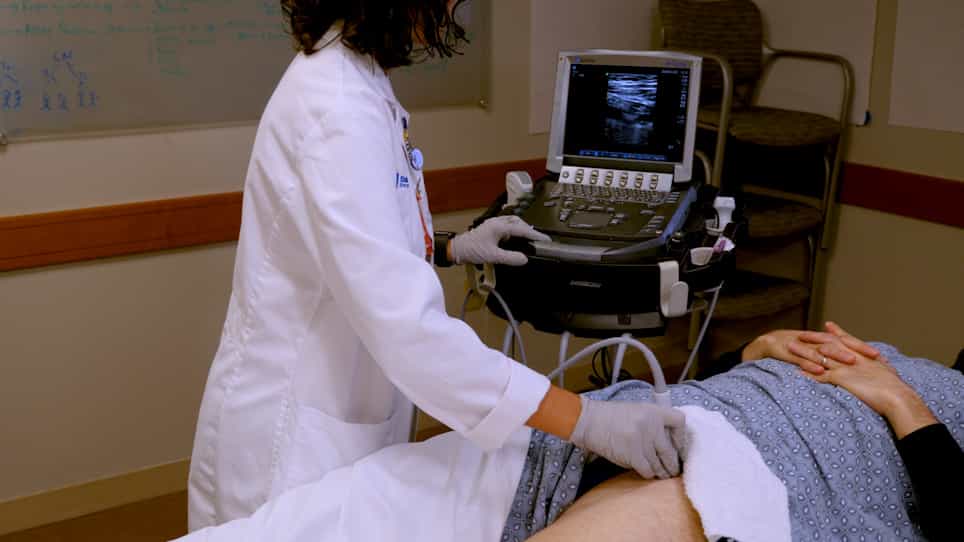
Point-Of-Care Ultrasound Screening for Proximal Lower Extremity Deep Venous Thrombosis
Published on: February 10, 2023
Duplex scanning alone is not sufficient imaging before secondary procedures after lower extremity reversed vein
G J Landry1, G L Moneta, L M Taylor
1Division of Vascular Surgery, Oregon Health Sciences University, Portland, USA.

Purpose:
Duplex surveillance of lower extremity reversed vein bypass grafts (LERVG) is a means of identifying patients at risk for occlusion. The perceived accuracy of duplex scan as a means of identifying stenoses has led many surgeons to perform graft revision on the basis of duplex scan alone. This may result in missing additional lesions that are threatening patency. To assess the role of duplex scan as the sole imaging method before revision of LERVGs, we reviewed consecutive patients undergoing revisions who underwent preoperative arteriography after identification of duplex scan abnormalities.
Methods:
Duplex scan results, operative reports, and preoperative arteriograms for patients undergoing LERVG revision from January 1990 to December 1997 were reviewed. A standard duplex scan surveillance protocol was followed, and attempts were made to survey the entire graft, including inflow and outflow. Duplex scan results were compared with the results of preoperative arteriograms and the operation performed to determine if all significant lesions were identified by means of duplex scan alone.
Results:
Two hundred five LERVG revisions were performed. The 5-year assisted primary patency rate was 91%. In 119 cases (58%), arteriography did not contribute significantly to duplex scan findings. Arteriography significantly contributed to operative planning in 86 cases (42%). In 38 cases (19%), only a low-flow state was identified by means of duplex scan, and a correctable stenosis was identified by means of arteriography. In 48 cases (23%), additional significant lesions corrected at operation were identified by means of arteriography. These included 26 inflow, 16 graft, and 8 outflow lesions. Arteriography was most useful as a means of determining the revision procedure performed when there were inflow lesions (P <.05) or when the proximal anastomosis was to the profunda or superficial femoral arteries (P <.05). All frequently performed bypass graft configurations had some discrepancy between arteriographic and duplex scan findings.
Conclusion:
Available data do not permit prediction of which LERVG are immune from missed lesions in a duplex scan surveillance protocol. This suggests to us that arteriography is mandatory before LERVG revisions.
Related Concept Videos
 01:20
Venous Thrombosis II: Clinical Manifestations and Diagnostic Studies
 01:19
Imaging Studies VII: Vascular Imaging
 01:23
Peripheral Artery Disease V: Postoperative Nursing Management
 01:26
Varicose Veins II: Diagnostic Studies and Interprofessional Care
 01:28
Imaging Studies for Cardiovascular System V: CT
 01:21
Peripheral Arterial Disease II: Clinical Manifestations and Diagnostic Evaluation