Related Experiment Video
Updated: Aug 17, 2026


Reduced Itraconazole Concentration and Durations Are Successful in Treating Batrachochytrium dendrobatidis Infection in Amphibians
Published on: March 14, 2014
Amphotericin B-induced nephrogenic diabetes insipidus in a case of cryptococcemia
Yukio Fujita1, Kei Kasahara, Kenji Uno
1Second Department of Internal Medicine, Nara Medical University, Japan.

Insights
Amphotericin B treatment for cryptococcemia can cause nephrogenic diabetes insipidus, leading to hypokalemia and polyuria. Prompt fluid and potassium replacement can manage this reversible side effect, allowing treatment completion.
Area of Science:
- Nephrology
- Infectious Diseases
- Oncology
Background:
- Malignant lymphoma patients undergoing chemotherapy are susceptible to opportunistic infections like cryptococcemia.
- Amphotericin B is a critical antifungal agent for treating invasive fungal infections.
Observation:
- A 66-year-old woman developed neutropenia and cryptococcemia during chemotherapy.
- Following amphotericin B initiation, she experienced significant polyuria and hypokalemia with stable renal function.
- No evidence of renal tubular acidosis was detected.
Findings:
- The patient was diagnosed with amphotericin B-induced nephrogenic diabetes insipidus, characterized by hypokalemia and polyuria.
- Renal function remained stable throughout the course.
- Discontinuation of amphotericin B led to prompt resolution of polyuria and hypokalemia.
Implications:
- Amphotericin B can induce reversible nephrogenic diabetes insipidus, a notable side effect.
- Vigorous water and potassium management are crucial for tolerating amphotericin B therapy.
- Close monitoring of fluid balance and renal function is essential during treatment.
Abstract:
A 66-year-old woman with malignant lymphoma became neutropenic during chemotherapy and developed cryptococcemia. After amphotericin B had been commenced, she developed significant hypokalemia and polyuria, though her renal function remained stable. The laboratory findings showed no evidence of renal tubular acidosis. With vigorous water and potassium replacement, amphotericin B had been continued until the cumulative dose reached 2.5 g. After the cessation of amphotericin B, the hypokalemia and polyuria resolved promptly. Based on theses findings, she was diagnosed as nephrogenic diabetes insipidus with hypokalemia and without renal tubular acidosis due to amphotericin B. This complication is usually reversible, and vigorous water and potassium replacement may allow completion of treatment by amphotericin B, though careful monitoring of body water balance and renal function is of importance.
Related Concept Videos
 01:27
Cryptococcal Meningitis
 01:15
Antifungal Agents
 01:28
Fungal Phylum Microsporidia
 01:28
Diabetic Nephropathy
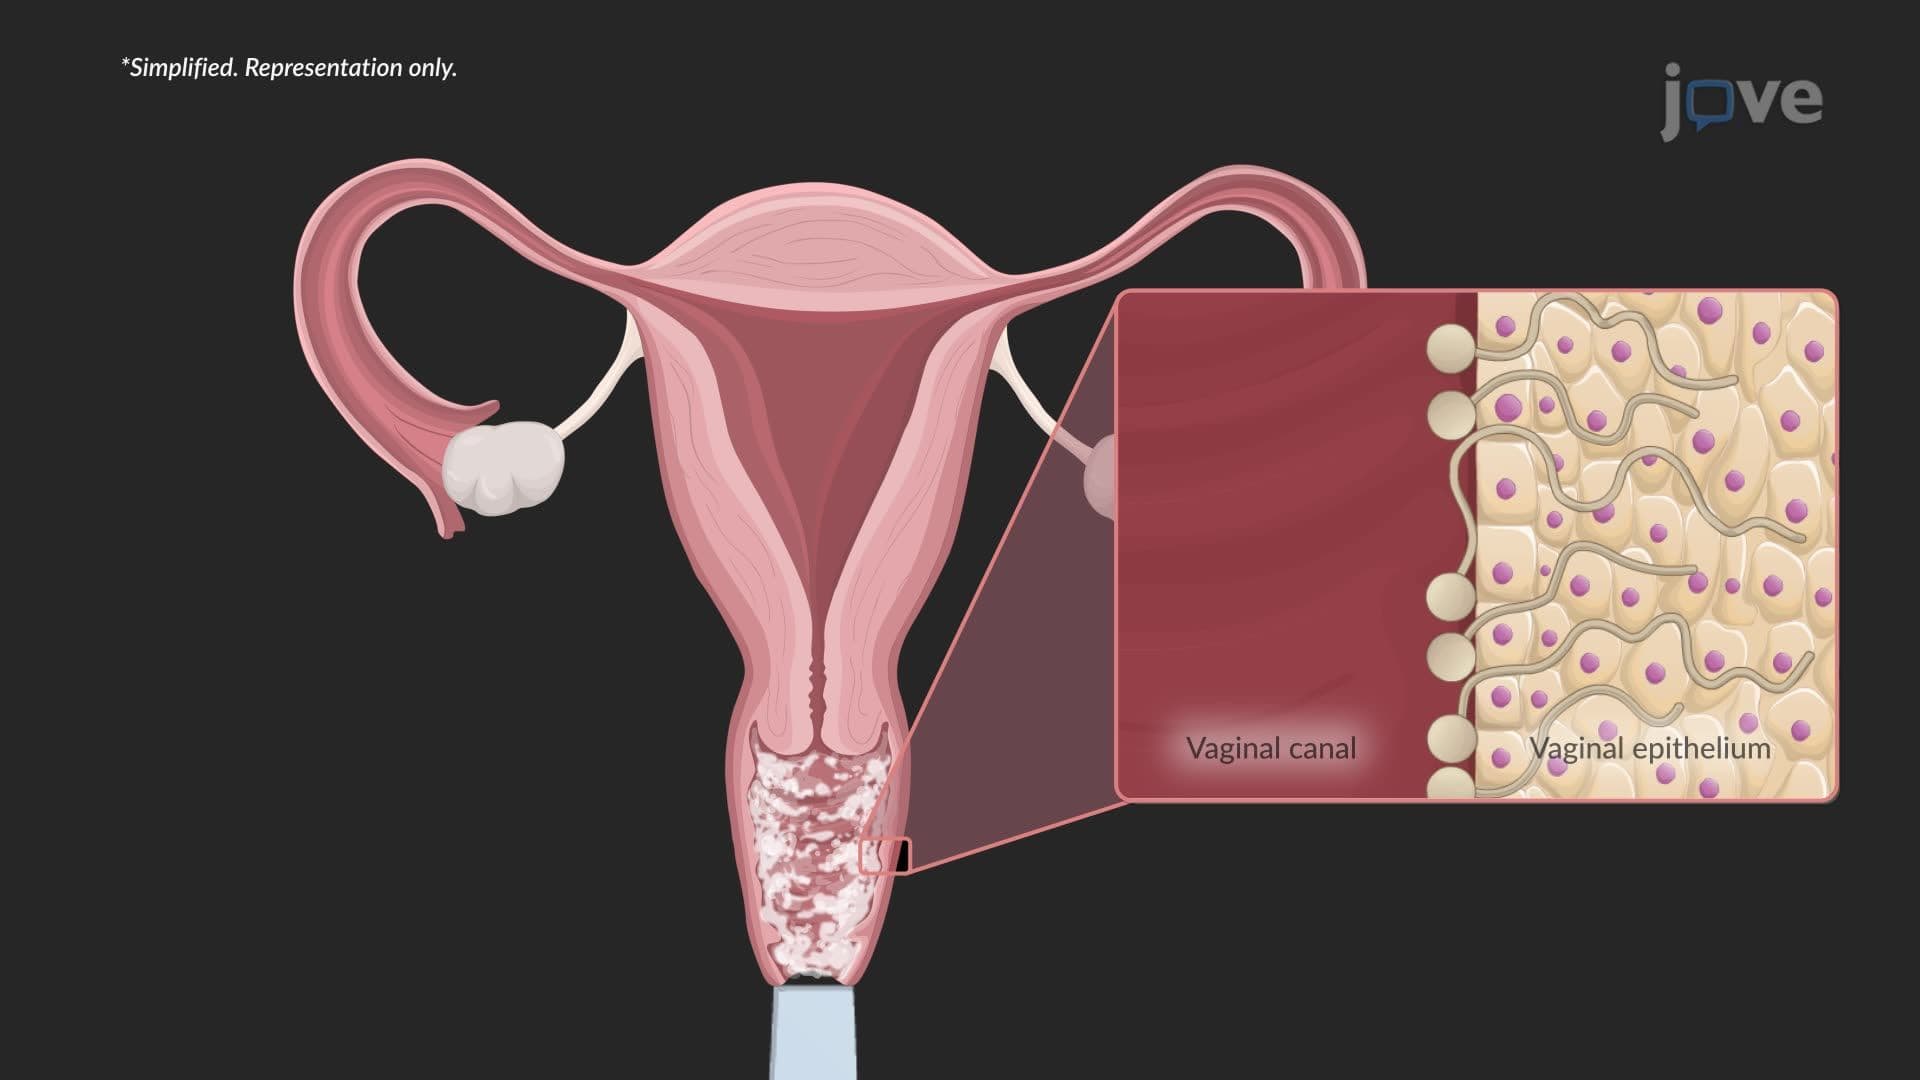 01:20
Candidiasis
 01:29
Pulmonary Tuberculosis I
Causative Organism
The primary infectious agent causing tuberculosis is Mycobacterium tuberculosis, a slow-growing, acid-fast, aerobic rod that exhibits sensitivity to heat and ultraviolet light. Instances of Mycobacterium bovis and Mycobacterium avium contributing to the development of TB infection are rare.
Mode of...