Related Experiment Video
Updated: Aug 8, 2026


Tumor Engraftment in a Xenograft Mouse Model of Human Mantle Cell Lymphoma
Published on: March 30, 2018
Large cleaved and immunoblastic lymphoma may represent two distinct clinicopathologic entities within the group of
Pascale De Paepe1, Ruth Achten, Gregor Verhoef
1Department of Pathology, Ghent University Hospital, Ghent, Belgium. pascale.depaepe@ugent.be

Insights
Immunohistochemistry for classifying diffuse large B-cell lymphoma (DLBCL) into germinal center B-cell-like (GCB) and non-GCB subgroups lacks prognostic significance. However, this classification helps characterize distinct clinicopathologic entities within DLBCL.
Area of Science:
- Hematology
- Oncology
- Immunopathology
Background:
- Diffuse large B-cell lymphoma (DLBCL) classification impacts patient prognosis.
- The prognostic value of immunohistochemistry (IHC) for subdividing DLBCL into germinal center B-cell-like (GCB) and non-GCB subgroups is debated.
- Understanding distinct clinicopathologic entities within DLBCL is crucial for effective treatment strategies.
Purpose of the Study:
- To evaluate the prognostic significance of subdividing DLBCL into GCB and non-GCB subgroups using IHC.
- To investigate if these subgroups represent distinct clinicopathologic entities with unique phenotypes, genetic abnormalities, and clinical characteristics.
- To assess the prognostic implications of specific morphological subtypes and genetic alterations in DLBCL.
Main Methods:
- Morphological review and subdivision of 153 DLBCL samples into large cleaved, immunoblastic, and not otherwise specified categories.
- Establishment of GCB and non-GCB immunohistochemical profiles for all DLBCL samples.
- Investigation of chromosomal translocations and rearrangements involving BCL2, BCL6, and MYC genes.
Main Results:
- Subdivision of DLBCL into GCB and non-GCB immunophenotypic profiles did not show prognostic significance.
- CD10 expression predicted a favorable outcome, while high bcl-2 expression and BCL6 rearrangement were adverse predictors of disease-free survival (DFS).
- Large cleaved DLBCL correlated with GCB profile, CD10 expression, BCL2 rearrangement, younger age, and lower International Prognostic Index, but lacked prognostic significance. Immunoblastic morphology indicated a non-GCB profile and predicted unfavorable DFS.
Conclusions:
- Immunohistochemical subdivision of DLBCL into GCB and non-GCB subgroups is not prognostically significant.
- This classification aids in characterizing two distinct clinicopathologic entities within DLBCL, previously recognized in the Working Formulation.
- Morphological features like immunoblastic subtype are significant predictors of outcome in DLBCL.
Purpose:
The reliability of immunohistochemistry for subdividing diffuse large B-cell lymphomas (DLBCL) into germinal center B-cell-like (GCB) and non-GCB prognostic subgroups is debated. In this study we evaluated the prognostic significance of such subgrouping on a series of 153 DLBCL patients. Furthermore, we investigated whether both subgroups could comprise clinicopathologic entities recognized by their morphology and characterized by a distinct phenotype, specific genetic abnormalities, and clinical characteristics.
Patients And Methods:
All samples from patients were reviewed and morphologically subdivided into large cleaved, immunoblastic, and not otherwise specified DLBCL. GCB and non-GCB immunohistochemical profiles were established. The presence of chromosomal translocations involving BCL2, BCL6, and MYC and/or rearrangements of these genes was investigated.
Results:
Subdividing DLBCL with either a GCB or non-GCB immunophenotypic profile was not of prognostic significance. Nevertheless, CD10 expression was a predictor of favorable outcome, whereas high bcl-2 expression and BCL6 rearrangement were adverse predictors of disease-free survival. Interestingly, large cleaved DLBCL was clearly associated with a GCB immunophenotypic profile, CD10 expression, BCL2 rearrangement, age younger than 60 years, and low to low/intermediate International Prognostic Index risk, but was not of prognostic significance. In contrast, immunoblastic morphology was associated with a non-GCB profile and was a significant predictor of unfavorable DFS.
Conclusion:
Subdividing DLBCL into subgroups based on their immunohistochemical profile was not of prognostic significance. Nevertheless, it allowed the additional characterization of two lymphoma subgroups previously recognized in the Working Formulation. Both correspond to two distinct clinicopathologic entities within the DLBCL.

Related Concept Videos
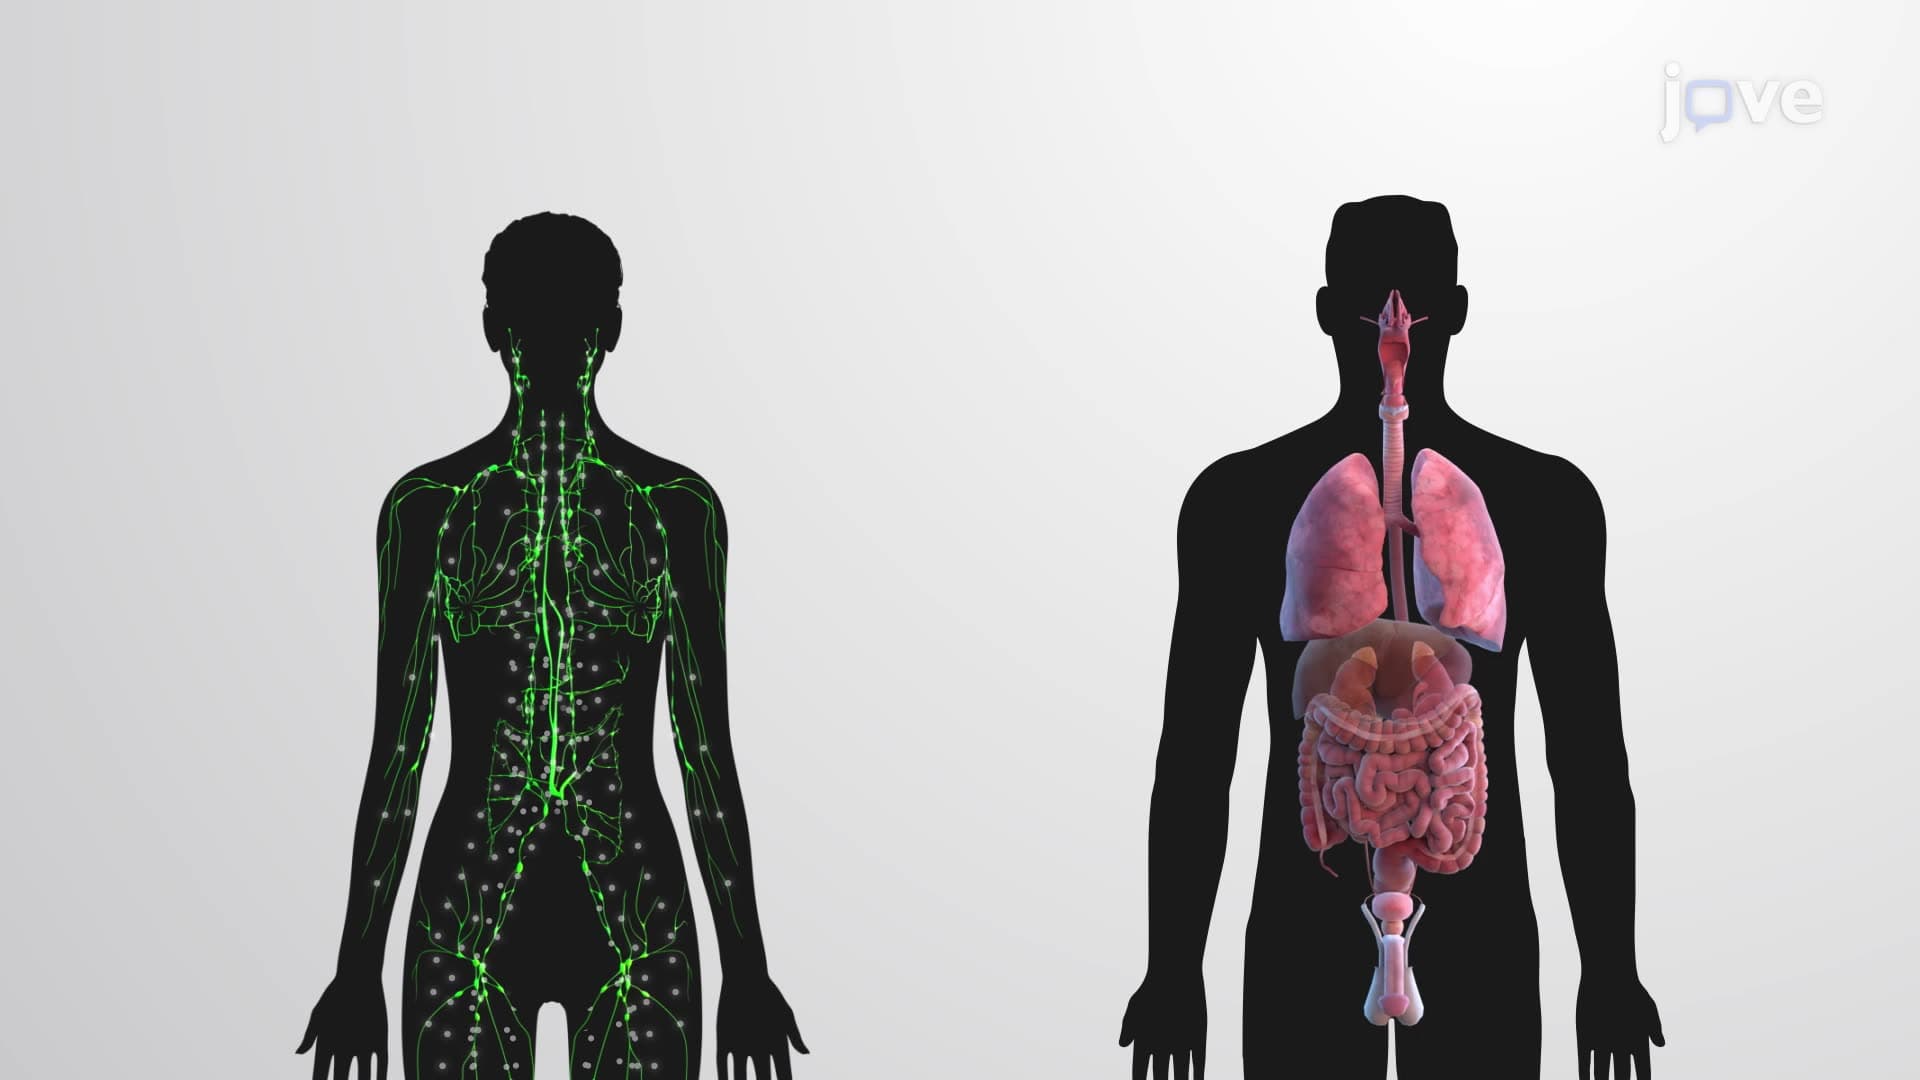 01:18
Lymphoid Cells and Tissues
Lymphoid cells consist of various types of immune system cells. These include B and T lymphocytes, which are responsible for producing antibodies and killing infected cells, respectively. Dendritic cells act as messengers between the innate and adaptive...
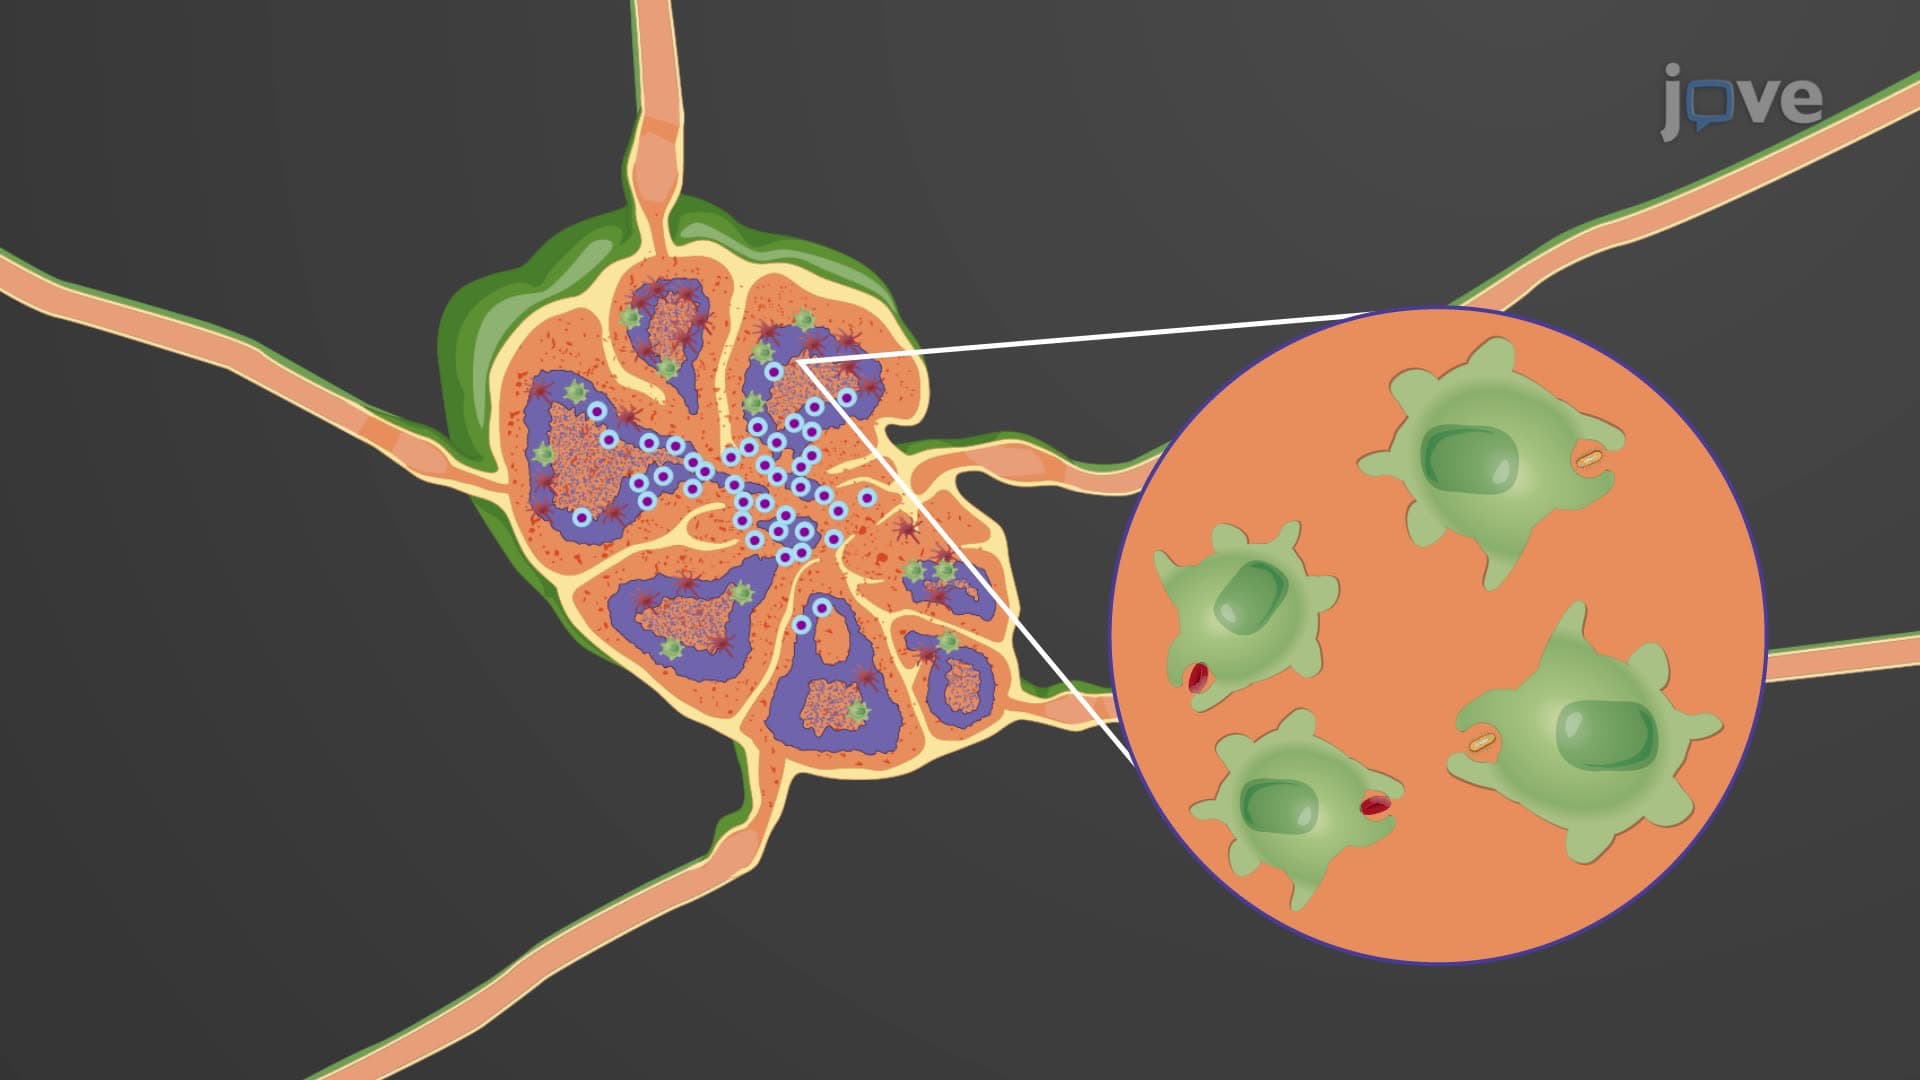 01:15
Secondary Lymphoid Organs
The spleen is a vital organ in the lymphatic system, nestled in the upper left side of the abdomen. It is composed of two primary regions: the red pulp and the white pulp, each having distinct functions. The red pulp performs a significant role in blood filtration. It efficiently purges the blood of old or damaged red blood cells and...
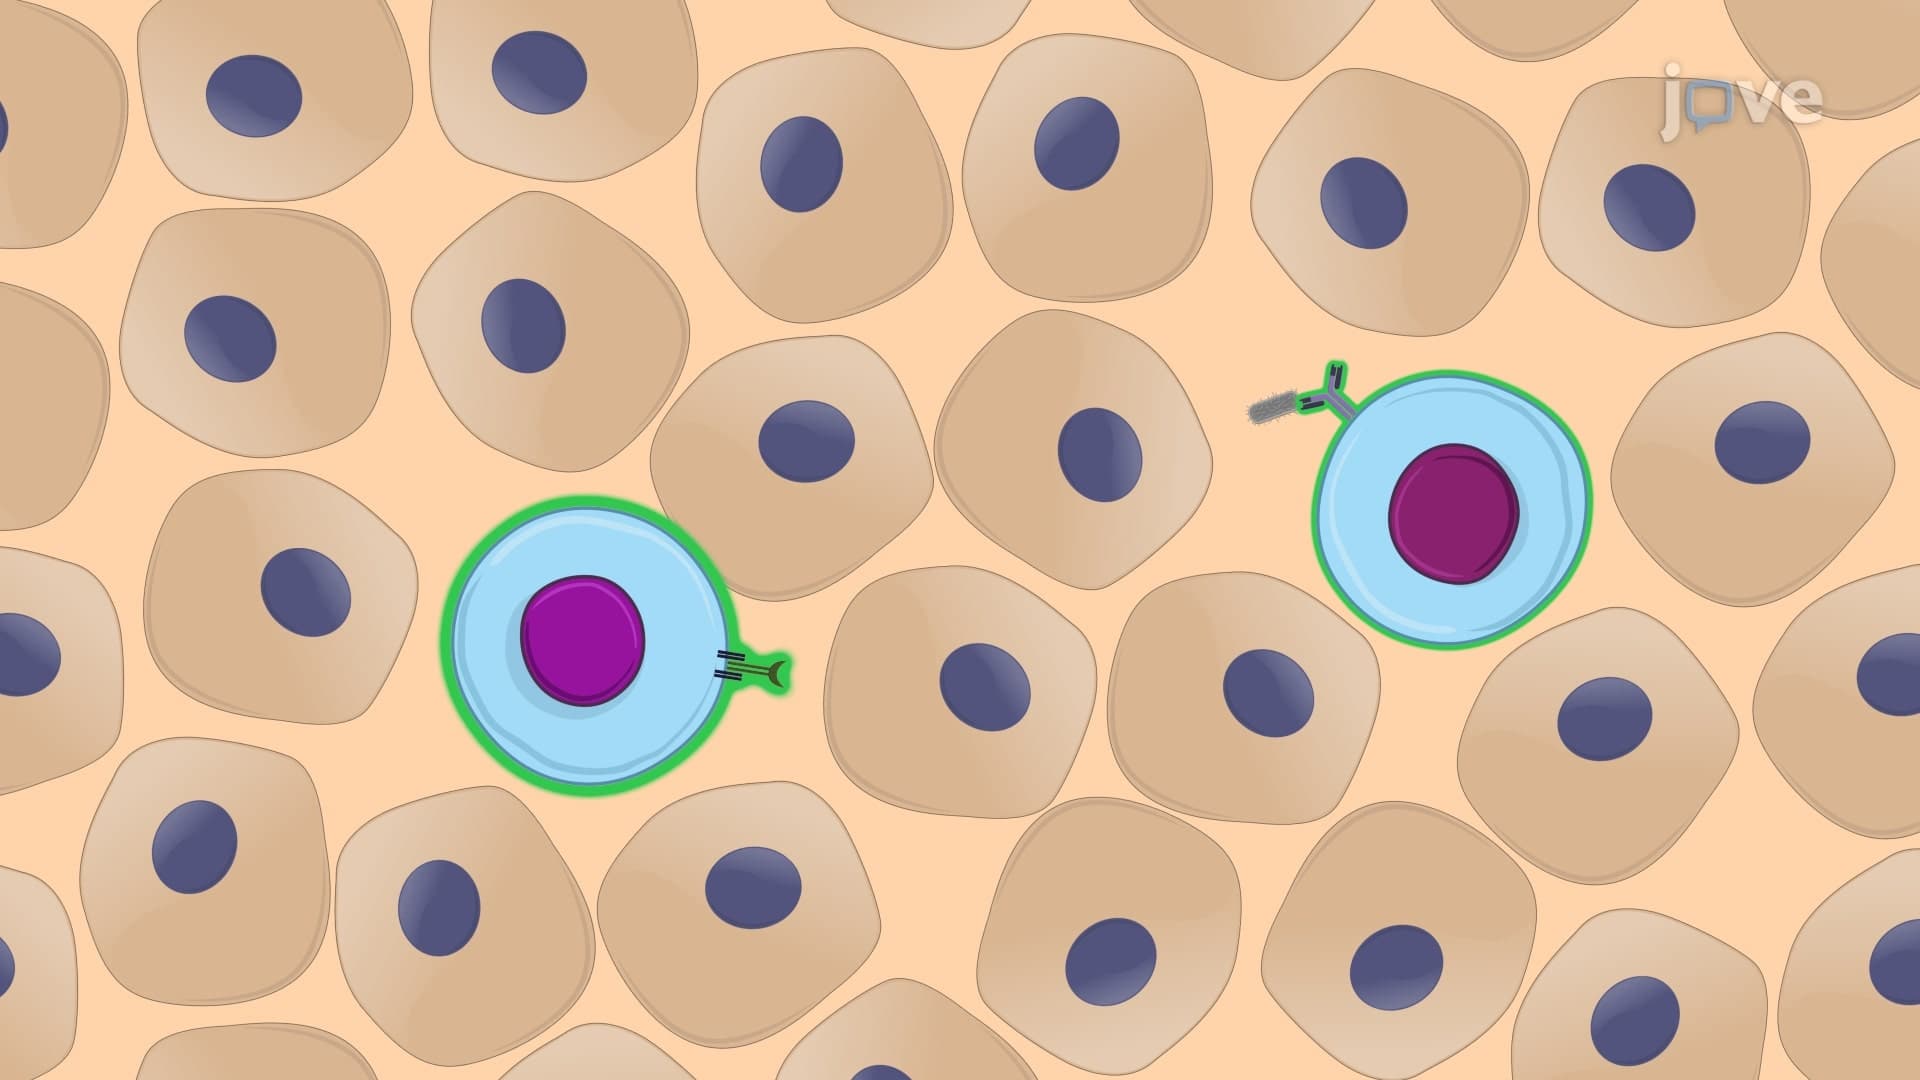 01:20
Special Features of Adaptive Immunity
The primary cell types involved in adaptive immunity are T cells and B cells. Each type has a unique role in defending the body against pathogens. T cells are responsible for cell-mediated immunity. They identify and eliminate infected cells directly,...
 01:23
Cells of the Adaptive Immune Response
 01:24
B Cell Activation and Differentiation
When naive B cells encounter a specific antigen that can bind to the B cell receptor (BCR) on their surface, they undergo sensitization to respond to the antigen's presence. Sensitization begins with...