Related Experiment Video
Updated: Jul 15, 2026
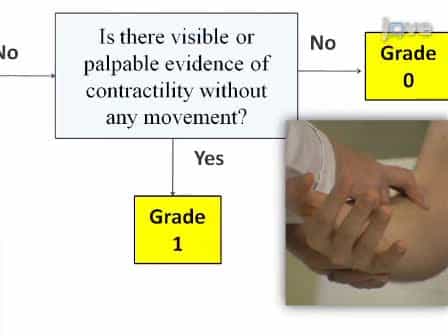

Manual Muscle Testing: A Method of Measuring Extremity Muscle Strength Applied to Critically Ill Patients
Published on: April 12, 2011
ICU-acquired weakness
William D Schweickert1, Jesse Hall
1Pulmonary/Critical Care, Department of Medicine, University of Chicago, 5841 S. Maryland Avenue, MC 6026, Chicago, IL 60657, USA. jhall@medicine.bsd.uchicago.edu.

Insights
Acquired neuromuscular disorders are common in critically ill patients. Early identification and management of risk factors like inflammation and immobility can improve outcomes and reduce ventilator dependence.
Area of Science:
- Critical care medicine
- Neurology
- Intensive care unit (ICU) management
Background:
- Acquired neuromuscular disorders, including critical illness polyneuropathy (CIP) and critical illness myopathy (CIM), are highly prevalent in patients requiring prolonged mechanical ventilation and critical care.
- Traditional diagnostic methods involve invasive electrophysiologic investigations and muscle biopsies.
- ICU-acquired weakness is a significant complication, contributing to long-term morbidity in survivors, particularly those with ARDS, and is linked to prolonged ventilator dependence.
Purpose of the Study:
- To review the current understanding of acquired weakness syndromes in the ICU.
- To highlight the shift towards non-invasive bedside assessments for diagnosing these conditions.
- To identify key risk factors associated with the development of ICU-acquired weakness.
Main Methods:
- Review of observational studies focusing on patients receiving critical care support.
- Discussion of diagnostic evolution from invasive techniques (electrophysiology, biopsy) to standardized bedside neuromuscular examinations.
- Multivariate analysis to identify risk factors for ICU-acquired weakness.
Main Results:
- Acquired neuromuscular disorders are extremely common in critically ill patients.
- Bedside neuromuscular examinations are emerging as a viable alternative to invasive diagnostic methods.
- Key risk factors for ICU-acquired weakness include severe systemic inflammation, corticosteroid and neuromuscular blocking agent use, poor glycemic control, and immobility.
Conclusions:
- ICU-acquired weakness is a common and significant syndrome with long-term implications for ARDS survivors.
- Early identification of risk factors is crucial for minimizing the impact of acquired weakness.
- A proactive approach to managing risk factors can potentially reduce ventilator dependence and improve patient outcomes.
Abstract:
Observational studies of patients receiving prolonged mechanical ventilation and other forms of critical care support have determined acquired neuromuscular disorders to be extremely common. Early studies used electrophysiologic investigations to diagnose critical illness polyneuropathy (CIP) and muscle biopsy to confirm critical illness myopathy (CIM). More recent approaches seek to obviate these invasive techniques and build on a standardized bedside neuromuscular examination to identify patients with acquired weakness syndromes. Serial examination in the alert patient may serve as a reasonable prognosticator for most patients. The importance of ICU-acquired weakness syndromes is supported by the observation that muscle wasting and weakness are among the most prominent long-term complications of survivors of ARDS. In addition, a strong association appears to exist between acquired weakness and protracted ventilator dependence, an important determinant of ICU length of stay. Multivariate analysis has identified several risk factors associated with increased incidence for ICU-acquired weakness, including severe systemic inflammation, medications (specifically, corticosteroids and neuromuscular blocking agents), glycemic control, and immobility. We advocate an approach to this common syndrome that identifies risk factors early in the hope of minimizing their impact.
Related Concept Videos
 01:28
Disorders of the Skeletal Muscle
Musculoskeletal disorders
Musculoskeletal disorders involve injuries and conditions affecting the skeletal muscles and associated connective tissues. These disorders can arise from acute biomechanical stresses or chronic overuse and can occur across different age groups. Common injuries include sprains, fractures, and muscular strains, often resulting from...
 01:26
Chemical Synapses
Because chemical synapses depend on the release of neurotransmitter molecules from synaptic vesicles to pass on their signal, there is an approximately one millisecond delay between when the axon potential reaches the presynaptic terminal and when the neurotransmitter leads to opening of postsynaptic ion channels. Additionally, this signaling is...
01:26Chemical Synapses
Because chemical synapses depend on the release of neurotransmitter molecules from synaptic vesicles to pass on their signal, there is an approximately one millisecond delay between when the axon potential reaches the presynaptic terminal and when the neurotransmitter leads to opening of postsynaptic ion channels. Additionally, this signaling is...
 01:29
Acute Kidney Injury III: Clinical Manifestations
 01:22
Myasthenia Gravis ll: Pathophysiology
 01:22
Acute Kidney Injury I: Introduction