Related Experiment Video
Updated: Dec 11, 2025
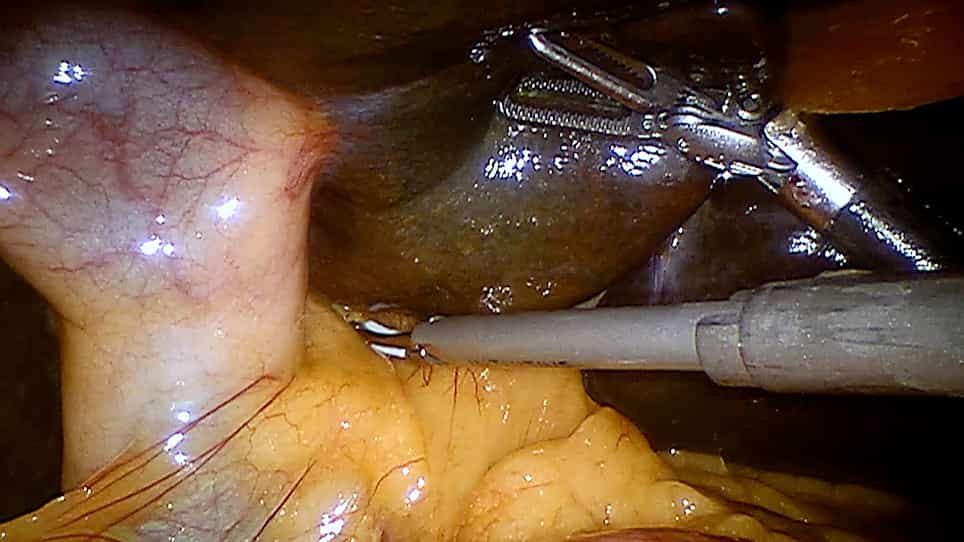
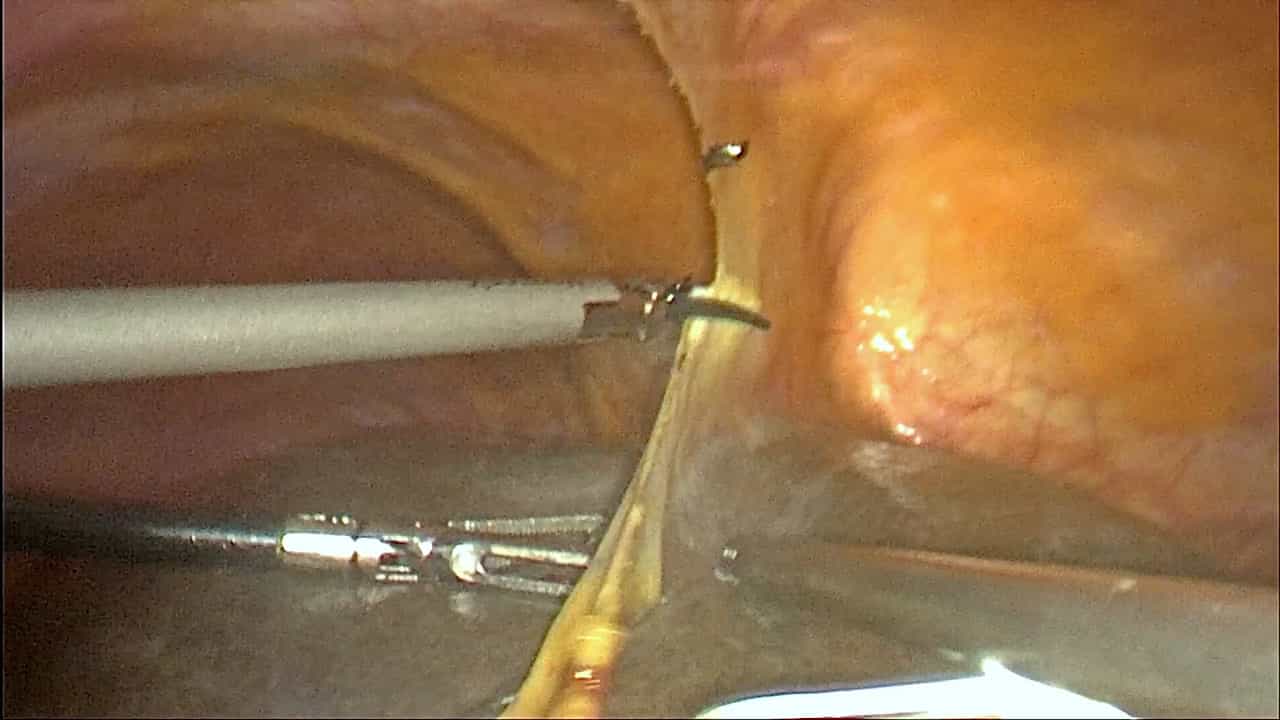
Robotic Taj Mahal Hepatectomy for Hilar Cholangiocarcinoma
Published on: July 14, 2022
[A Case of Unresectable Hilar Cholangiocarcinoma Resected Curatively Through Effective Response to Neoadjuvant
Hiroyuki Imafuji1, Yoichi Matsuo, Yoshinaga Aoyama
1Dept. of Gastroenterological Surgery, Nagoya City University Graduate School of Medical Science.

Insights
A 60-year-old man with jaundice was diagnosed with unresectable hilar cholangiocarcinoma. Chemotherapy led to tumor marker normalization and lymph node shrinkage, enabling curative surgery.
Area of Science:
- Hepatobiliary Surgery
- Gastroenterology
- Medical Oncology
Background:
- Hilar cholangiocarcinoma (CCA) is a challenging malignancy often presenting with advanced disease.
- Metastasis to distant lymph nodes frequently renders tumors unresectable at initial diagnosis.
Observation:
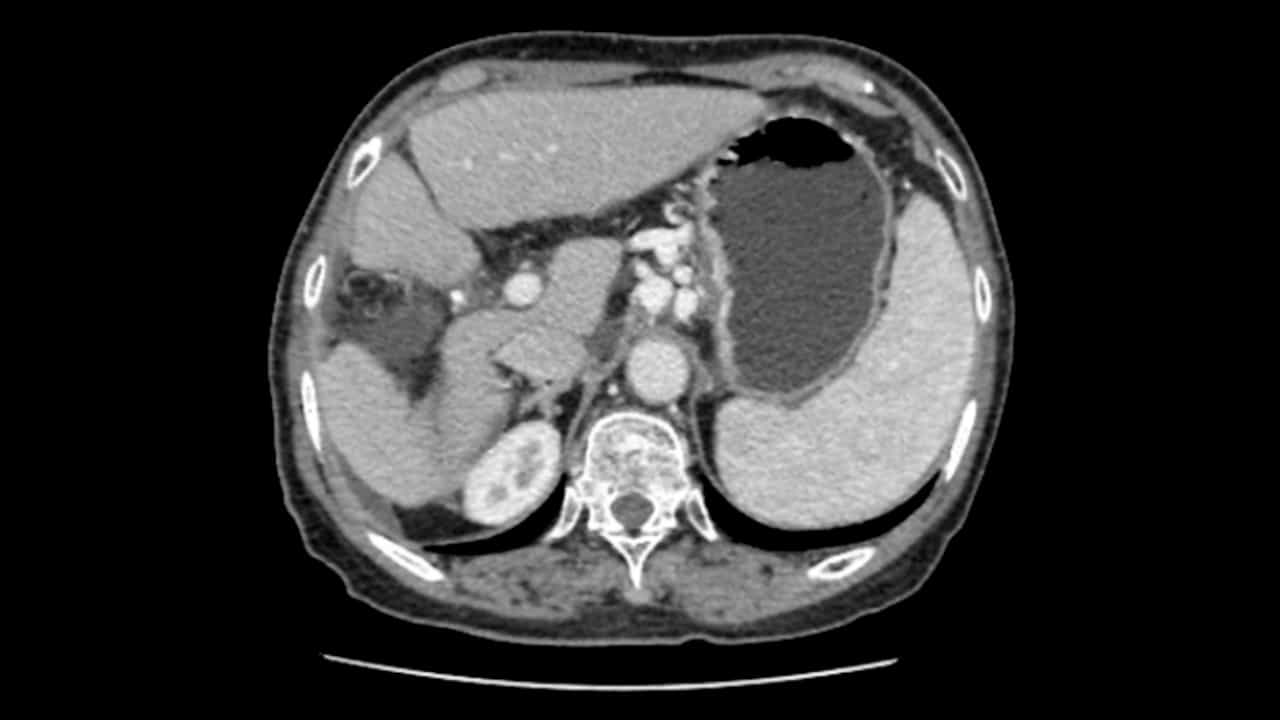
- A 60-year-old male presented with jaundice and imaging revealed hilar bile duct thickening with extensive lymph node (LN) enlargement.
- Endoscopic ultrasonography (EUS) and fine needle aspiration cytology (FNA) confirmed LN metastasis, staging the hilar cholangiocarcinoma as unresectable.
- The patient received gemcitabine/cisplatin (GC) therapy, resulting in normalized tumor markers and reduced LN size within 4 months.
Findings:
- After 12 cycles of GC therapy, cholangioscopy showed improvement in bile duct stenosis, suggesting treatment efficacy.
- The patient subsequently underwent curative resection, including left hepatic caudate lobectomy and extrahepatic cholangectomy.
- Pathological diagnosis post-surgery was pT2aN1(n8a)M0, Stage IIIB, R0, indicating successful removal of all macroscopic tumor.
Implications:
- Neoadjuvant chemotherapy can downstage unresectable hilar cholangiocarcinoma, enabling conversion to a curative surgical approach.
- This case highlights the potential of systemic therapy to improve resectability and long-term outcomes in advanced CCA.
- Adjuvant chemotherapy with S-1 was administered post-surgery to further reduce the risk of recurrence.
Abstract:
A 60's man came to our hospital for jaundice. Contrast-enhanced CT showed irregular thickening of the hilar bile duct, and the lymph nodes(LN)were swollen from the hilar to the abdominal aorta. These LNs showed similar findings in endoscopic ultrasonography(EUS), and fine needle aspiration cytology(FNA)was performed on the enlarged No.13LN to diagnose LN metastasis of hilar cholangiocarcinoma. Since the peri-aortic LN was also markedly enlarged, it was considered to be metastasis, and was diagnosed as unresectable hilar cholangiocarcinoma with distant LN metastasis. When gemcitabine/cisplatin therapy(GC therapy)was started, tumor markers normalized and LN decreased in 4 months. We performed GC therapy for a total of 12 cycles and did not re-exacerbate. Cholangioscopy revealed that bile duct stenosis at the hilar portion had improved. We have determined that curative resection is possible and performed surgery. We confirmed that No.16b1LN was negative by pathological diagnosis during surgery and performed left hepatic caudate lobectomy, extrahepatic cholangectomy, and biliary reconstruction. Diagnosis was pT2aN1(n8a)M0, fStage ⅢB, and pR0. After surgery, adjuvant chemotherapy with S-1 was continued.