Discordance between immunofluorescence and immunohistochemistry C4d staining and outcomes following heart
Takeo Fujino1, Yuto Kumai2, Benjamin Yang1
1Department of Medicine, University of Chicago Medical Center, Chicago, IL, USA.

Insights
Discrepancies in C4d staining between immunofluorescence and immunohistochemistry in heart transplant recipients indicate a higher risk of antibody-mediated rejection and heart failure. Early identification of these discordant results is crucial for patient outcomes.
Area of Science:
- Nephrology
- Immunology
- Cardiology
Background:
- C4d deposition is a key marker for antibody-mediated rejection (AMR) after heart transplantation (HT).
- Two methods, frozen-tissue immunofluorescence (IF) and paraffin immunohistochemistry (IHC), detect C4d.
- The clinical impact of differing IF and IHC C4d results remains unclear.
Purpose of the Study:
- To investigate the clinical significance of discrepancies between IF and IHC C4d staining in heart transplant recipients.
- To assess the association between discordant C4d staining and graft dysfunction, rejection, and long-term outcomes.
Main Methods:
- A retrospective review of 2187 biopsies from 142 HT recipients was conducted.
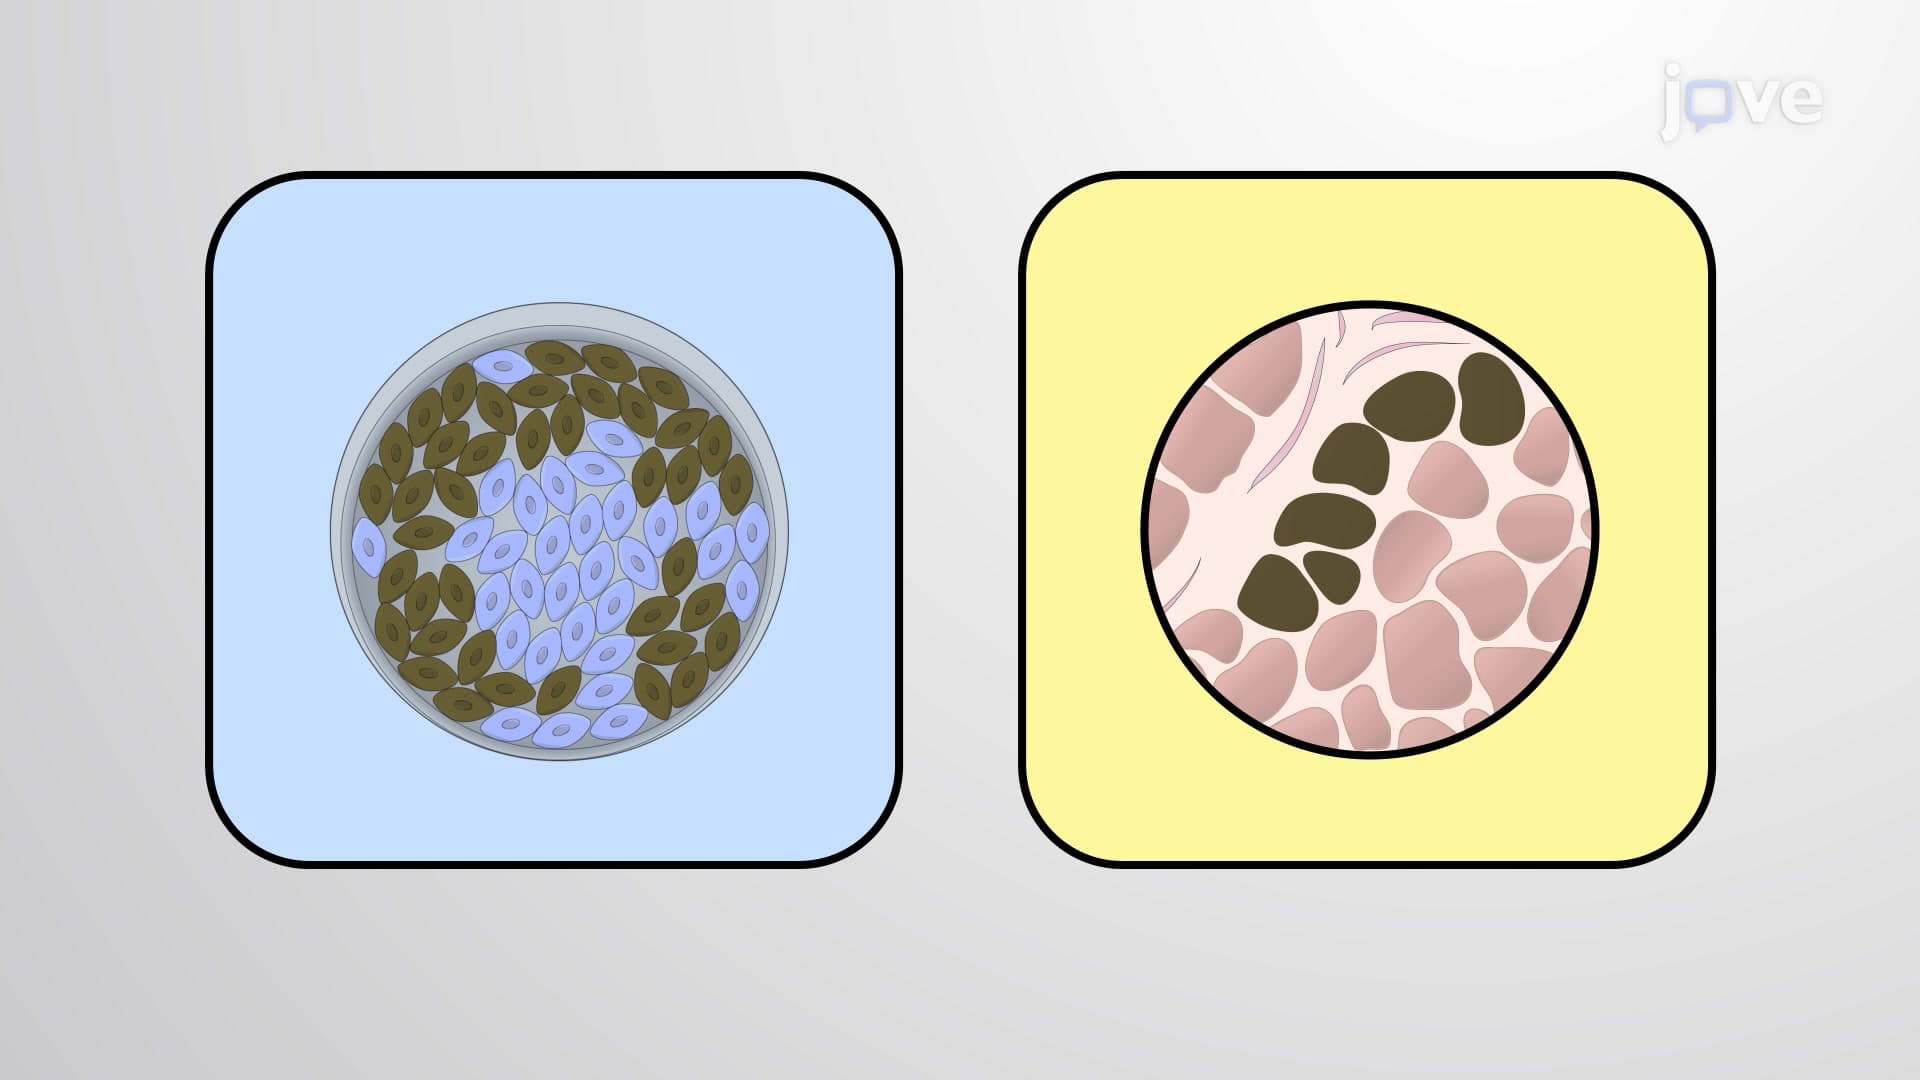
- Patients were categorized into Negative (both IF and IHC negative) and Discordant (IF positive, IHC negative) groups.
- Outcomes including graft dysfunction, cellular rejection, AMR, survival, and freedom from heart failure (HF) were analyzed.
Main Results:
- 32% of patients exhibited discordant C4d staining (IF+/IHC-).
- The Discordant group had significantly higher rates of graft dysfunction (19% vs 5%) and AMR (21% vs 4%) compared to the Negative group.
- Freedom from heart failure at 1 year was significantly lower in the Discordant group (70% vs 96%).
Conclusions:
- Discordant C4d staining (IF+/IHC-) is associated with increased risk of graft dysfunction and AMR post-heart transplantation.
- Patients with discordant C4d results experience worse outcomes, including lower freedom from heart failure.
- These findings highlight the clinical importance of recognizing and managing discrepancies in C4d detection methods.
Background:
Capillary deposition of C4d is an important marker of antibody-mediated rejection (AMR) following heart transplantation (HT). There are two immunopathologic assay methods for detecting C4d: frozen-tissue immunofluorescence (IF) and paraffin immunohistochemistry (IHC). The clinical significance of discrepancy between the results of IF and IHC has not been understood.
Methods And Results:
We reviewed 2187 biopsies from 142 HT recipients who had biopsies with assessment of both IF and IHC staining. Among them, 103 (73%) patients had negative IF and IHC C4d staining (Negative Group) and 32 (23%) patients had positive IF but negative IHC staining (Discordant Group). At the time of positive biopsy, 6 (19%) Discordant patients had graft dysfunction, compared to 5 (5%) Negative patients (p = .022). Cumulative incidence of cellular rejection at 1 year was comparable (31% vs. 29%, p = .46); however, cumulative incidence of AMR was significantly higher in the Discordant group (21% vs. 4%, p = .004). Overall 1-year survival was comparable (90% vs. 96%, p = .24); however, freedom from heart failure (HF) was significantly lower in the Discordant group (70% vs. 96%, p < .001).
Conclusion:
The Discordant group showed higher rates of graft dysfunction, AMR and HF admission than the Negative group.