Related Experiment Video
Updated: Sep 6, 2025

Intraoperative Ultrasound in Spinal Surgery
Published on: August 17, 2022
Comparative intra- and inter-observer reliability of two methods for evaluating intraoperative ultrasonography-based
Huachuan Wu1,2, Guoliang Chen3,4, Xianlong Li3,4
1Department of Orthopaedic Surgery, Innovation Platform of Regeneration and Repair of Spinal Cord and Nerve Injury, The Seventh Affiliated Hospital, Sun Yat-Sen University, Shenzhen, 518107, China. wuhch6@mail2.sysu.edu.cn.

Insights
A new ultrasound method (GVR-B) for evaluating spinal cord hyperechogenicity in degenerative cervical myelopathy (DCM) shows improved reliability over the standard method (GVR-A). This advancement aids in predicting neurological recovery after decompression surgery.
Area of Science:
- Neurosurgery
- Spinal Cord Imaging
- Degenerative Cervical Myelopathy (DCM)
Background:
- Spinal cord hyperechogenicity intensity is a potential predictor of neurological recovery in DCM patients post-decompression.
- The traditional Gray Value Ratio (GVR) method's accuracy is limited by various influencing factors.
- Intraoperative ultrasound (IOUS) is used during French-door laminoplasty for spinal cord visualization.
Purpose of the Study:
- To evaluate and compare the inter-observer and intra-observer reliability of two distinct GVR methods for assessing spinal cord hyperechogenicity.
- To identify a more reliable ultrasound-based method for spinal cord decompression assessment in DCM patients.
- To establish a robust protocol for prognostic prediction in DCM.
Main Methods:
- Twenty-eight DCM patients undergoing French-door laminoplasty were studied.
- Two GVR calculation methods were employed: GVR-A (using spinal cord gray value and normal spinal cord gray value) and GVR-B (using spinal cord gray value and dorsal dural sac gray value).
- In-observer and inter-observer reliability were assessed using reliability coefficients and statistical comparisons.
Main Results:
- GVR-B demonstrated superior repeatability and a smaller relative standard deviation compared to GVR-A.
- The mean difference in GVR-B values between clinicians was closer to zero, indicating higher agreement.
- GVR-B exhibited better inter- and intra-observer reliability than GVR-A.
Conclusions:
- The images-based GVR-B protocol offers significantly better inter- and intra-observer reliability for assessing spinal cord hyperechogenicity during DCM decompression.
- GVR-B is a more dependable method for real-time spinal cord visualization and prognostic prediction in DCM patients undergoing French-door laminoplasty.
- This improved ultrasound technique provides a more reliable basis for future research and clinical application in managing DCM.
Objectives:
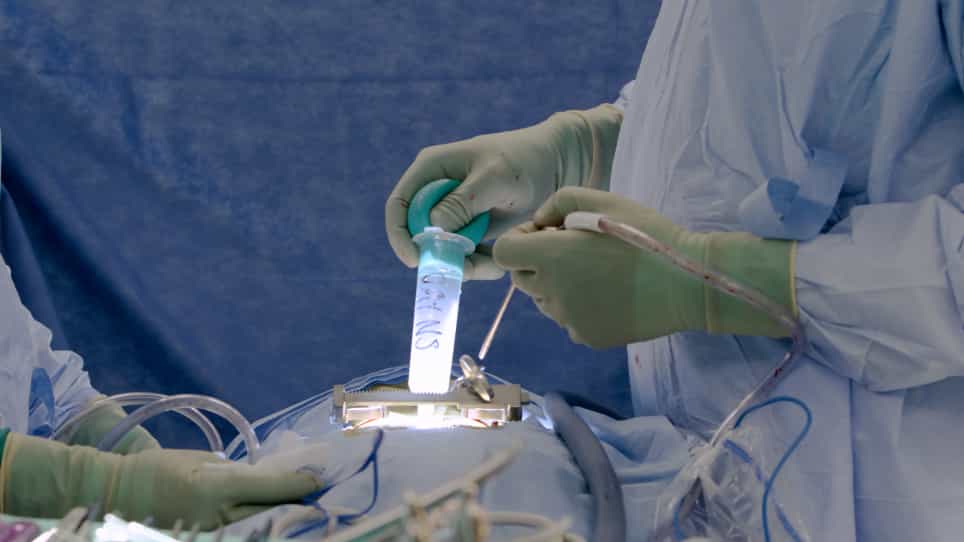
During French-door laminoplasty, a linear array transducer of IOUS was used to observe and record the spinal cord decompression. To acquire a higher-reliability method, and compare the in-observer and inter-observer reliability of two methods in evaluating the hyperechoic intensity of spinal cord ultrasound in degenerative cervical myelopathy (DCM).
Background:
The intensity of spinal cord hyperechogenicity is considered as a potential predictor of neurological recovery in DCM after decompression, but the accuracy of gray value ratio (GVR) is affected by many factors.
Methods:
Totally 28 patients (20 males and 8 females) who had been followed up for 12 months were included. Their mean age at surgery was 61.2 ± 10.8 years and the average symptom duration was 23.36 ± 22.11 months. The gray values of circles 1, 2 and 3 were recorded as Gcompression, Gnorml and Gsac, respectively. Circle 1 was drawn with the maximum brightness point within the spinal cord as the center, circle 2 with the same area was plotted on the spinal cord with uniform echogenicity, without compression and at least 1 cm away from the circle 1, and circle 3 was drawn on the dorsal dural sac at the same segment as circle 1. GVR was calculated as follows: GVR-A = Gcompression/Gnorml (method A), and GVR-B = Gcompression/Gsac (method B). The in-observer and inter-observer reliabilities of the two methods were compared. It is generally believed a reliability coefficient < 0.40 and > 0.75 indicate poor and good reliability respectively. The images-based GVR-B using this protocol demonstrates higher inter- and intraobserver reliabilities than GVR-A, and can be used as the basis for prognostic prediction and future studies.
Results:
All examination acquisitions were successfully completed. GVR-A averaged 2.043 (0.318-5.56), and GVR-B averaged 0.578(0.06-1.41). GVR-B has better repeatability of gray value measurement, smaller relative standard deviation (RSD%) (0.298 vs. 0.32) and larger inter-group correlation coefficient compared with GVR-A. The mean value (MD) of the GVR difference calculated by GVR-B between the two clinicians was closer to 0.
Conclusions:
For DCM patients routinely using ultrasound for real-time cord visualization during spinal cord decompression by French-door laminoplasty, the images-based GVR-B using this protocol demonstrates better inter- and intraobserver reliabilities compared with GVR-A.