Related Experiment Video
Updated: Aug 8, 2026


Methods for Quantitative Detection of Antibody-induced Complement Activation on Red Blood Cells
Published on: January 29, 2014
Glomerulonephritis associated with complete deficiency of the fourth component of complement. Response to intravenous
T R Welch1, A J McAdams, L S Beischel
1Children's Hospital Research Foundation, Cincinnati, Ohio, USA.

Insights
A teen with C4 deficiency and lupus developed nephritis. Intravenous immunoglobulin therapy improved symptoms and reduced kidney inflammation, suggesting alternative treatments for complement-deficient patients.
Area of Science:
- Immunology
- Nephrology
- Genetics
Background:
- Complete C4 deficiency is a rare genetic condition.
- Individuals with C4 deficiency have an increased risk of autoimmune disorders, including lupus.
- Lupus nephritis is a serious complication characterized by immune complex deposition in the kidneys.
Observation:
- A 15-year-old female with C4 deficiency and a lupus-like disorder presented with nephritis.
- Renal biopsy confirmed immune complex glomerulonephritis with significant deposits.
- The patient had normal renal function at presentation.
Findings:
- Treatment with monthly intravenous immunoglobulin (IVIG) for six months was well-tolerated.
- IVIG therapy led to the resolution of cutaneous lupus manifestations (rash) and hematuria.
- Follow-up renal biopsy revealed reduced glomerular proliferation and fewer immune deposits.
Implications:
- This case highlights the potential efficacy of IVIG in managing lupus nephritis in complement-deficient patients.
- The findings suggest that non-immunosuppressive therapies may be viable alternatives for glomerulonephritis in this population.
- Given the heightened infection risk in complement deficiency, avoiding traditional immunosuppression is crucial.
Abstract:
A 15-year-old girl with complete C4 deficiency and a lupus-like disorder developed evidence of nephritis after 4 years of followup. Renal biopsy demonstrated an immune complex glomerulonephritis, with deposits in the capillary loops, the paramesangium, and the mesangial matrix. Renal function was normal. The patient was treated with monthly infusions of intravenous immunoglobulin for 6 months. The treatment was well tolerated, and resulted in resolution of the rash and hematuria. Followup biopsy showed less proliferation and fewer loop deposits. In light of the serious risk of infections that is associated with complement deficiency, approaches to glomerulonephritis that do not include immunosuppression should be considered.
More Related Videos
 09:12
A Protein Microarray Assay for Serological Determination of Antigen-specific Antibody Responses Following Clostridium difficile Infection
Published on: June 15, 2018
 09:43
Analyses of Proteinuria, Renal Infiltration of Leukocytes, and Renal Deposition of Proteins in Lupus-prone MRL/lpr Mice
Published on: June 8, 2022
Related Concept Videos
 01:36
Humoral Immune Responses
 01:25
Immunodeficiency Diseases
There are three main causes of immunodeficiency disorders...
 01:27
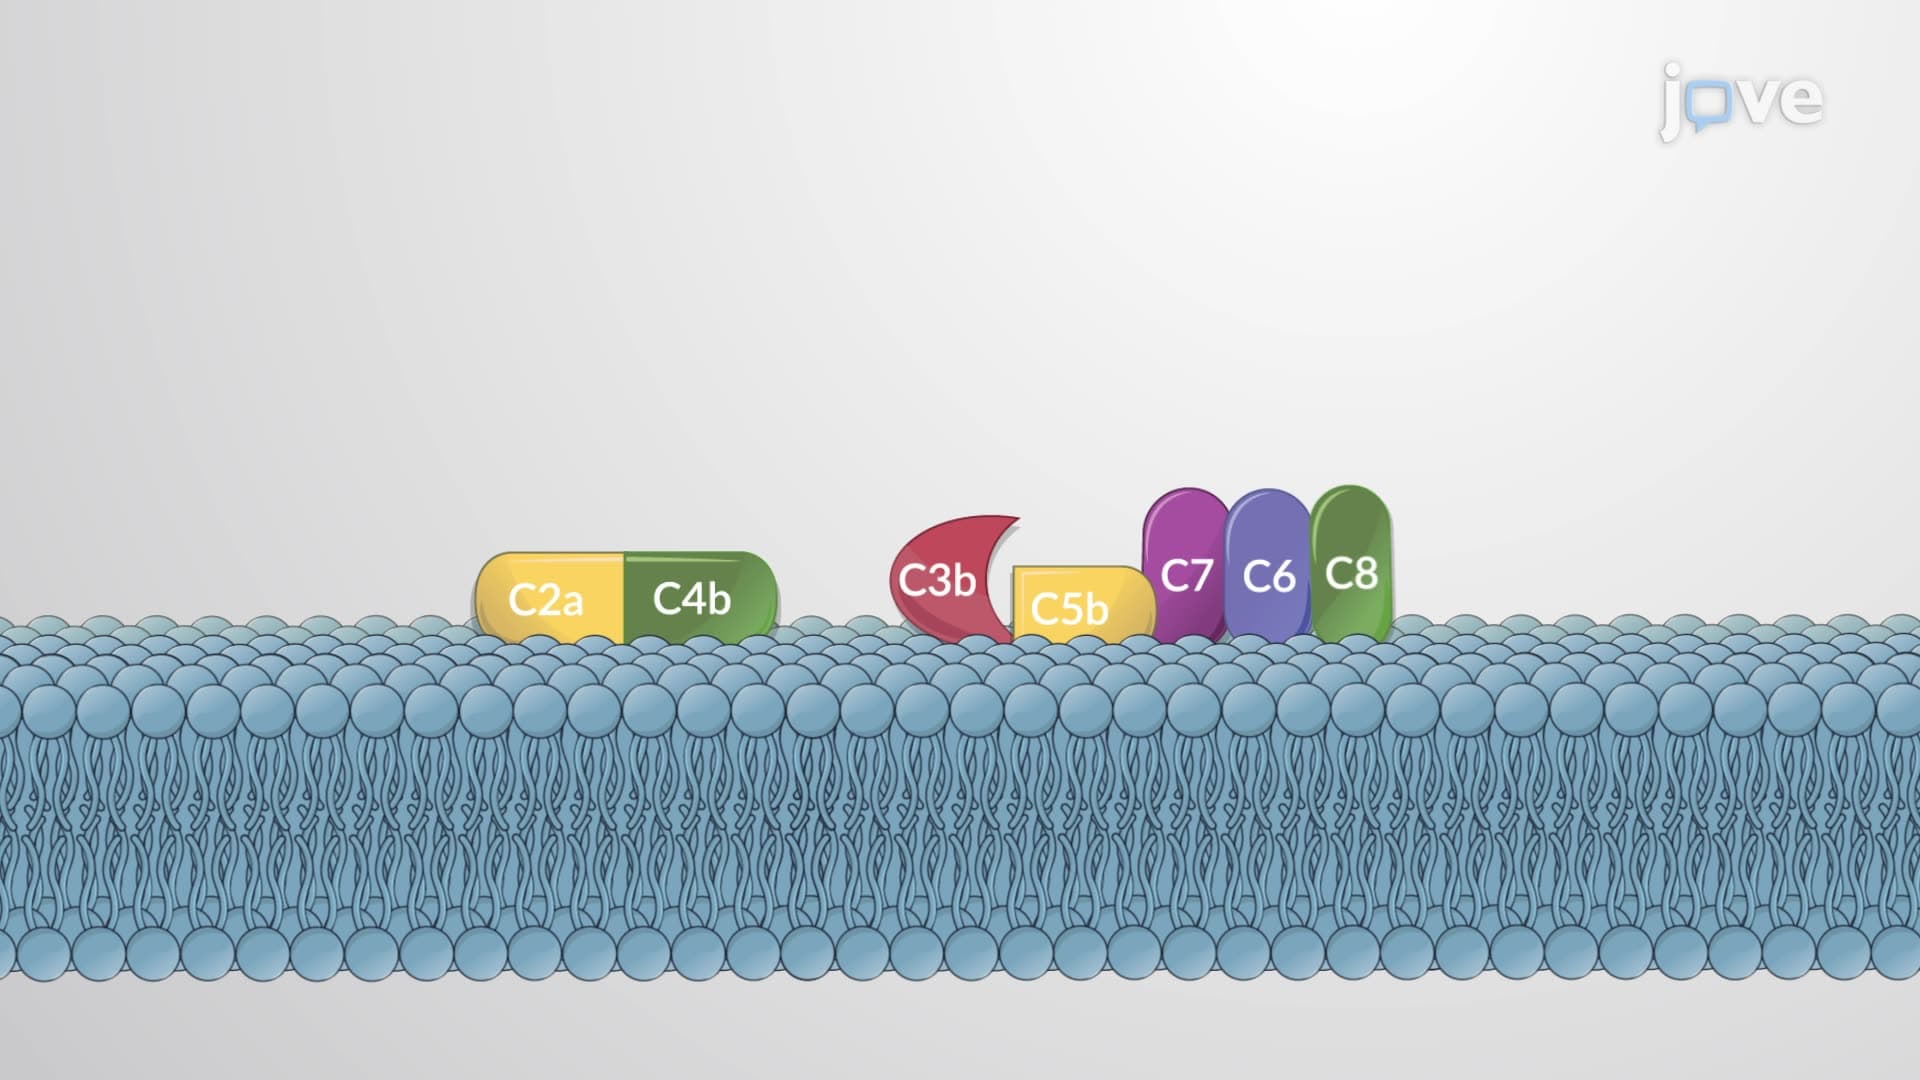
Complement System
 01:27
Acute Pyelonephritis I: Introduction
 01:28
Acute Pyelonephritis II: Diagnostic Studies and Management
 01:19
Hypersensitivity Reactions: Immune-Complex Reactions