Related Experiment Video
Updated: Aug 5, 2026
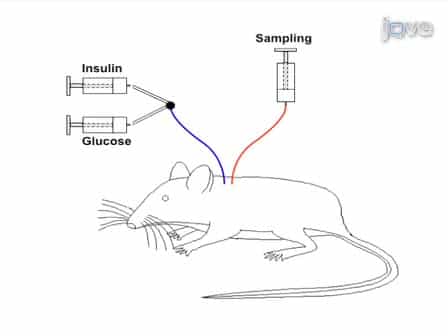

Hyperinsulinemic-Euglycemic Clamp in the Conscious Rat
Published on: February 7, 2011
Interstitial insulin during euglycemic-hyperinsulinemic clamp in obese and lean individuals
S P Mokshagundam1, A N Peiris, J I Stagner
1Department of Medicine, University of Louisville, KY, USA.

Insights
Transcapillary insulin transport is rapid and unaffected by obesity. Direct measurement shows insulin quickly reaches tissues, challenging the idea it limits insulin action in healthy men.
Area of Science:
- Endocrinology
- Metabolism
- Physiology
Background:
- Transcapillary insulin transport is a critical, yet poorly understood, determinant of insulin action.
- Previous studies lacked direct measurement of interstitial insulin levels during physiological hyperinsulinemia.
Purpose of the Study:
- To directly measure interstitial insulin levels in subcutaneous adipose tissue during a euglycemic-hyperinsulinemic clamp.
- To investigate the impact of obesity and fat distribution on transcapillary insulin transport.
Main Methods:
- Microdialysis was used to measure interstitial insulin concentrations in the abdominal and thigh subcutaneous adipose tissue of lean and obese men.
- A euglycemic-hyperinsulinemic clamp was performed to achieve controlled insulinemia.
Main Results:
- Interstitial insulin levels rapidly changed, reaching steady-state within 10 minutes of insulin infusion and returning to basal levels within 10 minutes of discontinuation.
- The rapidity and relative change in interstitial insulin were not significantly different between obese and lean individuals.
- Obesity, waist-to-hip ratio, and fat distribution pattern did not affect transcapillary insulin transport in adipose tissue.
Conclusions:
- Transcapillary insulin transport in human adipose tissue is rapid and does not exhibit a significant lag phase.
- Obesity and fat distribution patterns do not impair transcapillary insulin transport in healthy men.
- Direct measurement reveals that transcapillary insulin transport is not a rate-limiting step in insulin action in this context.
Abstract:
Transcapillary insulin transport has been considered a rate-limiting step of insulin action. However, direct measurement of interstitial insulin levels during physiologic levels of insulinemia have not been performed. We determined changes in interstitial insulin in eight healthy non-obese men and seven healthy obese men by microdialysis during a euglycemic-hyperinsulinemic clamp. Interstitial insulin was determined in the subcutaneous tissue of the abdomen and thigh. Steady-state insulin concentrations were reached approximately 10 minutes after the start of insulin infusion in the subcutaneous tissue of the abdomen and thigh and returned to basal levels approximately 10 minutes after the infusion was discontinued. There was no difference in the rapidity of change in interstitial insulin between obese and lean individuals at either site studied, irrespective of the pattern of fat distribution. The relative change in dialysate insulin concentration during the euglycemic clamp did not differ between obese and lean individuals at either site studied. It was also unaffected by the waist to hip ratio. The rapid change in interstitial insulin concentration could be of physiologic significance in determining the effects of changes in circulating insulin concentration. We conclude that transcapillary insulin transport in adipose tissue is unaffected by obesity and the pattern of fat distribution in healthy men. It is also concluded that when interstitial insulin is determined directly, transcapillary insulin transport is rapid and does not demonstrate a significant lag phase.

Related Concept Videos
 01:27
Glucose Homeostasis: Pancreatic Islets and Insulin Secretion
Insulin and C-peptide are co-secreted in...
 01:28
Insulin: The Receptor and Signaling Pathways
 01:16
Insulin: Dosing Regimen and Adverse Effects
The basal dose constitutes about 40%-50% of the total daily dose, with the rest as premeal insulin. The mealtime insulin dose should mirror...