Anaphylactic shock in a patient with ruptured hydatid liver cyst owing to trivial abdominal trauma
Related Experiment Video
Updated: Aug 12, 2026

Uncontrolled Hemorrhagic Shock Modeled via Liver Laceration in Mice with Real Time Hemodynamic Monitoring
Published on: May 21, 2017
A I Yahya1, J Przybylski, A Foud
1Surgical Department, Zliten Central Hospital, Libya.

Insights
A teenage male experienced severe abdominal pain after a football injury, presenting with shock and abdominal rigidity. Emergency surgery revealed internal injuries requiring immediate intervention.
Area of Science:
- Trauma Surgery
- Emergency Medicine
- Abdominal Trauma
Background:
- Blunt abdominal trauma can lead to severe internal injuries.
- Prompt diagnosis and surgical intervention are critical for patient survival.
Observation:
- A 16-year-old male presented with upper abdominal pain, shock (unrecordable blood pressure), pallor, and dyspnea after blunt abdominal trauma.
- Physical examination revealed generalized abdominal tenderness, guarding, and rigidity.
- Initial resuscitation included intravenous fluids, analgesia, and oxygen, followed by diagnostic peritoneal lavage.
Findings:
- Diagnostic peritoneal lavage revealed serosanguinous fluid, indicating intra-abdominal injury.
- The patient's condition necessitated an urgent exploratory laparotomy.
Implications:
- This case highlights the importance of considering intra-abdominal injury in blunt abdominal trauma, even without external signs.
- Timely surgical exploration is crucial for managing potentially life-threatening abdominal trauma.
- Adherence to advanced trauma life support protocols is vital for stabilizing patients with severe abdominal injuries.
Abstract:
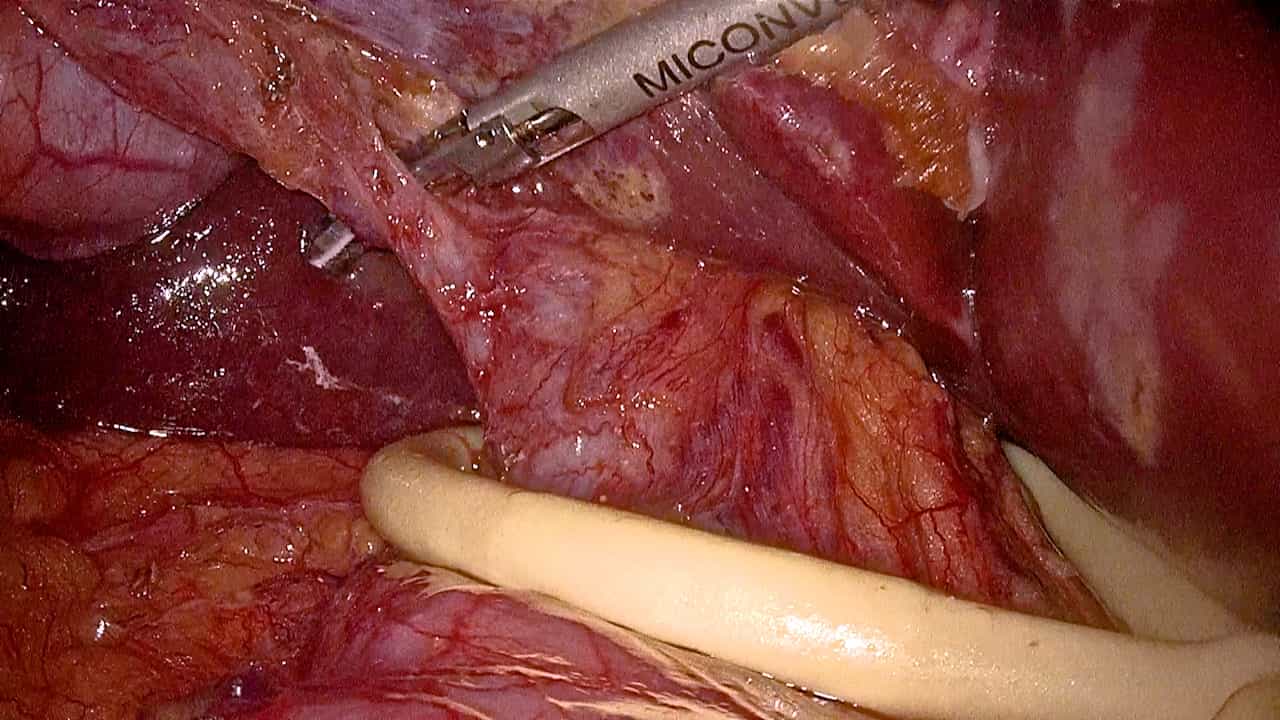
A 16-year-old Libyan male was admitted to the Intensive Therapy Unit (ITU) of Zliten Central Hospital after he had been hit on the abdomen by a football, his main symptom was upper abdominal pain. The patient looked pale, was dyspnoeic and had an unrecordable blood pressure level. Abdominal examination revealed tenderness, guarding and rigidity all over the abdomen. Other results were normal and there were no external signs of injury. The patient received intravenous fluid, analgesia and oxygen by mask. Peritoneal lavage was performed and a small amount of sero-sanguineous fluid was expelled. After resuscitation measures his blood pressure rose and the patient was taken to the operation theatre for a laparotomy.

Related Concept Videos
 01:22
Esophageal Perforation-I: Introduction
The location of esophageal perforation can vary, occurring anywhere along the esophagus.
 01:30
Aneurysm I: Introduction
 01:28
Amebiasis
 01:25
Hiatal Hernia
 01:20
Cholecystitis
 01:21
Acute Pancreatitis II: Pathophysiology