Video Experimental Relacionado
Updated: Sep 10, 2025
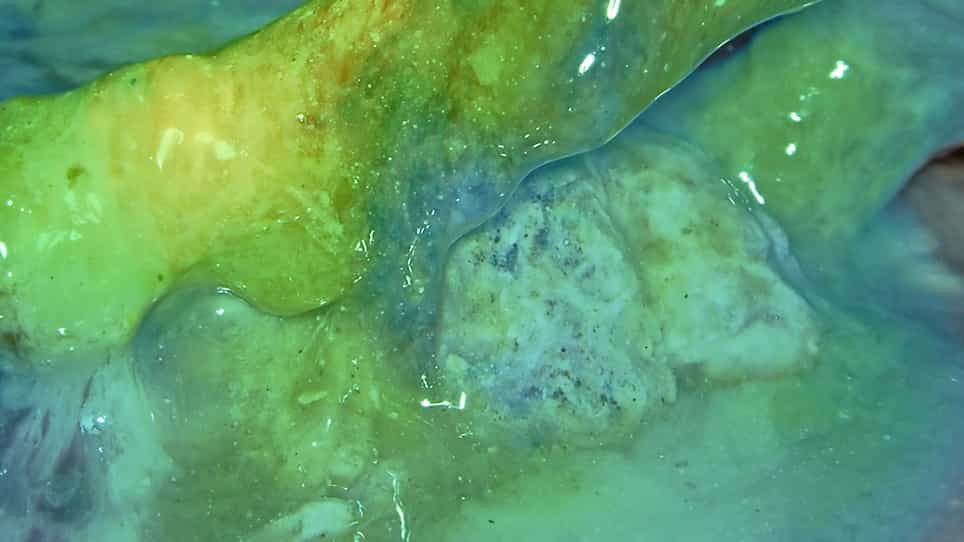

Indocyanine Green-Guided Intraoperative Imaging to Facilitate Video-Assisted Retroperitoneal Debridement for Treating Acute Necrotizing Pancreatitis
Published on: September 8, 2022
Implementación de una vía de diagnóstico del dolor abdominal agudo en el departamento de emergencias
Samari Blomerus1, Tracy-Lee Splinter2, Amy Gillis3
1University Hospital Limerick, Dooradoyle, Ireland.

La implementación de una nueva vía de diagnóstico para el dolor abdominal agudo redujo significativamente la duración de la estancia en el departamento de emergencias (ED). Esta iniciativa de mejora de la calidad simplificó la atención de los pacientes que requieren tomografías computarizadas abdominopelvicas con contraste mejorado.
Área de la Ciencia:
- Medicina de emergencia
- Radiología
- Patología quirúrgica
Sus antecedentes:
- El dolor abdominal agudo es una presentación frecuente en el departamento de emergencias (ED).
- La tomografía computarizada abdominopelvical (TAP) con aumento de contraste es la modalidad de imagen estándar.
- Se identificó que los procesos de ED existentes para el acceso a AP CT eran complejos y consumían mucho tiempo.
Objetivo del estudio:
- Desarrollar y aplicar una vía de diagnóstico para pacientes con disfunción eréctil con dolor abdominal agudo.
- Para mejorar la duración de la disfunción eréctil y los tiempos de tratamiento en pacientes con patología abdominal aguda.
- Mejorar la eficiencia de las imágenes avanzadas en casos de dolor abdominal agudo no diferenciado.
Principales métodos:
- Un proyecto de intervención de calidad con un enfoque gradual y multidisciplinario.
- Colaboración entre radiología, cirugía general y equipos de medicina de emergencia.
- Revisión del protocolo de imágenes de TC AP para utilizar predominantemente el contraste intravenoso.
- Recopilación y análisis de datos previos y posteriores a la aplicación.
Principales resultados:
- Mejora estadísticamente significativa en la duración de la ED (p<0,01).
- Tendencia no significativa hacia una reducción del tiempo desde la llegada de la ED hasta la TC AP (p=0,06).
- Alto rendimiento diagnóstico del 79,6% para patología aguda significativa en TC AP.
Conclusiones:
- La vía de diagnóstico del dolor abdominal agudo mejoró efectivamente los tiempos de rendimiento de ED.
- La vía demostró una reducción en las tasas de admisión para las cohortes de pacientes relevantes.
- Las tomografías computarizadas AP confirmaron la idoneidad de la vía para el dolor abdominal agudo no diferenciado que requiere imágenes urgentes.
Más Videos Relacionados


Videos de Conceptos Relacionados
 01:30
Acute Pancreatitis II: Clinical Manifestations and Management
 01:26
Endoscopic Procedures V: ERCP
Patient...
 01:28
Acute Pyelonephritis II: Diagnostic Studies and Management
 01:29
Appendicitis-II: Diagnostic Studies and Management
Diagnosing Appendicitis
It requires a multifaceted approach, starting with a detailed physical examination to pinpoint the location and nature of the pain and identify any associated symptoms. Laboratory tests play a crucial role. A complete Blood Count (CBC) typically reveals leukocytosis (an increased number of...
 01:28
Peptic Ulcer Disease III: Clinical Manifestations and Diagnostic Studies
Few clinical manifestations differentiate gastric ulcers from duodenal ulcers. Distinctions in the location, timing, and pain relief are crucial for healthcare providers in differentiating between gastric and duodenal ulcers during clinical assessments.
 01:22
Appendicitis-I: Introduction
Etiology: Appendicitis can arise from various causes, primarily rooted in the obstruction of the appendix lumen. Factors contributing to this obstruction include fecal accumulation, lymphoid hyperplasia and, in...