Video Experimental Relacionado
Updated: May 3, 2026

06:15

Protocol and Guidelines for Point-of-Care Lung Ultrasound in Diagnosing Neonatal Pulmonary Diseases Based on International Expert Consensus
Published on: March 6, 2019
50.4K
Editorial: Avances en la ecografía pulmonar: de las enfermedades infantiles a las de la edad adulta, volumen II
Luigi Vetrugno1, Anna Camporesi2
1Department of Emergency, Anesthesia and Intensive Care, Health Integrated Agency of Friuli Centrale, Tolmezzo, Italy.
Frontiers in medicine
|August 22, 2025

Resumen
No abstract available in PubMed .

Videos de Conceptos Relacionados
 01:30
Pulmonary Hypertension: Classification and Pathogenesis
906
Pulmonary hypertension (PH) is a severe health condition in which the mean pulmonary arterial pressure increases to 25 mmHg or more, even when the body is at rest. This high pressure in the blood vessels that transport blood from the heart to the lungs can cause various symptoms, including shortness of breath, can lead to right heart failure, and significantly affect the overall quality of life.
There are various classifications for PH, each relating to different underlying causes and also...
There are various classifications for PH, each relating to different underlying causes and also...
906
 01:30
Radiological Investigation II: MRI and Ventilation Perfusion Scan
1.0K
Description
Magnetic Resonance Imaging (MRI) and Ventilation Perfusion Scans are two radiological investigations that offer detailed diagnostic images of the body, particularly lung structures.
MRI
MRI uses magnetic fields and radiofrequency signals to distinguish between normal and abnormal tissues. This technology provides a more detailed diagnostic image than CT scans, enabling it to characterize pulmonary nodules, stage bronchogenic carcinoma, and evaluate inflammatory activity in...
1.0K
 01:29
Pulmonary Embolism II: Diagnostic Studies and Interprofessional Care
749
Diagnosing Pulmonary EmbolismDiagnosing pulmonary embolism (PE) involves clinical assessment and advanced imaging tests. The preferred diagnostic tool is the spiral (helical) CT scan or CT angiography (CTA), which uses intravenous contrast media to visualize the pulmonary vasculature and identify emboli.A ventilation-perfusion (V/Q) scan is an alternative for patients unable to receive contrast media. This scan includes both perfusion and ventilation scanning. Perfusion scanning involves...
749
 01:10
Atelectasis II: Pathophysiology
40
Atelectasis develops when alveoli lose their air and collapse inward. Because lung tissue is naturally elastic, these air sacs shrink rather than remaining open. Collapsed alveoli are no longer ventilated, reducing their role in gas exchange. Blood flow may continue in these regions, creating a ventilation–perfusion mismatch. Clinical findings include decreased breath sounds, dullness to percussion, reduced chest expansion, and decreased tactile fremitus as sound transmission through...
40
 01:23
Chronic Obstructive Pulmonary Disease II: Emphysema
48
Emphysema, a major phenotype of chronic obstructive pulmonary disease (COPD), is characterized by irreversible destruction of alveolar walls and permanent enlargement of distal airspaces. Unlike chronic bronchitis, which primarily affects the airways, emphysema predominantly involves the lung parenchyma, where structural damage leads to airflow limitation.PathophysiologyIt most commonly results from prolonged exposure to cigarette smoke and other toxic gases, particularly cigarette smoke.
48
 01:18
Pulmonary Edema II: Pathophysiology
39
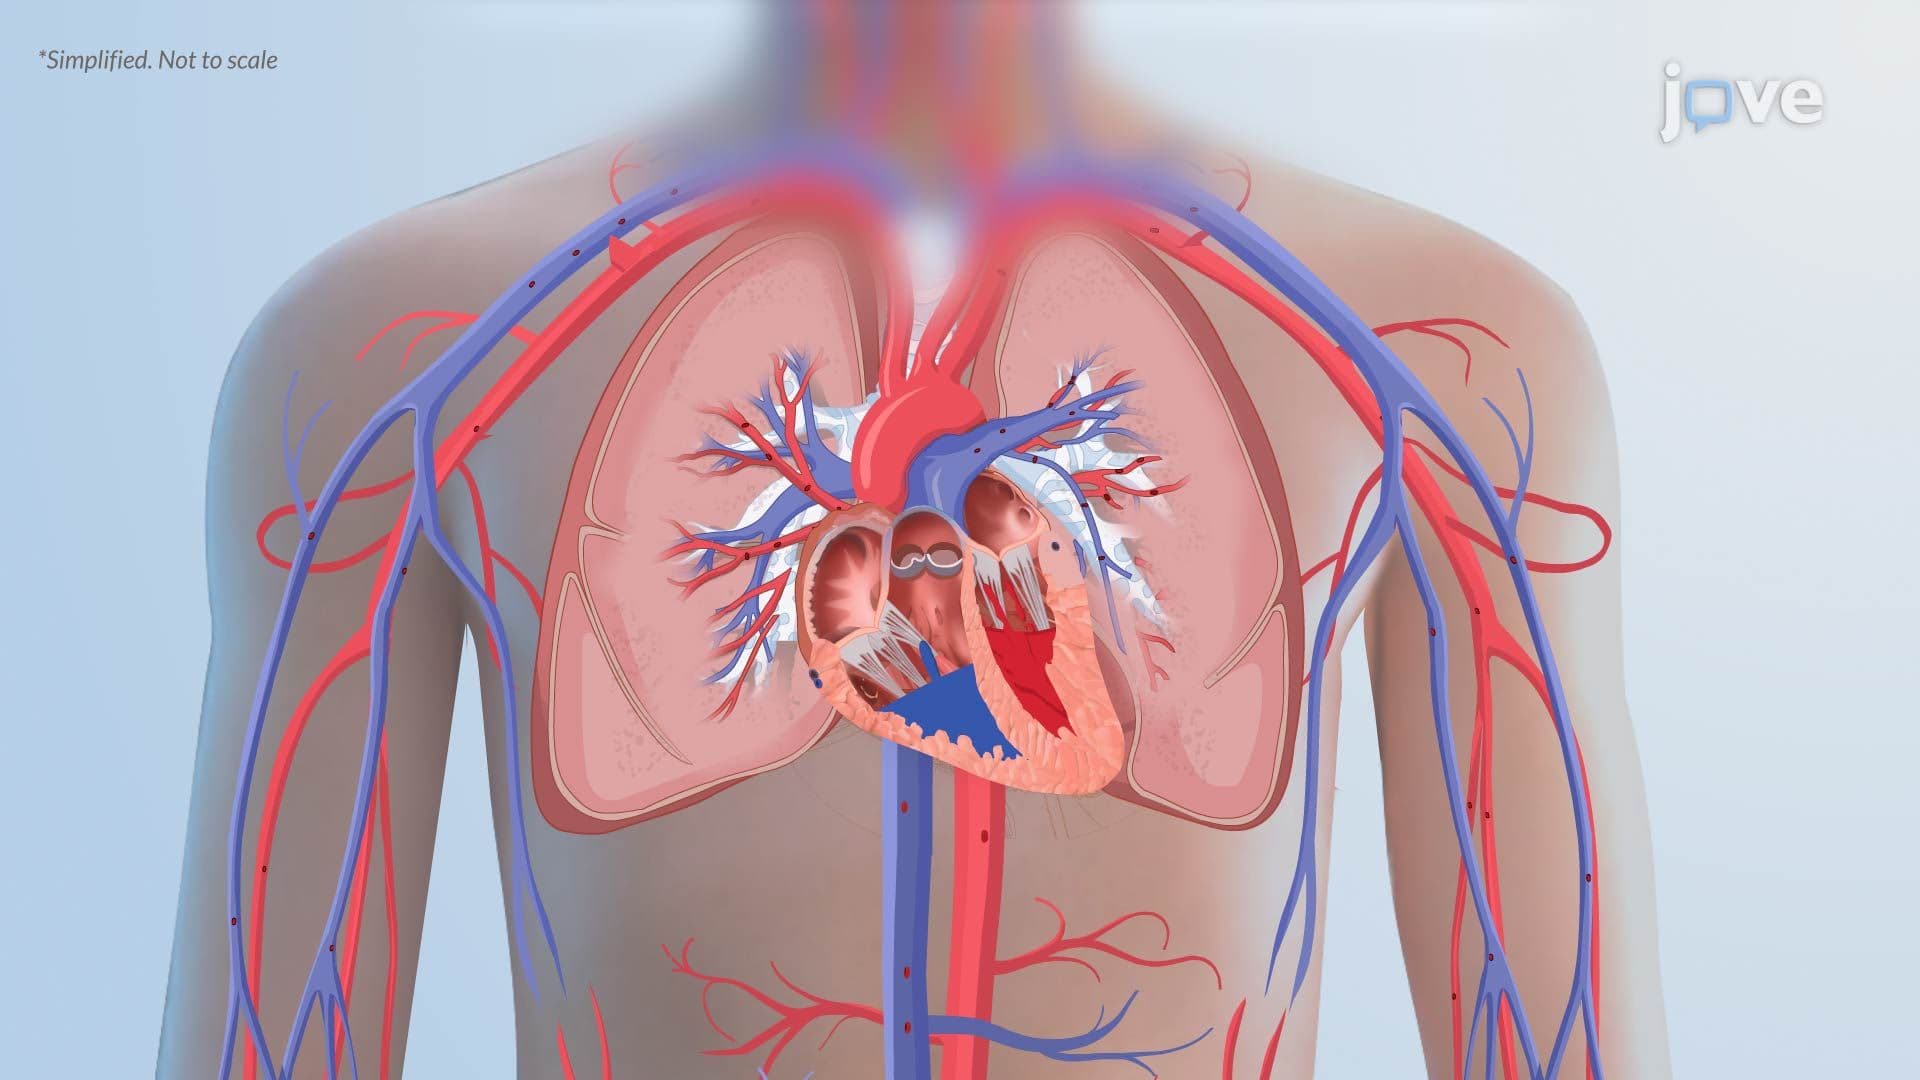
Pulmonary edema is the accumulation of fluid in the interstitial and alveolar spaces of the lungs, impairing gas exchange and oxygen delivery. It may be cardiogenic or noncardiogenic, but both reduce oxygenation and lung compliance.Cardiogenic Pulmonary EdemaCardiogenic edema results from increased hydrostatic pressure in pulmonary capillaries, usually due to left ventricular dysfunction from myocardial infarction, heart failure, or valvular disease. Ineffective cardiac pumping causes blood to...
39