Necesidad de mantener la flexibilidad: Argumentos a favor de las habilidades de intubación con fibra óptica
Video Experimental Relacionado
Updated: Jan 7, 2026
Guidelines for Elective Pediatric Fiberoptic Intubation
Published on: January 17, 2011
Fahd Sahi1, Haroon Mather1, Peter Murchan2
1Anesthesiology and Critical Care, Tipperary University Hospital, Clonmel, IRL.

Abstract:
Advances in video laryngoscopy (VL) have revolutionized airway management with higher successful first-attempt intubation rates as compared to direct laryngoscopy. However, in select patients with complex airway anatomy, particularly those with head and neck cancer, awake fiberoptic intubation (AFOI) remains the gold standard. The growing preference for VL risks marginalizing AFOI, potentially disadvantaging patients who cannot be safely intubated otherwise. We present the case of a 61-year-old male with a history of advanced throat cancer and prior extensive head and neck surgery, who presented with rectal bleeding and was diagnosed with sigmoid cancer requiring urgent colectomy. Preoperative airway assessment revealed multiple predictors of a difficult airway, including recurrent pharyngeal tumor extending into the larynx, subglottic stenosis, limited neck mobility, and distorted anatomy. In a prospective multidisciplinary team approach, AFOI was successfully performed using flexible fiberoptic bronchoscopy under anxiolysis and topical anesthesia, with emergency front-of-neck access on standby. The airway was secured uneventfully as planned. The patient was extubated at the end of surgery without complication and discharged from the ICU on postoperative day 2. This case underscores the critical importance of preserving fiberoptic intubation skills for managing difficult airways. VL is not always feasible in anatomically altered or surgically reconstructed airways. Despite its decreasing frequency in clinical use, fiberoptic intubation remains a valuable, potentially lifesaving, technique. Simulation and team-based approaches are essential for skill retention and preparedness. In an era dominated by VL, AFOI must remain a core competency for anesthesiologists managing complex airways. Continued training, simulation, and clinical application are vital to prevent the extinction of this critical skill.
Más Videos Relacionados
Videos de Conceptos Relacionados
 01:30
Cardiopulmonary Resuscitation V: Advanced Airway Management Techniques
 01:17
Endotracheal Intubation II: Nursing Management
1. Nursing Care of Patients Before Intubation
Before the endotracheal intubation procedure, nurses play an essential role in ensuring the process goes smoothly. The nurses must be familiar with intubation...
 01:15
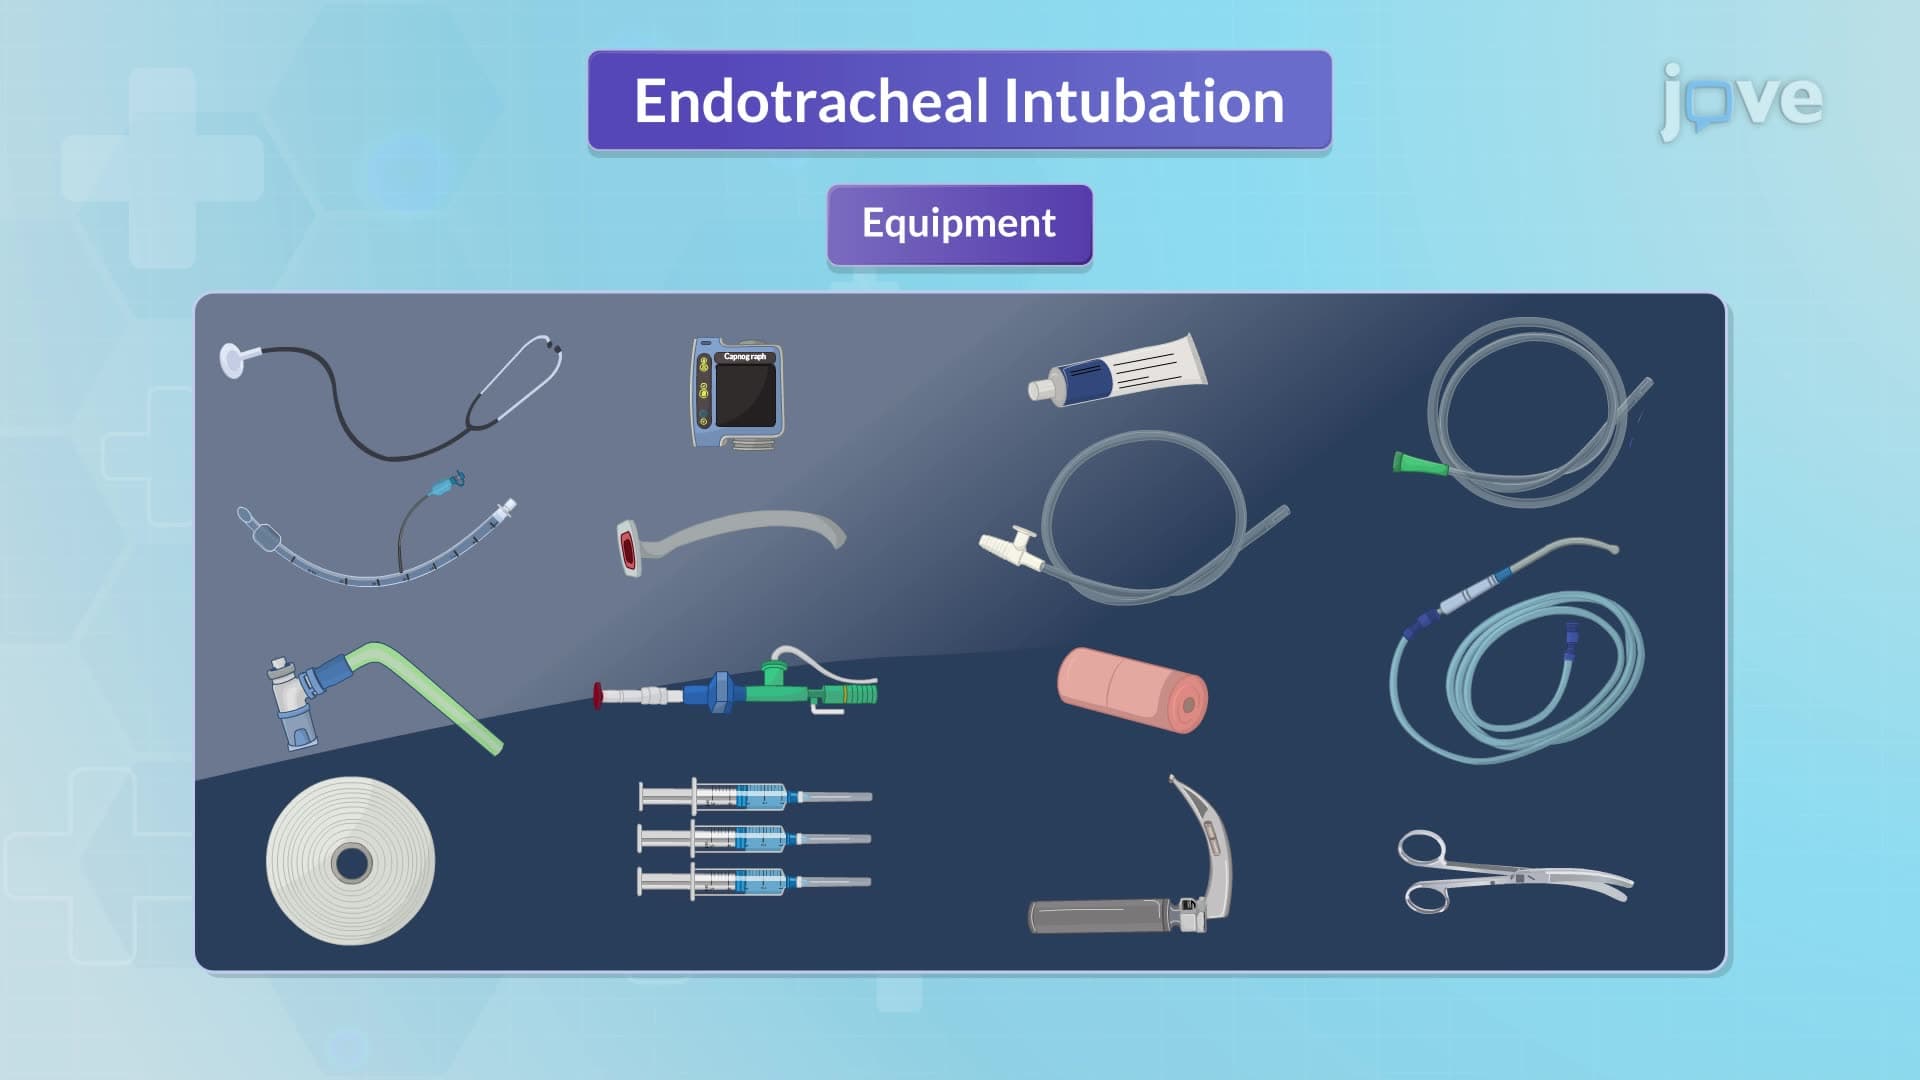
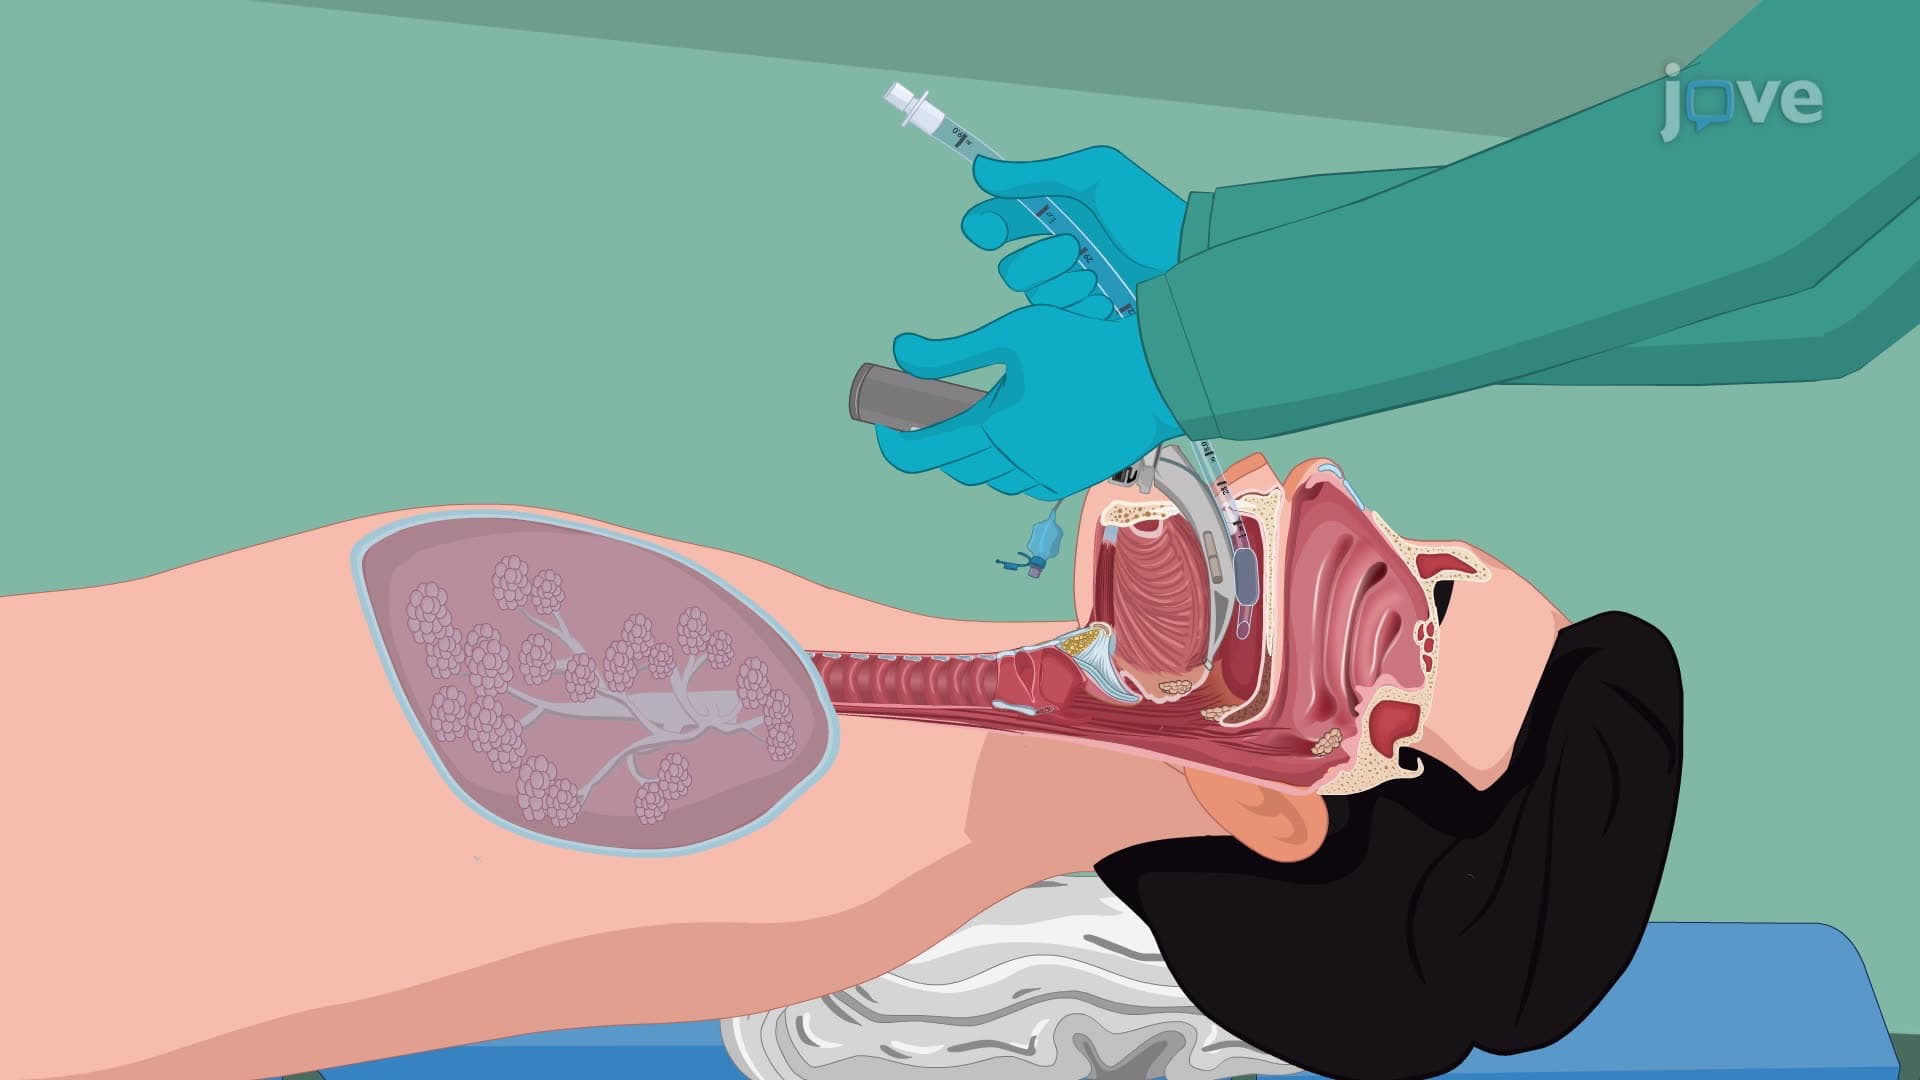
Endotracheal Intubation I: Procedure
The ET tube comprises various components, including a standard adaptor to attach a bag-valve-mask (BVM) or ventilator, a cuff, a pilot balloon, and radiopaque markings along its length to measure the insertion distance. The tube sizes...
 01:23
Oxygen Delivering System III: Tracheostomy and T-piece
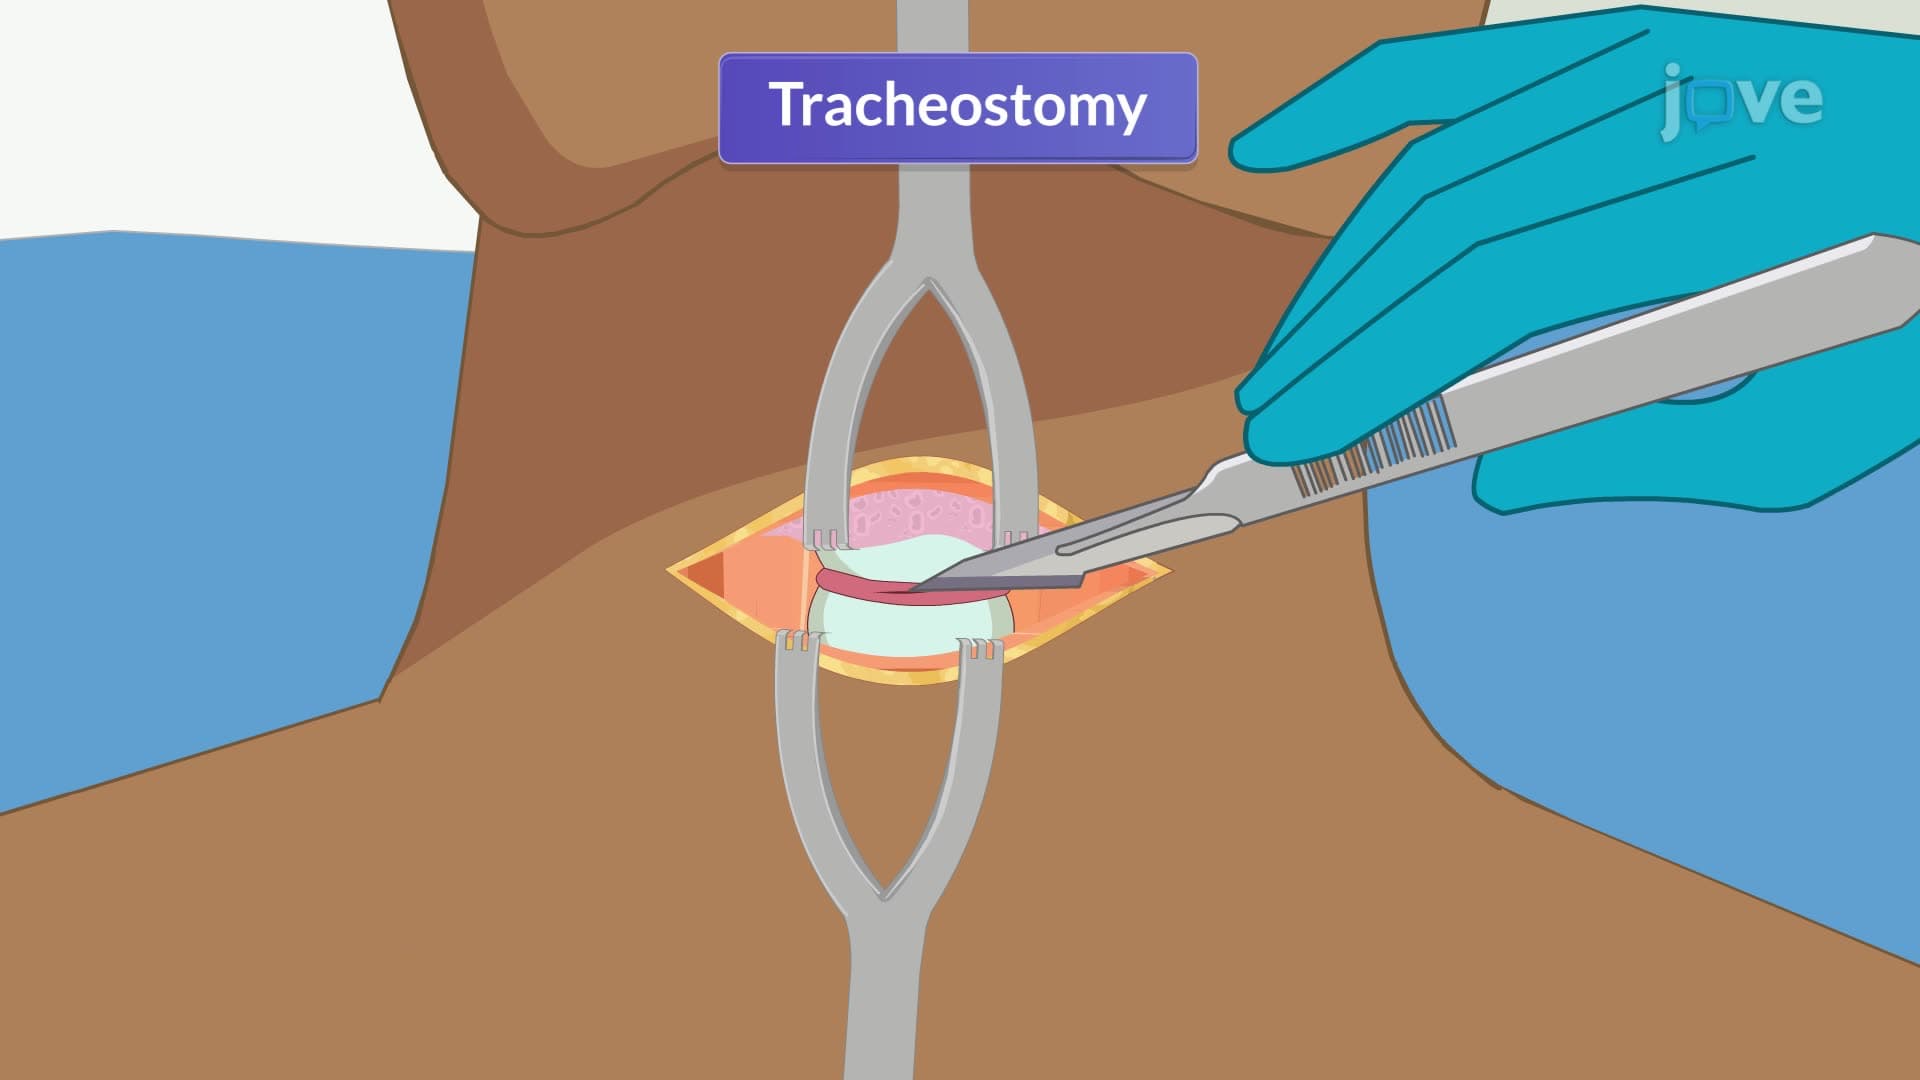
Tracheostomy
A tracheostomy is a surgically created opening (stoma) in the anterior part of the trachea. It is used to establish a patient airway, bypass an upper airway obstruction, simplify the removal of secretions, permit long-term...
 01:28
Tracheostomy: Procedure and Tubes
Tracheostomy tubes can be made of semiflexible plastic (polyurethane or silicone), rigid plastic, or metal, and they come in...
 01:24
Endotracheal Tube Extubation
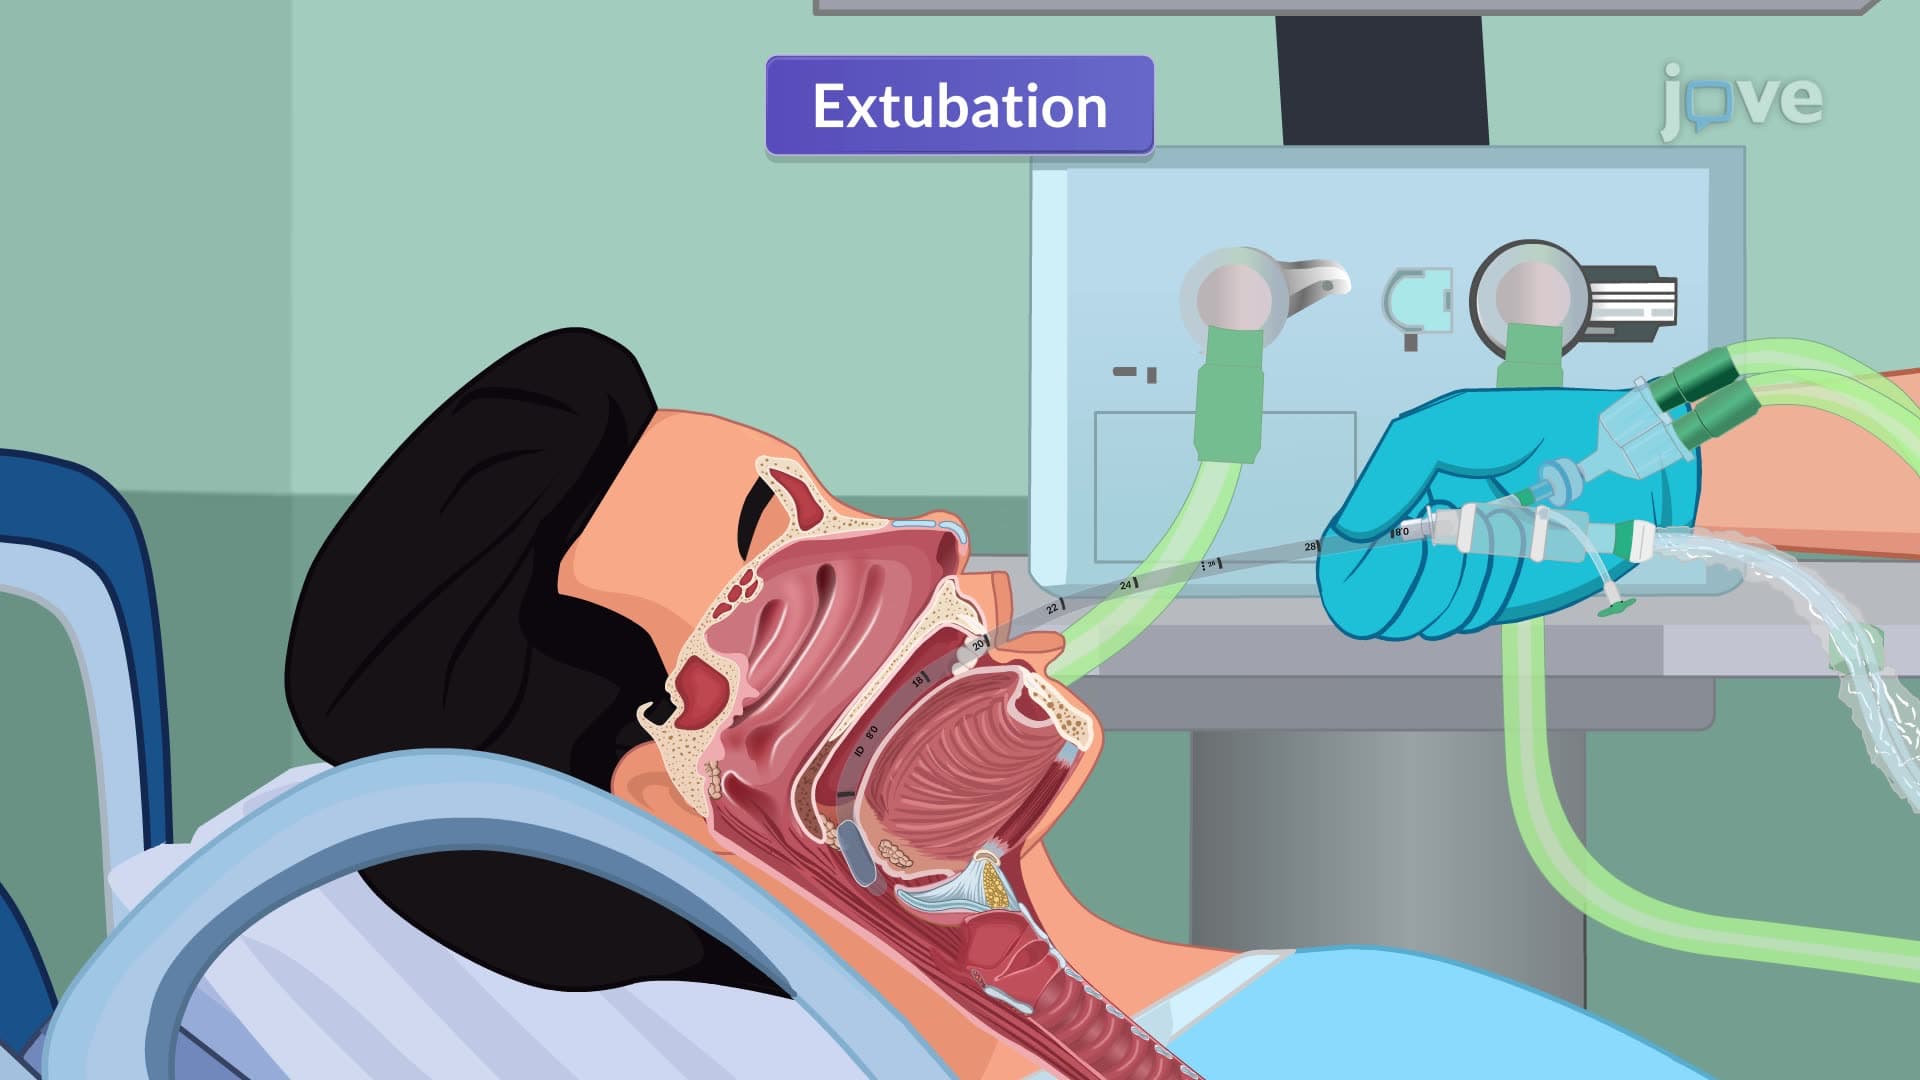
Procedure
Extubation removes the endotracheal tube (ETT) from the patient on mechanical ventilation. It requires a well-coordinated, multidisciplinary approach involving physicians, nurses, respiratory therapists, and other healthcare professionals....