Video Experimental Relacionado
Updated: May 2, 2026
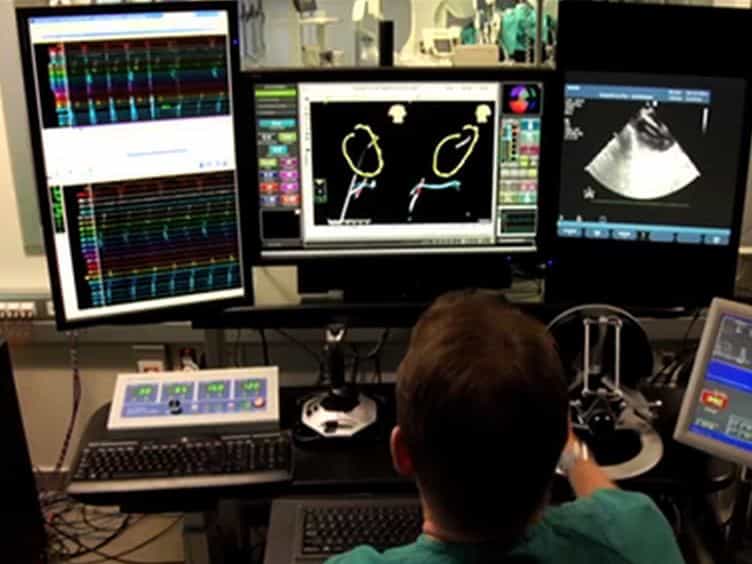
Remote Magnetic Navigation for Accurate, Real-time Catheter Positioning and Ablation in Cardiac Electrophysiology Procedures
Published on: April 21, 2013
4D Digital Heart Model-Guided Left and Right Ventricular Lead Placement for Cardiac Resynchronization Therapy:
Derek S Chew1, Bert Vandenberk2, Derek V Exner1
1Department of Cardiac Sciences, Libin Cardiovascular Institute (D.S.C., D.V.E., D.L., J.F., Y.M., S.R., G.S., J.A.W.).

Background:
Suboptimal left ventricular (LV) and right ventricular lead positioning has been associated with a lesser response to cardiac resynchronization therapy. The MAPIT-CRT (MRI Allocation of Pacing Targets in Cardiac Resynchronization Therapy) randomized controlled trial evaluated a novel, cardiac magnetic resonance-generated 4-dimensional phenomics cardiac magnetic resonance imaging (4DPcmr) lead placement strategy.
Methods:
A total of 202 participants with New York Heart Association class II to IV heart failure on optimal medical therapy, LV ejection fraction ≤35%, and QRS duration ≥120 ms were enrolled from 7 Canadian sites. Participants were randomized to 4DPcmr-guided lead placement using a web-based application or standard lead placement. 4DPcmr-recommended LV and right ventricular lead locations were generated using the combined consideration of (1) regional scar distribution and burden, (2) maximal regional delay in LV peak systolic strain, and (3) maximal interlead distance.
Results:
The primary end point, an increase in LV ejection fraction ≥5% at 6 months, was reached in 69 of 105 4DPcmr-guided patients (65.7%) versus 50 of 96 control patients (52.1%; risk ratio, 1.80 [95% CI, 1.02-3.17]; P=0.04). The absolute increases in LV ejection fraction observed for the respective intervention arms were 10.8% versus 5.8% (P=0.01). No differences in the secondary end points of all-cause mortality or heart failure hospitalization at 12 months, rate of adverse outcomes, or procedural times were identified between the 2 study arms.
Conclusions:
4DPcmr-guided LV/right ventricular cardiac resynchronization therapy lead implantation using a practical web application was clinically feasible, safe, and was associated with greater LV ejection fraction improvement at 6 months versus standard of care with no increase in procedural times or complications.
Registration:
URL: https://www.clinicaltrials.gov; Unique identifier: NCT01640769.
Más Videos Relacionados
 12:45
Benefits of Cardiac Resynchronization Therapy in an Asynchronous Heart Failure Model Induced by Left Bundle Branch Ablation and Rapid Pacing
Published on: December 11, 2017
 10:17
Real-Time Cardiac Mapping with a Noninvasive Imageless Electrocardiographic Imaging System
Published on: April 11, 2025
