Asociación entre la dosis inicial de norepinefrina y la presión arterial media minuto a minuto
Video Experimental Relacionado
Updated: Feb 28, 2026

Quantifying Acute Changes in Renal Sympathetic Nerve Activity in Response to Central Nervous System Manipulations in Anesthetized Rats
Published on: September 11, 2018
Mitsuaki Nishikimi1,2, Shinichiro Ohshimo3, Kiyono Nobayashi4
1Department of Emergency and Critical Care Medicine, Graduate School of Biomedical and Health Sciences, Hiroshima University, 1-2-3 Kasumi, Minami-ku, Hiroshima, 734-8551, Japan.

Background:
Neither the magnitude nor the timing of mean arterial pressure (MAP) increase after norepinephrine (NE) initiation is well defined, leaving clinicians without clear criteria for adequate starting doses. This study aimed to characterize minute-by-minute MAP responses to different initial NE doses in intensive care unit (ICU) patients with shock.
Methods:
We included patients admitted to seven ICUs in Japan between 2013 and 2024 who had hypotension (MAP ≤ 65 mmHg) and initiated NE infusion more than 30 min after ICU admission. Invasive MAP data were collected during the observational period, defined as 30 min before to 120 min after NE initiation. Time-dependent effects were estimated with a generalized additive model adjusting for potential confounders, to evaluate MAP changes with varying starting NE doses.
Results:
Among the 81,829 patients, 5,349 who received NE were analyzed, of whom 2,006 (37.5%) had sepsis. Both the maximum MAP rise and the 15-min rate of increase were higher at an NE infusion rate of 0.100 µg/kg/min, compared with 0.025 and 0.050 µg/kg/min (p < 0.01). Model outputs indicated that NE infusion rates of 0.025 and 0.050 µg/kg/min failed to achieve a MAP ≥ 65 mmHg within 60 min when baseline MAP was below 53.9 and 48.4 mmHg, respectively. Failure to achieve MAP ≥ 65 mmHg within 60 min was independently associated with increased ICU mortality (odds ratio: 1.49 [1.27-1.76], p < 0.01). In sepsis, the initial MAP slope at 0.025 µg/kg/min was significantly smaller than in non-sepsis (p < 0.01).
Conclusion:
Higher initial NE doses were associated with both larger and faster MAP increases. Lower starting doses appeared insufficient to achieve a target MAP within 60 min in patients with severe hypotension.
Más Videos Relacionados
 08:21
Author Spotlight: A Pharmacodissection Approach to Uncover Mechanisms in Cardiovascular Disease Risk Populations
Published on: July 21, 2023
 11:08
Novel Approach for Simultaneous Recording of Renal Sympathetic Nerve Activity and Blood Pressure with Intravenous Infusion in Conscious, Unrestrained Mice.
Published on: February 14, 2018
Videos de Conceptos Relacionados
 01:18
Neural Regulation of Blood Pressure
Baroreceptor Reflex
Baroreceptors, located in the carotid sinuses and aortic arch, detect changes in blood pressure. When blood pressure rises, these stretch-sensitive receptors...
 01:24
Blood Pressure
 01:30
Blood Pressure
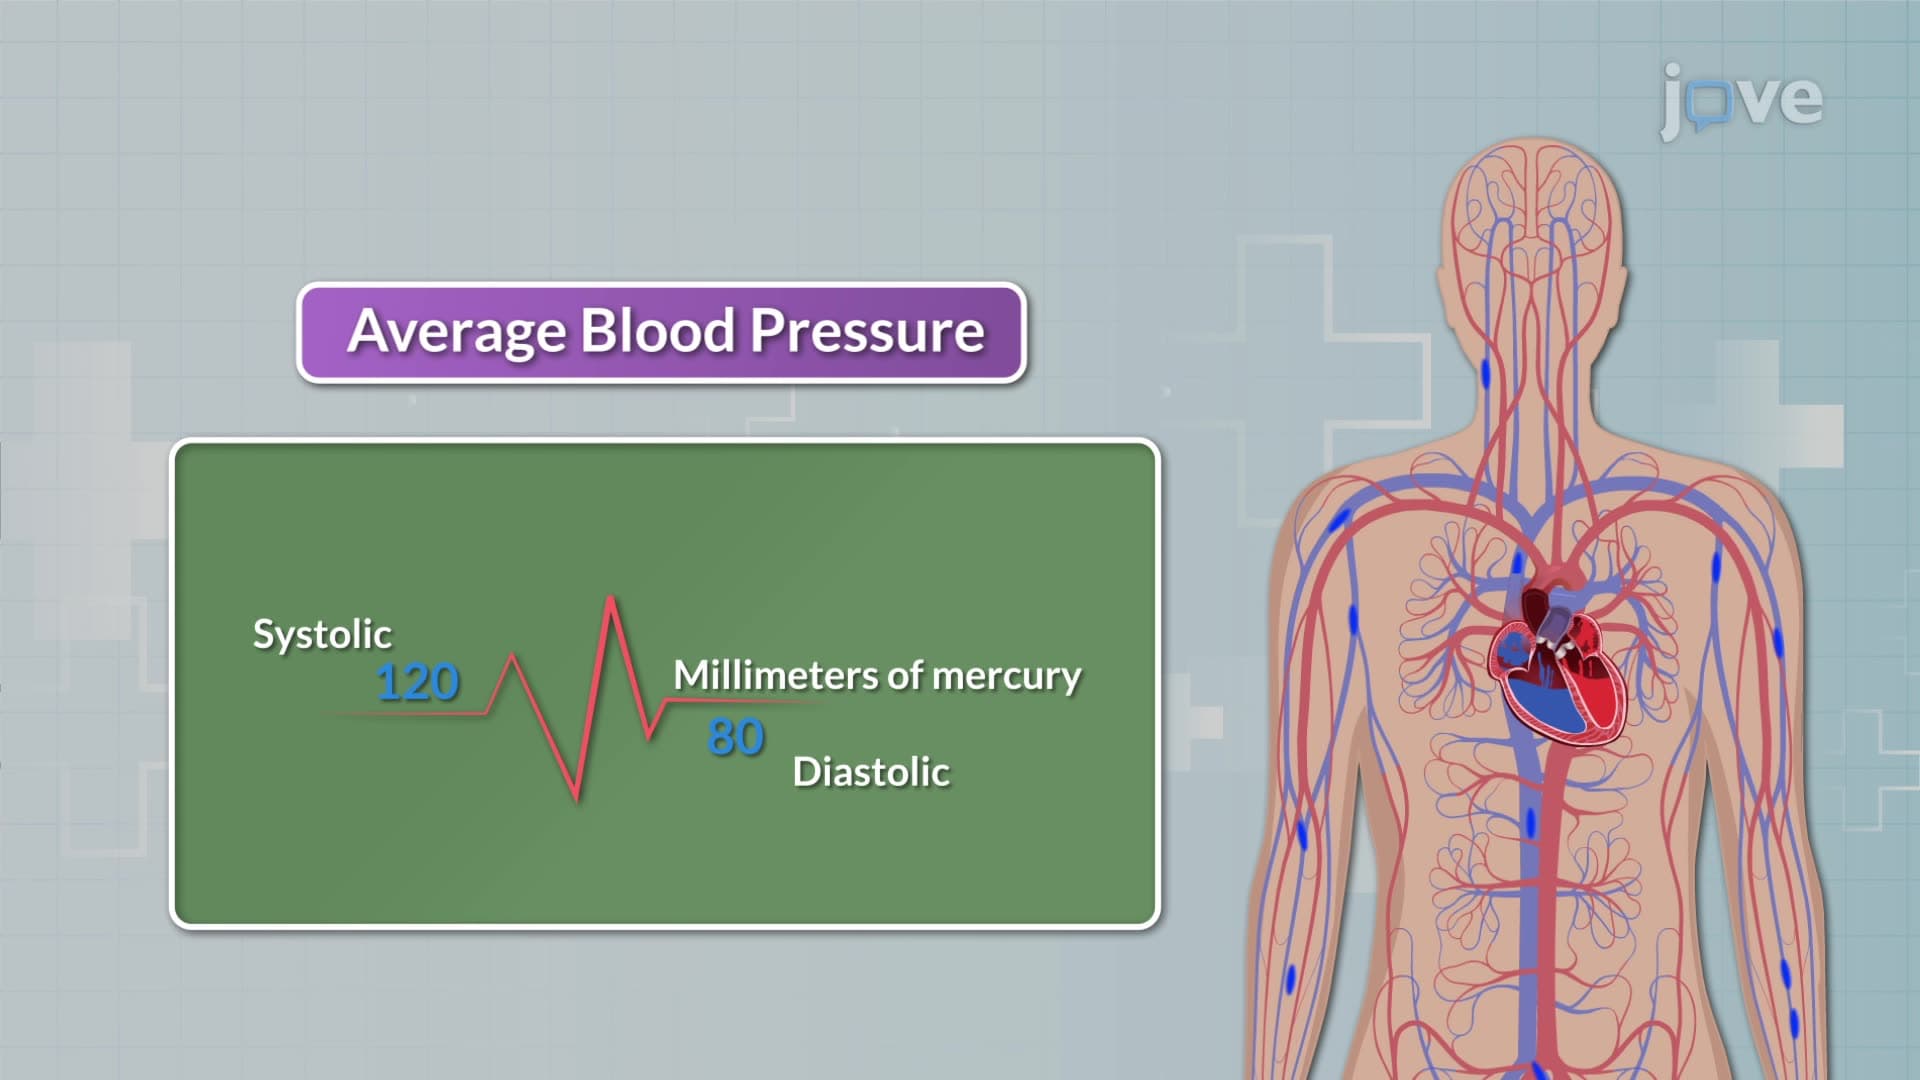
The average BP in an adult is typically around 120/80 mmHg (millimeters of mercury). In this measurement, the numerator (120) indicates the systolic pressure, which is the pressure in the arteries during the contraction of the heart's ventricles as blood is expelled. The denominator (80) represents the...
 01:15
Chronopharmacokinetics: Circadian Rhythms and Influence on Drug Response
The time of drug administration is an important factor to consider, as it can influence the toxic dose of a drug. For example, a study conducted by Prins et al. in 1997 examined the effects of the timing of...
 01:28
Special considerations while measuring blood pressure
Monitoring Both Arms:
Monitoring BP in both arms during the initial assessment is advisable, as the systolic value may differ by five to ten mm Hg between arms. For subsequent BP assessments, use the arm with the higher reading.
 01:28
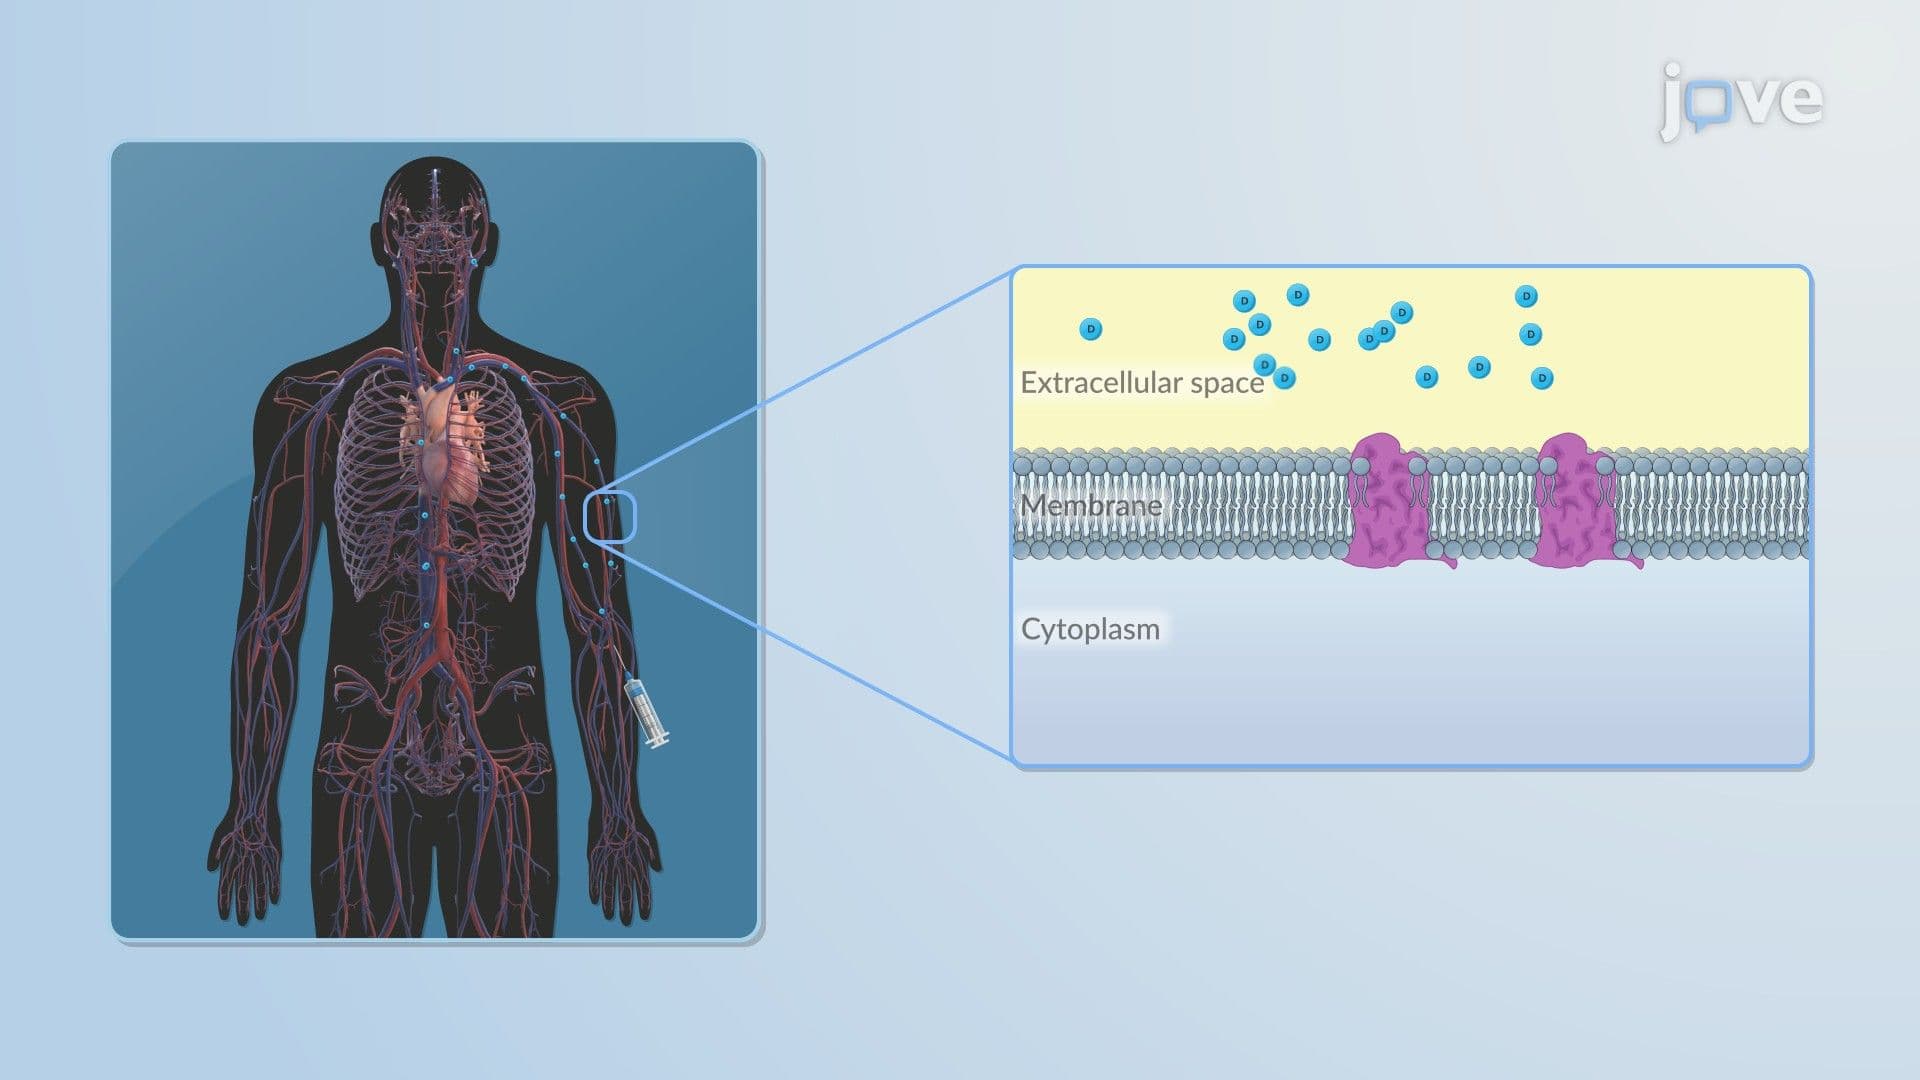
Pharmacokinetic–Pharmacodynamic Relationship: Dose to Pharmacological Effect