関連する実験動画
Updated: May 5, 2026
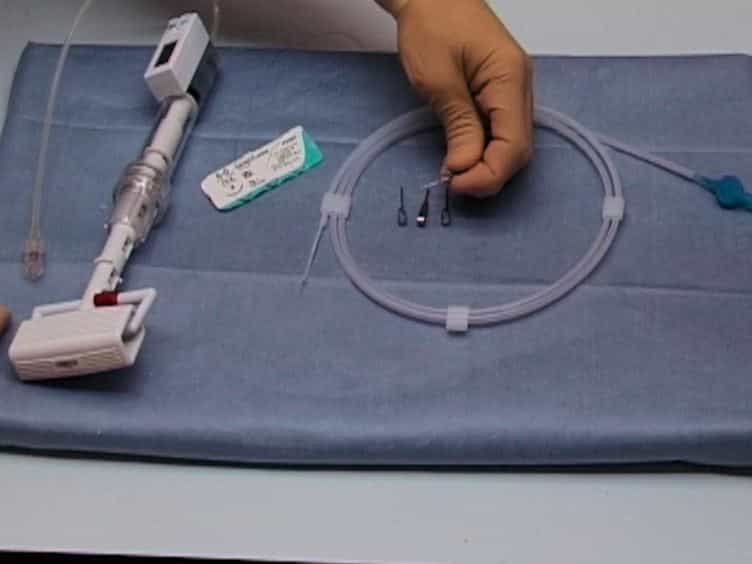
08:51

A New Murine Model of Endovascular Aortic Aneurysm Repair
Published on: July 7, 2013
13.7K
選択的な修復を拒むまたは不適格な患者における大きな腹部大動脈動脈瘤の破裂率
Frank A Lederle1, Gary R Johnson, Samuel E Wilson
1Department of Medicine, Veterans Affairs Medical Center, Minneapolis, Minn 55417, USA. frank.lederle@med.va.gov
JAMA
|June 8, 2002

まとめ
大量の腹部大動脈動脈瘤 (AAA) を有する高リスク患者は,かなりの破裂リスクに直面します. このリスクは,大きな動脈瘤直径,特に7.0cm以上で,著しく増加します.
科学分野:
- 血管外科 血管外科
- 大動脈動脈瘤の研究
- 患者リスクの階層化
背景:
- 腹動脈動脈瘤 (AAA) の修復は,高リスクの患者では,破裂が迫っているまで,しばしば延期されます.
- この集団における大きなAAAの破裂リスクに関するデータは限られている.
- 現在のガイドラインには,大型AAAの断裂リスクに関する正確なデータがない.
研究 の 目的:
- 大型の腹部大動脈動脈瘤 (AAA) の患者における破裂の発生率を決定する.
- AAA破裂リスクのデータを直径によって層分化して提供します.
- 高手術リスクのAAA患者に対する臨床的意思決定の情報提供.
主な方法:
- 47の退役軍人の医療センターで実施された前向きなコホート研究.
- 選択的な修理を予定している者を除く,少なくとも5.5cmのAAAを持つ,手術リスクの高い退役軍人198人を登録しました.
- 患者さんを平均1.52年間追跡し,AAA破裂の発生率を初期と到達直径によって評価した.
主要な成果:
- AAA破裂の可能性の1年間の発生率は,5.5-5.9cmの場合9.4%,6.0-6.9cmの場合10.2%,7.0cm以上AAAの場合32.5%でした.
- 直径8.0cmに達する動脈瘤は,6ヶ月以内に25.7%の破裂率を持っていた.
- 全体的な死亡率は57%で,検死を受けたのは46%でした.
結論:
- 高手術リスクの患者で,AAA ≥5.5cmの患者は,破裂のリスクが高い.
- AAA破裂の発生率は,動脈瘤の直径が増加するにつれて著しく上昇します.
- これらの発見は,大きなAAAを持つ高リスク患者への介入を慎重に検討する必要性を強調しています.
さらに関連する動画

関連する概念動画
 01:15
Aortic Regurgitation I: Introduction
1.6K
IntroductionAortic regurgitation is characterized by the backward flow of blood from the aorta into the left ventricle during diastole and arises from the improper closure of the aortic valve. This condition results in left ventricular volume overload and can stem from both acute and chronic etiologies, each contributing uniquely to the disease's progression and symptomatology.Acute and Chronic CausesAcute aortic regurgitation often results from events that suddenly impair the integrity of the...
1.6K
 01:25
Aortic Regurgitation III: Medical Management
598
Aortic regurgitation (AR) is when the aortic valve does not close or seal properly, leading to backward blood circulation from the aorta into the left ventricle during diastole. Common causes of AR include rheumatic heart disease, congenital valve defects, and aortic root dilation. Managing AR requires a multifaceted approach to alleviate symptoms, preserve left ventricular function, and address the underlying cause of the regurgitation. Patients with symptomatic AR or significant left...
598
 01:30
Aneurysm I: Introduction
658
An aortic aneurysm is a localized outpouching or dilation at a weak point in the artery wall. It may involve different parts of the aorta, such as the abdominal aorta, aortic arch, or thoracic aorta.Etiological factorsSeveral disorders are associated with aortic aneurysms.Congenital causes, such as primary connective tissue disorders like Marfan syndrome, impact the integrity and strength of connective tissues, notably affecting the aorta. Marfan syndrome is a genetic disorder that specifically...
658
 01:21
Aneurysm II: Clinical Manifestations and Diagnostic Studies
592
Thoracic, aortic arch and abdominal aneurysms are significant vascular conditions that can present with various clinical manifestations and lead to serious complications. Understanding these manifestations and the appropriate diagnostic studies is essential for effective management and treatment.Thoracic Aortic AneurysmsThoracic aortic aneurysms often remain asymptomatic until they reach a size that impinges on adjacent structures. They typically cause deep, diffuse chest pain that radiates to...
592
 01:26
Aneurysm III: Interprofessional Care
478
Aneurysm management involves either conservative medical therapy or surgical intervention, depending on the size and symptoms of the aneurysm. Conservative management is generally reserved for smaller, asymptomatic aneurysms, while larger or symptomatic aneurysms often necessitate surgical repair.Conservative Medical TherapyFor small, asymptomatic aneurysms, particularly abdominal aortic aneurysms (AAA) less than 5.5 centimeters in diameter, conservative medical therapy is recommended. This...
478
 01:22
Aneurysm IV: Nursing Management
625
Vigilant monitoring for aneurysm rupture is essential for patients undergoing aortic surgery.Preoperative Nursing ManagementContinuously monitor the patient for manifestations of aneurysm rupture, such as pallor, weakness, tachycardia, hypotension, abdominal, back, groin, or periumbilical pain, changes in consciousness, and a pulsating abdominal mass. Regularly assess the patient's peripheral pulses.Instruct the patient to consume a clear liquid diet the day before surgery and administer...
625