
アルツハイマー病の進行に対するロフェコキシブまたはナプロキセンとプラセボの効果:ランダム化制御試験
Paul S Aisen1, Kimberly A Schafer, Michael Grundman
1Department of Neurology, Georgetown University Medical Center, Washington, DC 20057, USA. psa@georgetown.edu
JAMA
|June 5, 2003

まとめ
ナプロキセンやロフェコキシブのような非ステロイド性抗炎症薬 (NSAIDs) は,アルツハイマー病 (AD) 患者における認知機能低下を1年以上にわたって遅らせなかった. この研究では,プラセボと比較して認知機能の有意な差は認められなかった.
科学分野:
- 神経科学は神経科学である.
- 薬理学 薬理学とは
- クリニカル・メディシン 臨床医学
背景:
- 炎症的メカニズムは,アルツハイマー病 (AD) の神経損傷に関与しています.
- 非ステロイド性抗炎症薬 (NSAIDs) は,抗炎症性によりADの進行を潜在的に変化させると仮定されています.
研究 の 目的:
- 選択性サイクロオキシゲナーゼ (COX) - 2阻害剤 (ロフェコキシブ) または従来の非選択性NSAID (ナプロクセン) の投与が軽度から中等度のAD患者の認知機能低下を遅らせるかどうかを評価する.
- これらのNSAIDの安全性と有効性をAD集団で評価する.
主な方法:
- 多センター,ランダム化,ダブルブラインド,プラセボ対照試験で,軽度から中度までのADの351人の参加者が参加しました.
- 参加者は1年間,毎日ロフェコキシブ (25 mg),ナプロキセンナトリウム (220 mg,毎日2回),またはプラセボを投与されました.
- 認知機能低下は,主にアルツハイマー病評価スケール-認知 (ADAS-Cog) のサブスケールスコアの1年間の変化で測定されました.
主要な成果:
- ナプロクセンもロフェコキシブも,1年後にプラセボと比較して,認知機能低下を遅らせる (ADAS-Cogスコア) 点で有意な差異を示さなかった.
- また,二次的結果測定では,活性治療群のいずれにも一貫した利点が示されませんでした.
- 疲労,めまい,高血圧,およびより深刻な有害事象の発生率の増加は,プラセボと比較して,活性薬群で観察されました.
結論:
- ロフェコキシブと低用量ナプロキセンは,軽度から中等度のアルツハイマー病患者の認知機能低下を遅らせるようには見えません.
- 発見は,ADにおける認知機能低下の経過を修正するためにこれらのNSAIDの使用を支持しません.
さらに関連する動画


関連する概念動画
 01:30
Cognitive Enhancers: Cholinesterase Inhibitors and NMDA Receptor Antagonists
Cognitive enhancers, also known as "smart drugs," are substances used to enhance memory, mental alertness, and concentration. These can be natural or synthetic and improve cognition in conditions like Alzheimer's disease (AD) and other neurodegenerative diseases. Some common examples include caffeine, amphetamines, methylphenidate, modafinil, arecoline, donepezil, vortioxetine, and piracetam. These enhancers work on the principle of synaptic plasticity and altered circuit function. They...
 01:26
Alzheimer's Disease: Overview
Alzheimer's Disease (AD) is a continually advancing neurodegenerative disorder, distinguished by escalating memory loss, cognitive dysfunction, and dementia. The disease unfolds in three stages: preclinical, mild cognitive impairment (MCI), and dementia. Its onset is insidious, and the progression gradual, with the cause not well explained by other disorders.
The clinical diagnosis of AD hinges on the presence of memory and other cognitive impairments. Biomarkers, such as changes in Aβ and tau...
The clinical diagnosis of AD hinges on the presence of memory and other cognitive impairments. Biomarkers, such as changes in Aβ and tau...
 01:22
Alzheimer's Disease: Treatment
Alzheimer's Disease (AD), a neurodegenerative disorder, is pathologically identified by amyloid plaques and neurofibrillary tangles composed of tau protein. AD pharmacotherapy aims to manage cognitive symptoms, delay disease progression, and treat behavioral symptoms. The treatment is primarily symptomatic and palliative, with no definitive disease-modifying therapy available. Cholinesterase inhibitors, including donepezil (Aricept), rivastigmine (Exelon), and galantamine (Razadyne), are...
 01:27
Pharmacodynamics in Geriatric Patients: Effects of Age
Age-related pharmacokinetic changes are extensively documented, but understanding age-related pharmacodynamic alterations is relatively limited. This knowledge gap can be partly attributed to the complexity of developing appropriate measures of drug responses compared to bioanalytical methods for determining drug concentrations.Most information regarding age-related differences in human pharmacodynamics originates from cross-sectional studies. However, these studies assume that observed mean...
 01:29
Alzheimer Disease l: Introduction
Alzheimer disease is a chronic, progressive, and irreversible neurodegenerative disorder and the most common cause of dementia in older adults. It leads to gradual neuronal loss, causing cognitive decline, behavioral changes, and loss of functional independence.Risk Factors and EtiologyThe disease is multifactorial. Age is the strongest risk factor, with prevalence doubling every 5 years after age 65. Genetic factors include mutations in genes such as APP, PSEN1, and PSEN2, which are associated...
 01:23
Alzheimer Disease ll: Pathophysiology
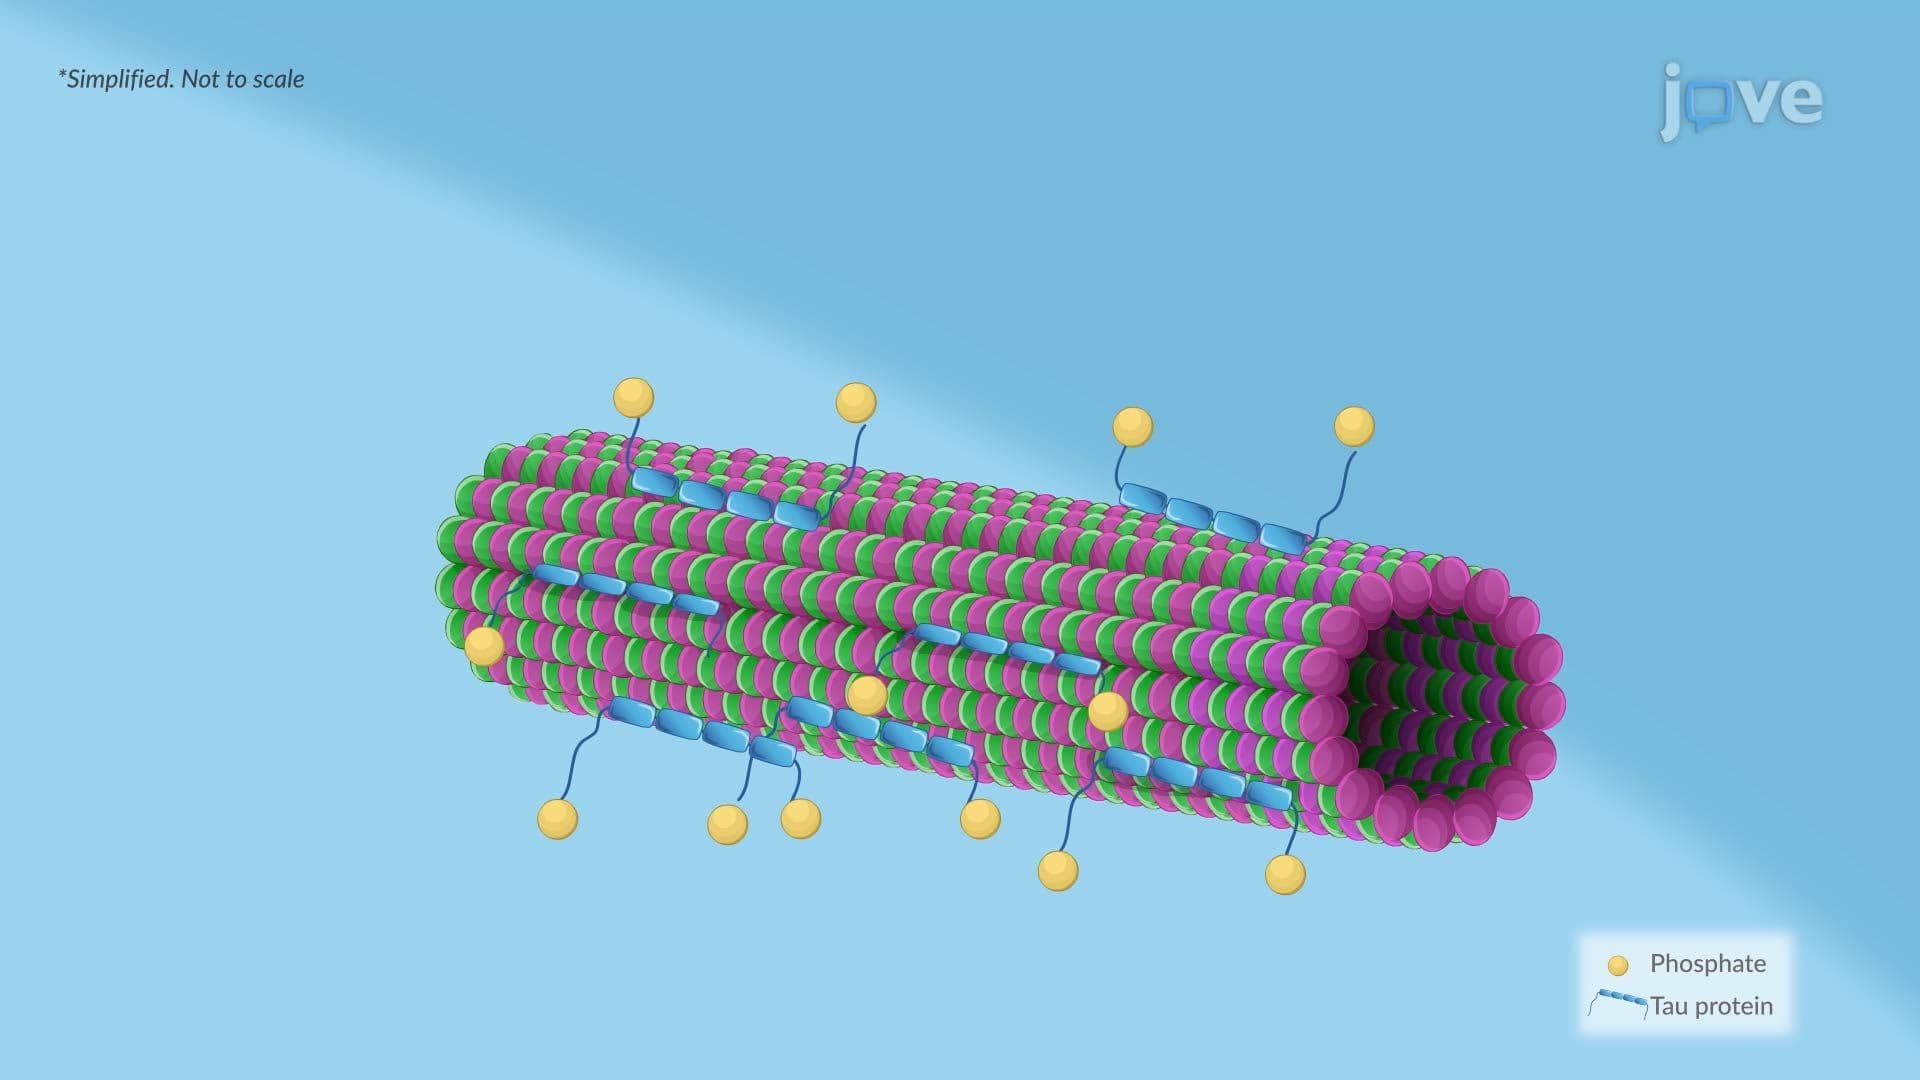
Alzheimer disease involves structural changes in the brain that begin long before symptoms appear. The most distinctive features are extracellular neuritic plaques and intracellular neurofibrillary tangles.Neuritic plaques form in the cerebral cortex and around blood vessels. These plaques contain a dense core of beta-amyloid (Aβ)—a toxic protein fragment that clumps outside neurons. The core is surrounded by damaged neuronal extensions, as well as reactive astrocytes and microglia. Abnormal...