関連する実験動画
Updated: Jul 27, 2026
07:34

Use of Animal Model of Sepsis to Evaluate Novel Herbal Therapies
Published on: April 11, 2012
髄膜球菌性毒ショックにおける心筋機能不全におけるインタールイキン6の役割
Nazima Pathan1, Cheryl A Hemingway, Ash A Alizadeh
1Department of Paediatrics, Imperial College of Science, Technology and Medicine, W2 1PG, London, UK. n.pathan@imperial.ac.uk
Lancet (London, England)
|January 24, 2004

まとめ
インタールイウキン6 (IL-6) は,髄膜球菌性性ショックにおける心筋縮を引き起こす. この炎症性サイトカインは,心臓機能不全と疾患の重症度の重要な要因であり,潜在的な治療目標を提供します.
科学分野:
- 心臓病学 心臓病学
- 免疫学 免疫学とは
- 感染症 感染症とは
背景:
- 心筋不全はセプティックショックにおいて極めて重要であり,臓器の損傷や死亡につながる.
- セプシスは,心臓の収縮性を損なう要因の放出を誘発します.
- 髄膜炎球菌性 сепティックショックにおけるこれらの心筋緩剤の特定は極めて重要です.
研究 の 目的:
- 髄膜球菌性 септик шокにおける心筋縮の特定のメディエーターを特定する.
- セプシス誘発の心臓機能不全における血清因子の役割を調査する.
主な方法:
- 遺伝子発現プロファイリング,タンパク質,細胞分析を組み合わせた.
- メンニゴコックスの暴露後の血液中のアップレギュレーション遺伝子を特定しました.
- 選択された熱安定タンパク質 (12-25 kDa) を潜在的心筋抑うつ因子として用いる.
主要な成果:
- 174のアップレギュレーション遺伝子を特定し,6つのコード化されたタンパク質が,心筋抑うつ因子の特性と一致しました.
- インタールイキン6 (IL-6) は,インビトロにおいて,ミオカルディアの有意な低下を誘発した.
- IL-6の除去により,患者の血清と細胞のスーパーナタンにおけるネガティブなイノトロピック活性が廃止された.
- 血清のIL-6レベルは,小児における心筋機能不全と疾患の重症度と相関する.
結論:
- インターリューキン6は,髄膜球菌疾患における心筋縮の重要な媒介体である.
- IL-6とその下流経路は,髄膜炎球菌性結核ショックの潜在的な治療標的を代表しています.
関連する概念動画
 01:21
Myocarditis I: Introduction
Myocarditis is inflammation of the myocardium, which is the muscular layer of the heart.EtiologyMyocarditis has a diverse etiology, including a wide range of infectious and non-infectious causes:Infectious CausesViral: Common viruses include Coxsackie A and B, adenovirus, parvovirus B19, enteroviruses, and influenza A.Bacterial: Examples include infections caused by Streptococcus, Staphylococcus, and Mycoplasma species.Rickettsial: Infections like Rocky Mountain spotted fever can result in...
 01:27
Myocarditis II: Clinical Features and Diagnostic Tests
Myocarditis is an inflammation of the heart muscle. The symptoms vary widely, encompassing asymptomatic presentations to severe, acute manifestations.Clinical PresentationAsymptomatic cases: In some instances, myocarditis may be asymptomatic, with the infection resolving without intervention. These cases often go undetected unless discovered incidentally through diagnostic imaging or tests conducted for other reasons.General Early Symptoms: Early symptoms of myocarditis are non-specific and can...
 01:14
Myocarditis III: Medical Management
Myocarditis: Comprehensive Medical ManagementMyocarditis, the heart muscle inflammation, requires a comprehensive medical management strategy that addresses the underlying cause, provides supportive care, manages symptoms, and reduces cardiac workload.Infections and Autoimmune CausesAdminister appropriate antimicrobial therapy when an infectious agent causes myocarditis. For instance, penicillin treats infections caused by Group A Streptococcus. In cases where autoimmune processes are...
 01:24
Bacterial Meningitis
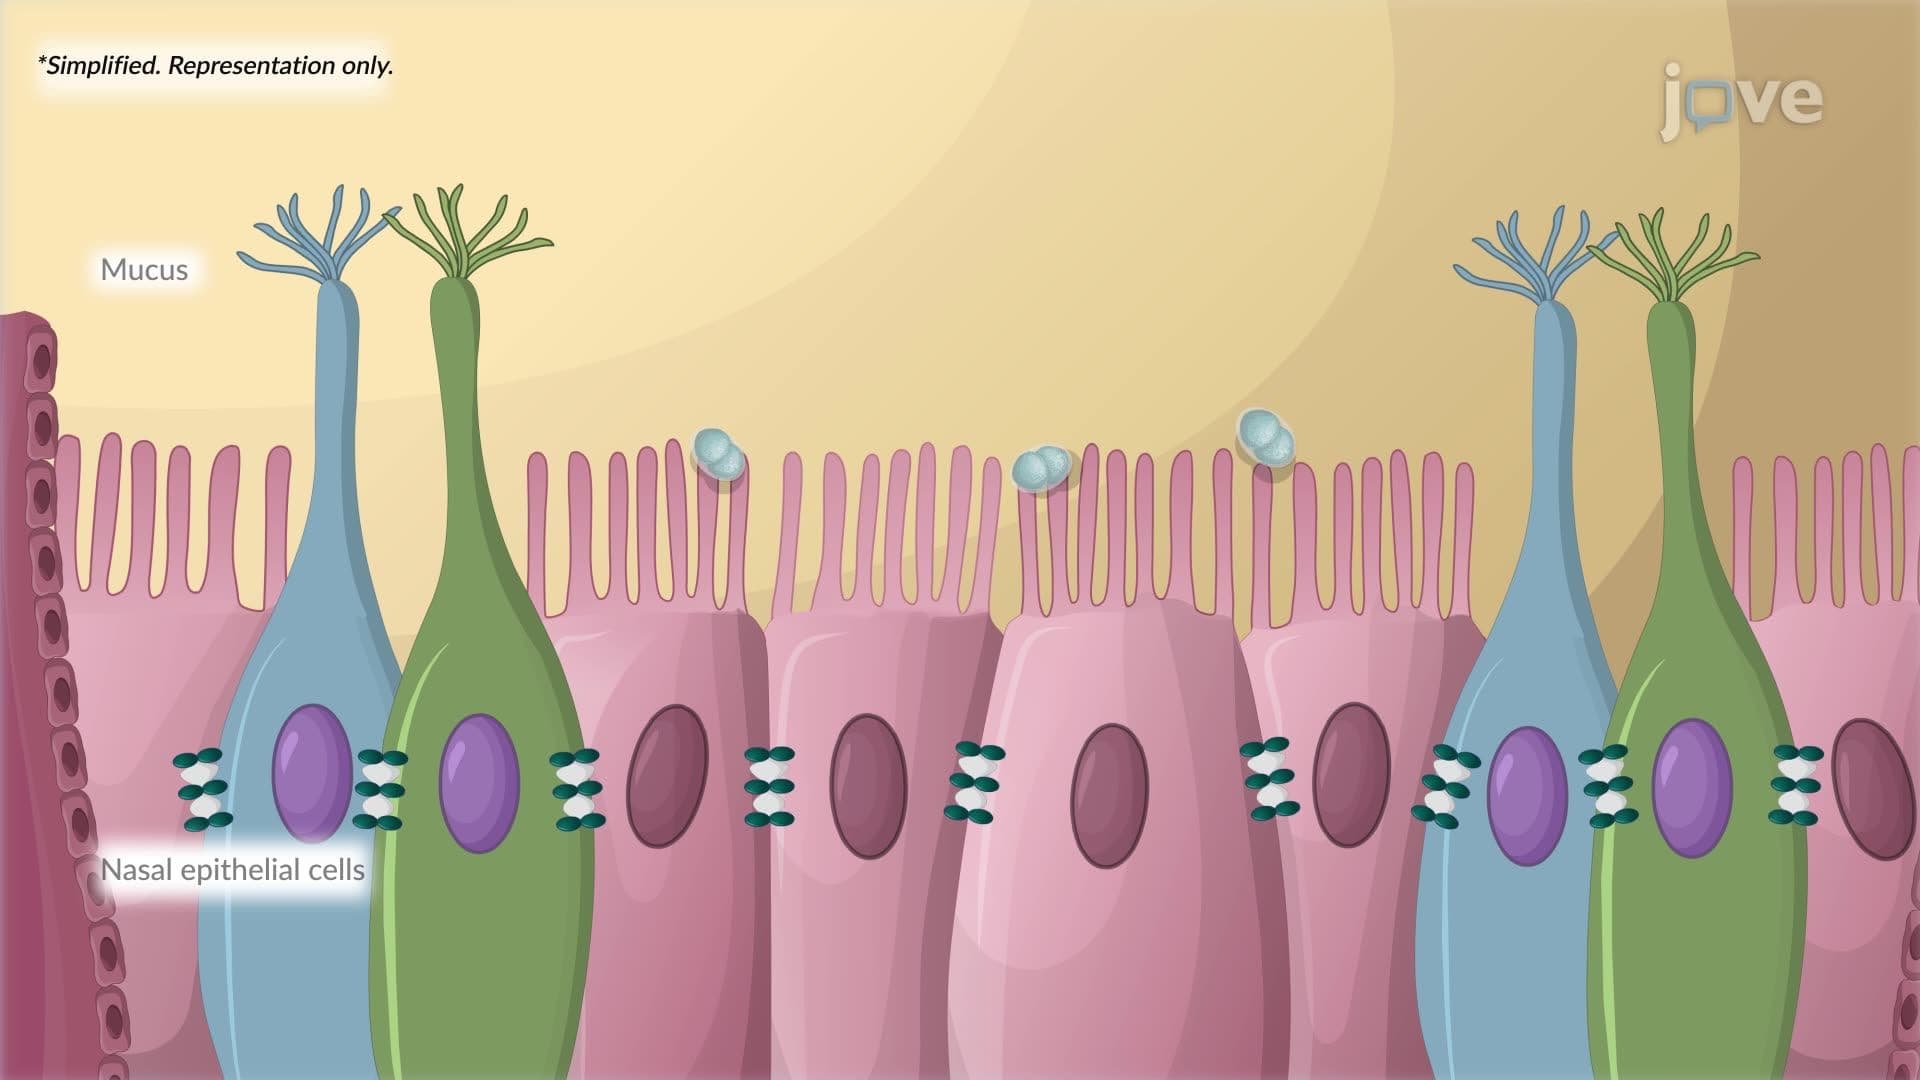
Bacterial meningitis is a severe infectious disease involving inflammation of the meninges, the protective membranes surrounding the brain and spinal cord. It occurs when pathogenic bacteria cross the blood–brain barrier and enter the cerebrospinal fluid. Common causative organisms include Neisseria meningitidis, Streptococcus pneumoniae, Haemophilus influenzae type b, Listeria monocytogenes, and Escherichia coli K1. The exact route of entry varies by pathogen and host condition.Routes of Entry...
 01:25
Acute Inflammation III: Local and Systemic Effects
Acute inflammation produces a coordinated set of local and systemic changes that limit injury, eliminate pathogens, and initiate repair. These responses arise within minutes of infection, trauma, or chemical insult and are driven by vascular alterations and leukocyte-derived mediators. When the stimulus resolves, the reaction typically abates within days.Local EffectsAt the site of injury, arteriolar vasodilation increases blood flow, resulting in redness and warmth. Simultaneously, increased...
 01:26
Bacterial Meningitis II: Pathophysiology
Bacterial meningitis typically begins when pathogens such as Neisseria meningitidis and Streptococcus pneumoniae colonize the nasopharynx and invade the bloodstream. This process is facilitated by bacterial virulence factors, such as polysaccharide capsules, which resist phagocytosis and complement-mediated killing. Less commonly, bacteria reach the central nervous system via contiguous spread from infections like otitis media or sinusitis, through congenital or acquired dural defects, or...