

初等医療におけるアルツハイマー病の高齢者の共同ケアの有効性:ランダム化制御試験
Christopher M Callahan1, Malaz A Boustani, Frederick W Unverzagt
1Indiana University Center for Aging Research, Regenstrief Institute Inc, Indiana University School of Medicine, Indianapolis 46202, USA. ccallaha@iupui.edu
JAMA
|May 11, 2006

まとめ
共同ケアモデルは,アルツハイマー病のケア品質を大幅に改善し,プライマリケアにおける行動症状を軽減しました. 介護者はまた,不安やうつ病が少なくなったと報告しました.
科学分野:
- ゲロントロジーはゲロントロジーの学科です.
- プライマリーケア医療 プライマリーケア医療
- 神経学 神経学とは
背景:
- プライマリケア医師は,しばしば認知症のケアを管理し,実践環境の課題に直面します.
- 高品質の認知症ケアは,高齢者とその介護者にとって極めて重要です.
- アルツハイマー病 (AD) は,初等医療施設内で専門的な管理戦略を必要とします.
研究 の 目的:
- アルツハイマー病患者のケア品質の向上における共同ケアモデルの有効性を評価する.
- 統合医療が患者と介護者の健康状態に与える影響を評価する.
- 共同ケアが認知症 (BPSD) の行動的および心理的な症状の管理を改善するかどうかを判断する.
主な方法:
- アルツハイマー病を患っている153人の高齢者とその介護者を対象とした臨床試験です.
- 参加者のランダム化により,共同ケアマネジメントまたは拡張通常のケア.
- 介入は,高度な実務看護師が率いる学際的なチームによる1年間のケアマネジメントであり,BPSDの非薬理学的管理に焦点を当てました.
主要な成果:
- コラボレーティブケア患者の場合,コレネステラス阻害剤と抗うつ剤を投与する確率が高かった.
- 認知症 (BPSD) の行動的および心理的な症状の有意な減少は,12ヶ月および18ヶ月 (NPIスコア) で観察されました.
- 介護者は,苦痛とうつ病の症状の有意な改善を報告しました.
結論:
- 共同ケアモデルは,初等医療施設におけるアルツハイマー病のケア品質を効果的に改善します.
- このモデルは,BPSDを大幅に削減し,介護者の幸福度を高めます.
- 改善は,抗精神病薬や鎮静催眠薬の使用を増やすことなく達成されました.

関連する概念動画
 01:26
Alzheimer's Disease: Overview
1.7K
Alzheimer's Disease (AD) is a continually advancing neurodegenerative disorder, distinguished by escalating memory loss, cognitive dysfunction, and dementia. The disease unfolds in three stages: preclinical, mild cognitive impairment (MCI), and dementia. Its onset is insidious, and the progression gradual, with the cause not well explained by other disorders.
The clinical diagnosis of AD hinges on the presence of memory and other cognitive impairments. Biomarkers, such as changes in Aβ...
The clinical diagnosis of AD hinges on the presence of memory and other cognitive impairments. Biomarkers, such as changes in Aβ...
1.7K
 01:22
Alzheimer's Disease: Treatment
1.3K
Alzheimer's Disease (AD), a neurodegenerative disorder, is pathologically identified by amyloid plaques and neurofibrillary tangles composed of tau protein. AD pharmacotherapy aims to manage cognitive symptoms, delay disease progression, and treat behavioral symptoms. The treatment is primarily symptomatic and palliative, with no definitive disease-modifying therapy available. Cholinesterase inhibitors, including donepezil (Aricept), rivastigmine (Exelon), and galantamine (Razadyne), are...
1.3K
 01:27
Pharmacodynamics in Geriatric Patients: Effects of Age
367
Age-related pharmacokinetic changes are extensively documented, but understanding age-related pharmacodynamic alterations is relatively limited. This knowledge gap can be partly attributed to the complexity of developing appropriate measures of drug responses compared to bioanalytical methods for determining drug concentrations.Most information regarding age-related differences in human pharmacodynamics originates from cross-sectional studies. However, these studies assume that observed mean...
367
 01:27
Peripheral Artery Disease III: Interprofessional Care
655
Peripheral Artery Disease (PAD) is characterized by narrowed arteries that diminish blood flow to the extremities. Effective management of PAD requires an interprofessional approach involving various healthcare professionals. The critical aspects of interprofessional care for PAD patients focus on risk factor modification, drug therapy, exercise therapy, nutrition therapy, critical limb ischemia care, and interventional radiology and surgical procedures.The primary treatment goal for PAD...
655
 01:29
Alzheimer Disease l: Introduction
21
Alzheimer disease is a chronic, progressive, and irreversible neurodegenerative disorder and the most common cause of dementia in older adults. It leads to gradual neuronal loss, causing cognitive decline, behavioral changes, and loss of functional independence.Risk Factors and EtiologyThe disease is multifactorial. Age is the strongest risk factor, with prevalence doubling every 5 years after age 65. Genetic factors include mutations in genes such as APP, PSEN1, and PSEN2, which are associated...
21
 01:23
Alzheimer Disease ll: Pathophysiology
35
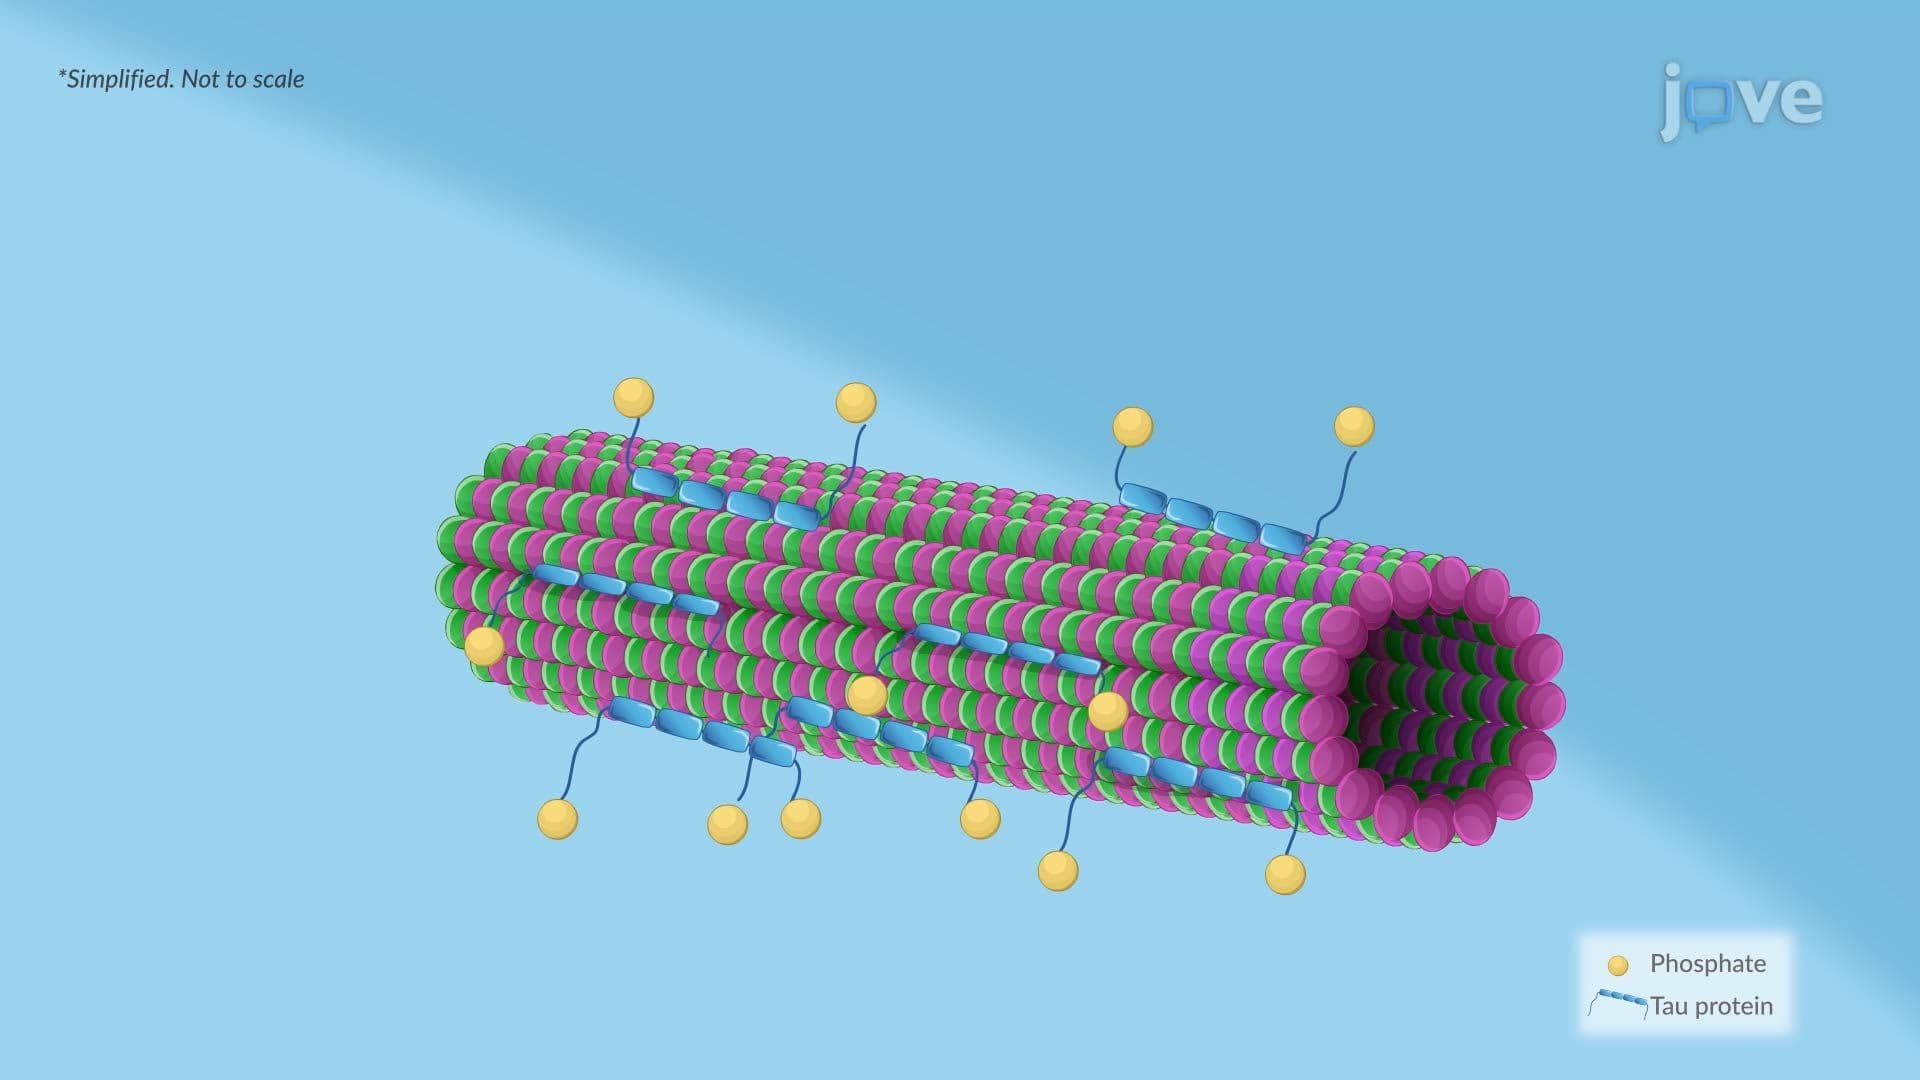
Alzheimer disease involves structural changes in the brain that begin long before symptoms appear. The most distinctive features are extracellular neuritic plaques and intracellular neurofibrillary tangles.Neuritic plaques form in the cerebral cortex and around blood vessels. These plaques contain a dense core of beta-amyloid (Aβ)—a toxic protein fragment that clumps outside neurons. The core is surrounded by damaged neuronal extensions, as well as reactive astrocytes and...
35