関連する実験動画
Updated: Jun 23, 2026
08:00
Ambulatory ECG Recording in Mice
Published on: May 28, 2010
マウスにおけるA1-アデノシン受容体の過剰発現は,心臓の形態学と機能に悪影響を及ぼすが,逆戻り可能な変化をもたらします
Hajime Funakoshi1, Tung O Chan, Julie C Good
1Center for Translational Medicine, Department of Medicine, Jefferson Medical College, Philadelphia, PA 19107, USA.
Circulation
|November 8, 2006

まとめ
心臓におけるアデノシン受容体 (AR) の過剰発現は,拡張性心筋病と死亡を引き起こす可能性があります. しかし,A1-ARの発現を成人期まで遅らせることは,心臓病理を減少させますが, cardiac pathologyを排除することはできず,心不全の洞察を提供します.
科学分野:
- 心血管生物学 心血管生物学
- 分子心臓病学 分子心臓病学
- アデノシン受容体シグナリング
背景:
- アデノシン受容体 (ARs),特にA1-ARとA3-ARは,アデノシン媒介の心臓保護に関連しています.
- 逆説的に,A1-ARとA3-ARの過剰発現は,変化した心臓のフェノタイプと相関しています.
- 心臓リモデリングにおけるARシグナル伝達の時間的動態については,さらなる調査が必要である.
研究 の 目的:
- A1-ARシグナル伝達と心臓リモデリングの間の時間的関係を調査する.
- 心臓特異的な方法で,制御されたA1-AR過剰発現の影響を評価する.
主な方法:
- マウスの制御されたA1-AR過剰発現のために,心臓特異のテトラサイクリン調節プロモーターを使用した.
- 構成的および遅延A1-AR誘導下での検査されたフェノタイプ,生存率,心臓機能,および遺伝子発現.
- A1-AR誘導中止が心臓機能不全に与える影響を評価した.
主要な成果:
- 構成的なA1-AR過剰発現は,膨張性心筋症,心室機能の低下,心拍数低下,および6〜12週間以内に死亡につながりました.
- 成人期までA1-AR発現を遅らせることで生存率が改善 (30週で90%以上) され,即時の心臓機能不全が予防されました.
- 遅いA1-AR誘導は,それでも軽度の心筋病変,加速した高縮,圧力の過負荷下での膨張,Aktのリン酸化と線維症の低下をもたらした.
結論:
- 頑丈で構成的なA1-AR過剰発現は,拡張性心筋病を誘発する.
- 遅れたA1-AR発現は,心臓病理を改善しますが,完全に予防することはありません.
- 誘導可能なA1-ARマウスモデルは,心不全におけるアデノシンシグナル伝達と,選択的対非選択的AR活性化の結果についての洞察を提供します.


関連する概念動画
 01:27
Adrenergic Receptors (Adrenoceptors): Classification
Adrenergic receptors, or adrenoceptors, respond to the autonomic neurotransmitter noradrenaline and other endogenous catecholamine agonists. They are classified into two main families, α and β, based on their pharmacological response and are further subdivided depending on their location, elicited response, and affinity to specific agonists or antagonists.
α-Adrenoceptors
α-Adrenoceptors are classified into two main subtypes: α1 and α2. The α1 adrenoceptors, which are found on postsynaptic...
α-Adrenoceptors
α-Adrenoceptors are classified into two main subtypes: α1 and α2. The α1 adrenoceptors, which are found on postsynaptic...
 01:31
Adrenergic Receptors: ɑ Subtype
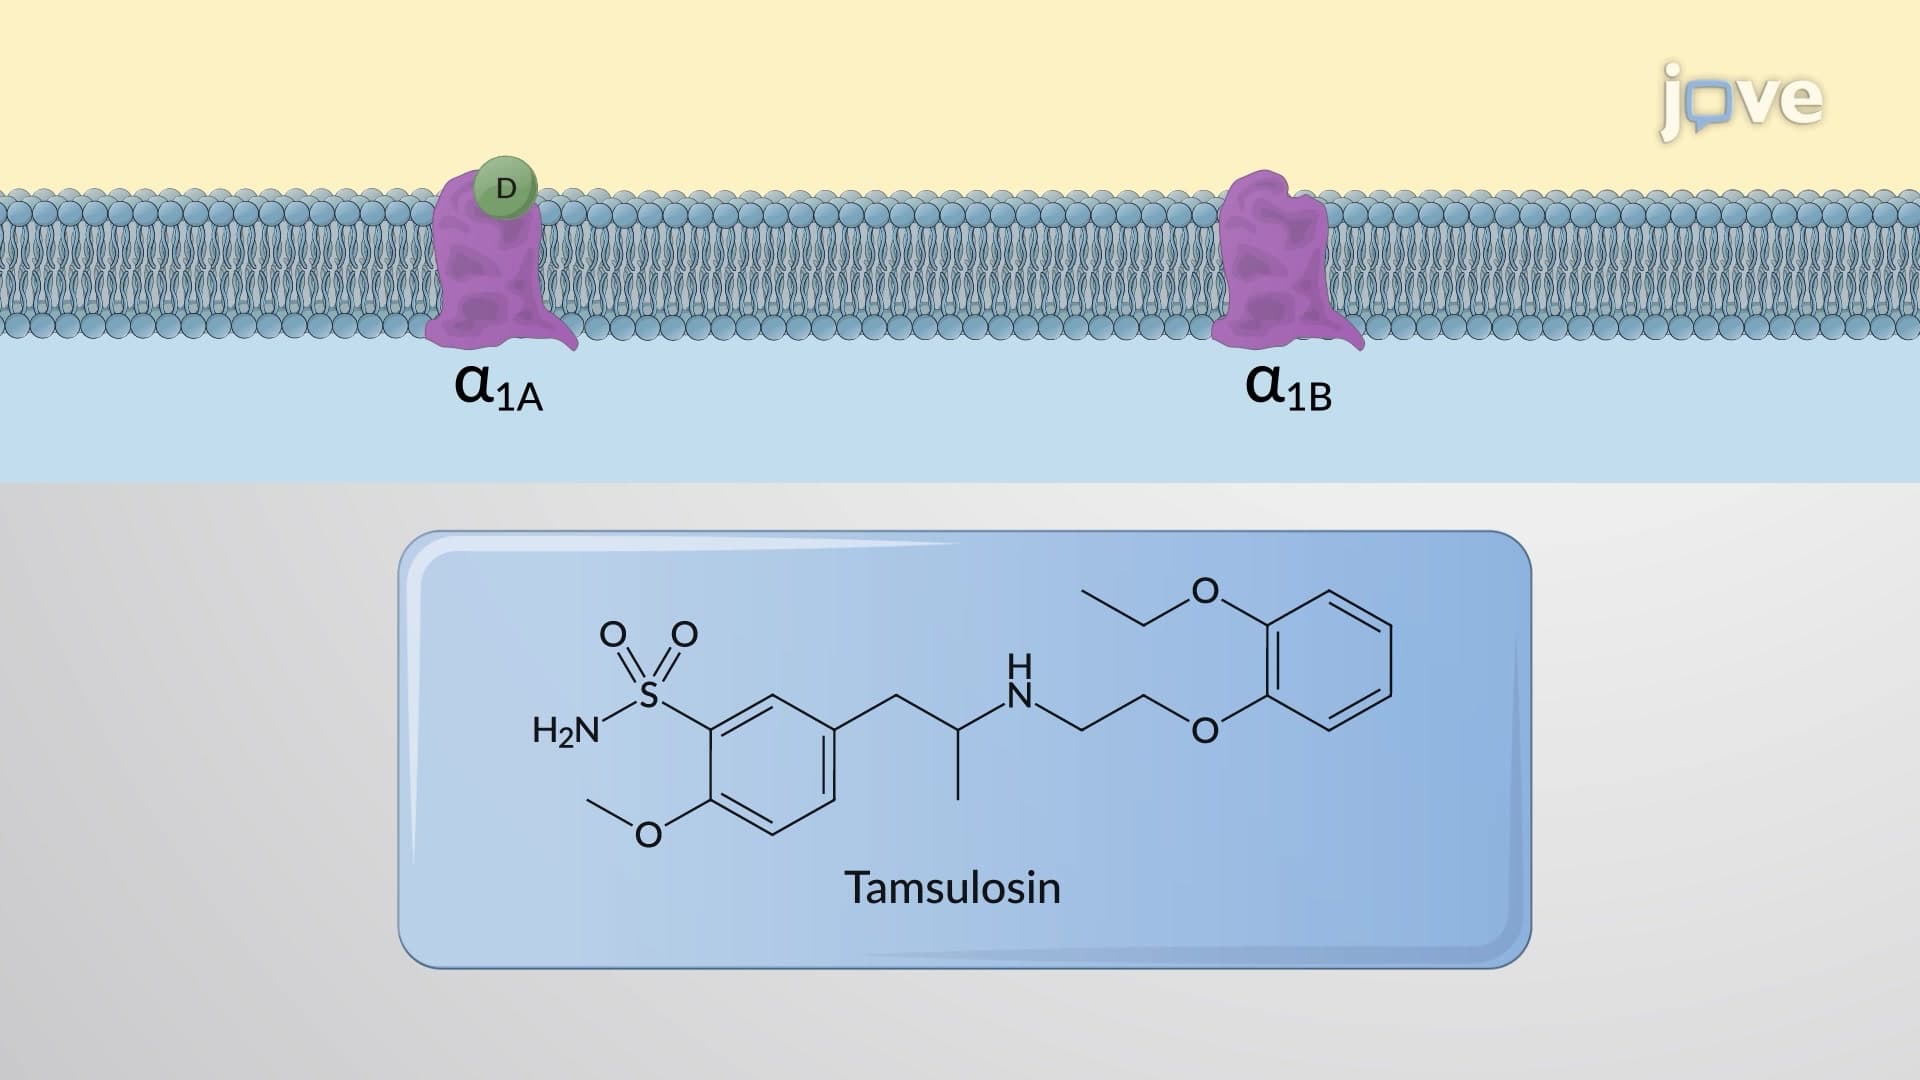
Adrenoceptors are classified into α and ꞵ classes based on their potencies to catecholamine agonists. α-adrenoceptors show the following order of catecholamine potency:
Adrenaline ≥ Noradrenaline >> Isoprenaline
α-adrenoceptors are further divided into α1 and α2-adrenoceptors.
α1-Adrenoceptors: These receptors are located postsynaptically on the effector organs and cause constriction of smooth muscle mediated by activation of phospholipase C—inositol-1,4,5-trisphosphate...
 01:26
Adrenergic Receptors: β Subtype
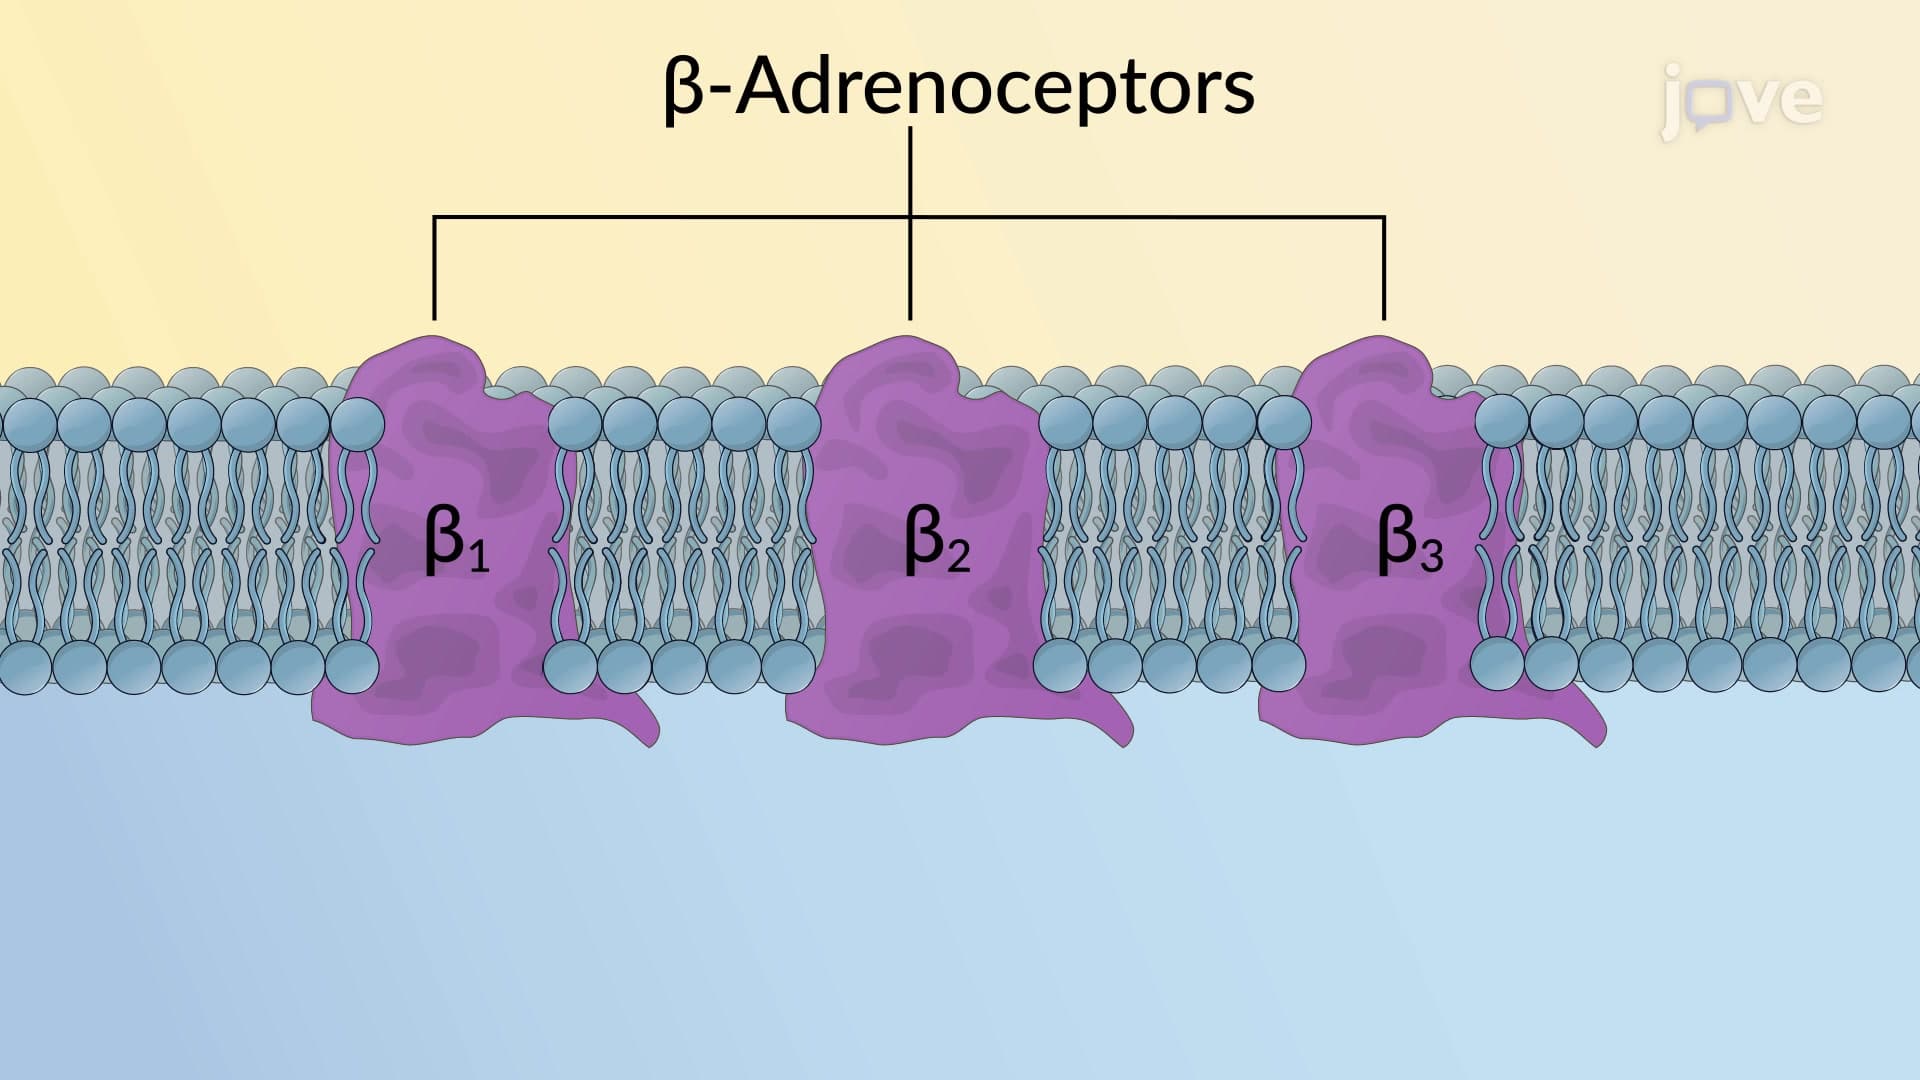
β-adrenoceptors have varied sensitivities towards adrenaline, noradrenaline, and isoprenaline. The order of agonist potency is as follows:
Isoprenaline > Adrenaline > Noradrenaline
Neurotransmitter binding to these receptors causes activation of adenylyl cyclase resulting in increased concentrations of cAMP and modulation of calcium ion channels within the cell. They are further classified into β1, β2, and β3 subtypes.
β1-adrenoceptors: β1-adrenoceptors have equal affinities for...
 01:22
Adrenergic Antagonists: Pharmacological Actions of ɑ-Receptor Blockers
α-Adrenergic antagonists, known as α-blockers, exert their effects by inhibiting α-adrenoceptors, leading to specific physiological actions. α1-blockers and α2-blockers have distinct pharmacological actions and therapeutic applications.
α1-blockers: These drugs inhibit α1-adrenoceptors on smooth muscle cells, resulting in vasodilation. This vasodilation lowers blood pressure, making α1-blockers valuable in treating hypertension. Additionally, α1-blockers effectively address urinary obstruction...
α1-blockers: These drugs inhibit α1-adrenoceptors on smooth muscle cells, resulting in vasodilation. This vasodilation lowers blood pressure, making α1-blockers valuable in treating hypertension. Additionally, α1-blockers effectively address urinary obstruction...
 01:26
Heart Failure Drugs: Inhibitors of Renin-Angiotensin System
The activation of the sympathetic nervous system and the renin-angiotensin-aldosterone system (RAAS) contributes to cardiac remodeling, and inhibiting the RAAS is a pharmacological target in heart failure management. As a result, neurohumoral modulation is a crucial treatment principle for managing heart failure. This approach involves using medications like ACE inhibitors (ACEIs), angiotensin receptor blockers (ARBs), β-blockers, mineralocorticoid receptor antagonists (MRAs), and neutral...
 01:29
Heart Failure II: Pathophysiology
Systolic Heart Failure and Compensatory MechanismsSystolic heart failure (also termed HFrEF, Heart Failure with Reduced Ejection Fraction) is the most prevalent type of heart filure. It results in a decreased volume of blood being pumped from the ventricle. The aortic arch and carotid sinuses have baroreceptors that detect reduced blood pressure, triggering the sympathetic nervous system (SNS) to release epinephrine and norepinephrine. Initially, this response aims to boost heart rate and...