関連する実験動画
Updated: Jun 26, 2026
07:35
Gene Transfer for Ischemic Heart Failure in a Preclinical Model
Published on: May 15, 2011
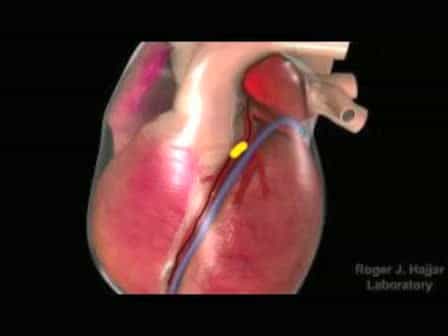
心筋アデノ関連ウイルスの血清型6βARKct遺伝子治療は,慢性心不全の心臓機能を改善し,神経ホルモン軸を正常化する
Giuseppe Rengo1, Anastasios Lymperopoulos, Carmela Zincarelli
1Center for Translational Medicine, Thomas Jefferson University, Philadelphia, PA 19107, USA.
Circulation
|December 24, 2008

まとめ
心不全 (HF) のラットでAAV6-betaARKctを用いた長期間の遺伝子治療により,心臓機能が改善され,リモデリングが逆転しました. このアプローチは,HFに対する持続的な治療上の利点を提供し,ベータブロッカー単独のパフォーマンスを上回ります.
科学分野:
- 心臓病学 心臓病学
- 分子医学は分子医学である.
- 遺伝子療法の遺伝子治療法
背景:
- Gタンパク質結合受容体キナーゼ2 (GRK2) のアップレギュレーションは,機能不全した心筋に,ベータアドレナリン受容体 (β-AR) のシグナル伝達と心臓機能を損なう.
- ペプチドβARKctはGRK2を阻害し,βARシグナル伝達を改善し,臨床前の心不全 (HF) モデルにおいて有望であることを示しています.
- この研究では,アデノ関連ウイルスの血清型6型 (AAV6) を用いて,安定した心筋筋遺伝子配送のためのHFにおける長期βARKct発現を調査しています.
研究 の 目的:
- 心不全のラットモデルにおけるbetaARKctによる長期の心臓遺伝子療法の有効性を評価する.
- AAV6媒介のβARKct投与が心機能,再構成,および神経ホルモン状態に与える影響を評価する.
- betaARKct遺伝子療法の治療効果を,同時にベータブロッカーの治療を併用して,併用せずに比較する.
主な方法:
- ネズミでは心不全が誘発され,その後,ベータARKctまたは緑色光タンパク質 (対照) を有するAAV6の直接心内注射が行われました.
- ベータブロッカーメトプロロールの併用投与は,別々のグループで評価されました.
- 心臓の機能,左心室の改造,神経ホルモンの状態は,出産後少なくとも12週間で評価されました.
主要な成果:
- AAV6媒介のベータARKctの投与は,左心室で強固で長期的なトランスゲン発現をもたらした.
- betaARKctは心臓の収縮性を著しく改善し,左心室の再構築を逆転させました.
- カテコアミンとアルドステロンを含む神経ホルモンの状態は正常化し,心臓のβARシグナル伝達が回復した. メトプロロールは単独でさらなる悪化を防ぎましたが,収縮性を改善することはありませんでした.
結論:
- 長期にわたるAAV6-betaARKct遺伝子治療は,全般的な心臓機能の改善を維持し,心不全のリフォームを逆転させます.
- 治療効果は,神経ホルモンのシグナル伝達軸の正常化に部分的に起因する.
- betaARKct遺伝子治療は,心不全の長期的な治療の可能性を示しており,ベータブロッカーと互換性を持ちながら,単独でベータブロッカーに優れている結果を示しています.

関連する概念動画
 01:26
Heart Failure Drugs: Inhibitors of Renin-Angiotensin System
The activation of the sympathetic nervous system and the renin-angiotensin-aldosterone system (RAAS) contributes to cardiac remodeling, and inhibiting the RAAS is a pharmacological target in heart failure management. As a result, neurohumoral modulation is a crucial treatment principle for managing heart failure. This approach involves using medications like ACE inhibitors (ACEIs), angiotensin receptor blockers (ARBs), β-blockers, mineralocorticoid receptor antagonists (MRAs), and neutral...
 01:29
Cardiomyopathy III: Hypertrophic Cardiomyopathy
Hypertrophic cardiomyopathy, or HCM, is an autosomal dominant genetic disorder characterized by asymmetric left ventricular hypertrophy without ventricular dilation. It is more common in men and is typically diagnosed in young, athletic adults.EtiologyHCM is primarily genetic and is caused by mutations in genes encoding sarcomeric proteins. Researchers have identified over 1400 mutations across at least 11 different genes. Among these, the most frequently occurring mutations are found in the...
 01:29
Cardiomyopathy IV: Restrictive Cardiomyopathy
Restrictive cardiomyopathy (RCM) is a rare heart muscle disease characterized by impaired ventricular filling due to stiffened ventricular walls, leading to significant diastolic dysfunction.EtiologyRestrictive cardiomyopathy can arise from both inherited and acquired diseases, many of which are systemic. It is categorized into four main types: infiltrative, storage, non-infiltrative, and endomyocardial diseases.Infiltrative diseases, such as amyloidosis, lead to RCM by depositing amyloid...
 01:30
Cardiomyopathy II: Dilated Cardiomyopathy
Dilated cardiomyopathy, or DCM, is a progressive myocardial disorder characterized by ventricular chamber dilation and contractile dysfunction.EtiologyVarious factors can cause DCM, including hypertension and heavy alcohol intake, which contribute to the weakening and enlargement of the heart muscle. Viral infections, such as Coxsackievirus B, adenoviruses, and influenza, can lead to DCM by causing inflammation and damage to heart tissue. Certain chemotherapeutic agents, including daunorubicin,...
 01:29
Cardiomyopathy VI: Nursing Management
Assessment: Nursing management of patients with cardiomyopathy begins with a thorough assessment of the patient's history, including a family history of cardiomyopathy or sudden cardiac death, personal history of heart disease, hypertension, diabetes, and any alcohol consumption or drug use.During the physical examination, assess vital signs, look for signs of heart failure (such as edema, jugular venous distention, and cyanosis), auscultate for abnormal heart sounds (like murmurs and gallops),...
 01:22
Heart Failure VI: Adjunct Therapies
Additional therapies for treating patients with heart failure (HF) may include procedural interventions, supplemental oxygen, the management of sleep disorders, and nutritional therapy.Procedural InterventionsImplantable Cardioverter-Defibrillator: For patients at risk of life-threatening arrhythmias due to severe left ventricular dysfunction, an Implantable Cardioverter-Defibrillator (ICD) can detect and terminate these arrhythmias, preventing sudden cardiac death and improving survival rates.