関連する実験動画
Updated: May 6, 2026

12:08
Improving IV Insulin Administration in a Community Hospital
Published on: June 11, 2012
19.7K
深刻な病気と厳格な血糖コントロールによる治療から4年後の子供の神経認知発達:ランダム化制御試験
Dieter Mesotten1, Marijke Gielen, Caroline Sterken
1Department of Intensive Care Medicine, Catholic University of Leuven, Leuven, Belgium.
JAMA
|October 27, 2012

まとめ
小児重症病棟での厳格なグルコースコントロール (TGC) は,長期的な神経発達を害しませんでした. このアプローチは低血糖症を増加させる一方で,子どもの知性や全体的な成績に悪影響を及ぼさなかった.
科学分野:
- 小児重症治療医療は,小児重症治療医療である.
- 神経発達に関する結果
- グルコース管理について
背景:
- 小児集中治療における厳格なグルコースコントロール (TGC) は,罹病率と死亡率を低下させ,低血糖症を増加させた.
- 高血糖症と低血糖症の両方が発達中の脳に与える潜在的な悪影響について懸念がありました.
研究 の 目的:
- ICUでTGCで治療された子供の長期的な神経発達のアウトカムを評価する.
- TGCの短期的な利点を検証し,潜在的な害を排除する.
主な方法:
- 700人の小児ICU患者を対象とした将来性,ランダム化制御試験です.
- 3年後の長期フォローアップでは,知能 (IQ),視覚運動統合,注意力,運動調整,実行機能,記憶,行動の評価が行われました.
- 健康な兄弟姉妹と無縁の子供との比較.
主要な成果:
- TGCは,フルスケールIQスコアに影響したり,悪い結果 (死亡または重度の障害) の発生率を増やしたりしませんでした.
- TGCと通常ケア (UC) グループ間の知能,視覚運動統合,または記憶の違いは観察されなかった.
- TGCは,運動調整と認知の柔軟性を大幅に改善しました.
結論:
- ICUでTGCを投与された子どもたちは,UCを投与された子どもと比較して,フォローアップ時に知能の測定値が悪くなかった.
- TGCによって誘発された短期的な低血糖症は,有害な神経認知的結果と関連しませんでした.


関連する概念動画
 01:22
Diabetes Mellitus: Type 2 and Gestational
5.0K
Type 2 diabetes, characterized by insulin resistance, arises when the insulin receptors on cells lose responsiveness to insulin, diminishing the cell's capacity to take up glucose, resulting in elevated blood glucose levels. To receive a diagnosis of Type 2 diabetes, a series of blood glucose tests are necessary to assess whether the blood glucose falls within normal parameters. If the result is out of the normal range, a patient may be diagnosed as prediabetic or diabetic, depending on the...
5.0K
 01:02
Glucose Homeostasis: Regulation of Blood Glucose
4.4K
Carbohydrates consumed through foods are converted into glucose, a crucial energy source for the body. In the prandial state, high blood glucose levels stimulate the secretion of insulin from the pancreas. Insulin inhibits hepatic glucose production and stimulates glucose uptake and metabolism by muscle and adipose tissue. The excess glucose is converted into glycogen and stored in the liver and muscles.
During fasting, when blood glucose levels are low, the pancreas secretes glucagon. it...
During fasting, when blood glucose levels are low, the pancreas secretes glucagon. it...
4.4K
 01:26
Type I Diabetes II: Pathophysiology
122
Type 1 diabetes mellitus arises from an immune-mediated destruction of pancreatic β-cells, resulting in an absolute deficiency of insulin. This process develops in genetically susceptible individuals when autoimmunity, environmental exposures, and immunologic dysregulation converge to trigger a targeted attack on the insulin-producing cells of the pancreas. The β-cells are located within the islets of Langerhans and are essential for regulating blood glucose by facilitating cellular...
122
 01:19
Type I Diabetes III: Clinical Manifestations
53
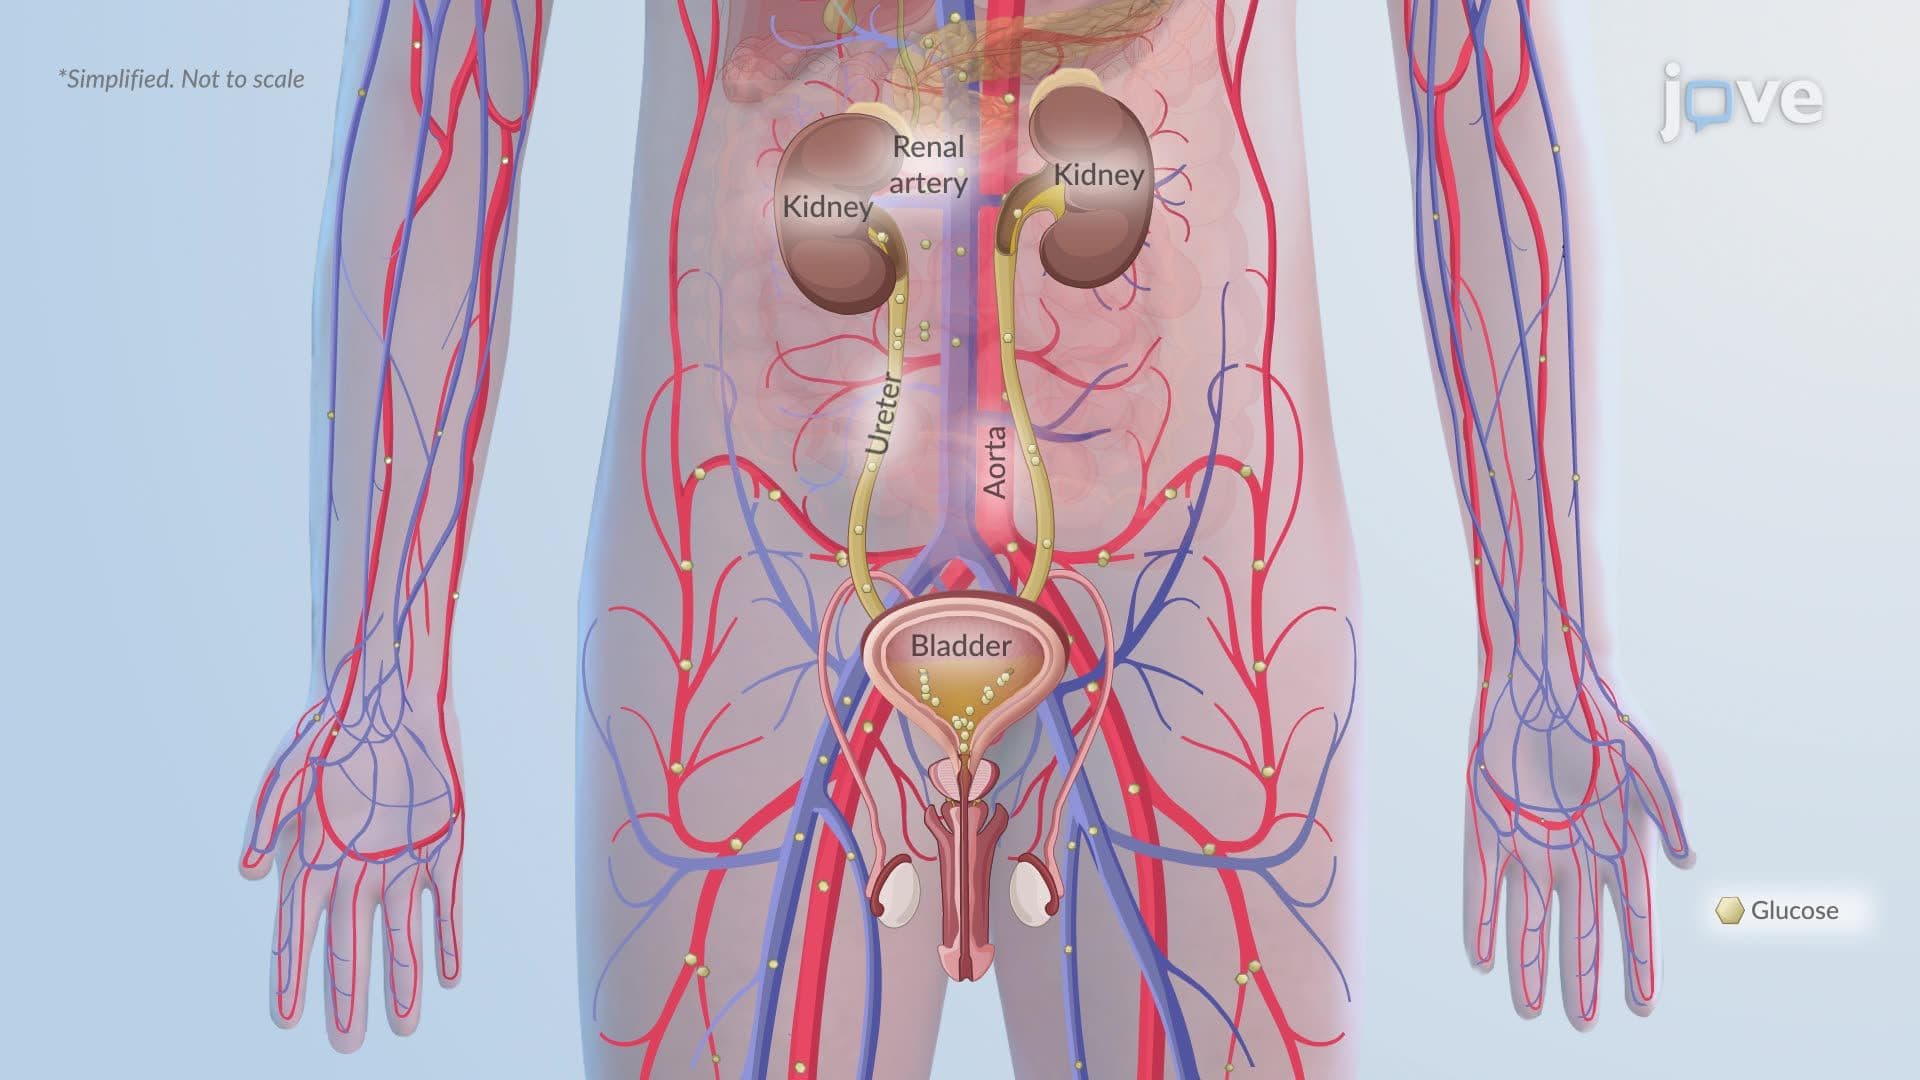
Type 1 diabetes mellitus typically presents with rapid-onset symptoms due to the body’s inability to utilize glucose in the absence of insulin. Since insulin is required for glucose uptake into cells, its deficiency leads to hyperglycemia and cellular energy deprivation, resulting in characteristic clinical features.Polyuria and PolydipsiaOne of the earliest, most prominent symptoms is polyuria (excessive urination). When blood glucose concentrations rise above the renal threshold, the...
53
 01:29
Hyperglycemia
35
Hyperglycemia is an abnormally high blood glucose level. It is diagnosed by fasting glucose ≥126 mg/dL, 2-hour oral glucose tolerance test (or OGTT) ≥200 mg/dL, random glucose ≥200 mg/dL with symptoms, or HbA1c ≥6.5%. However, HbA1c results may be unreliable in certain conditions, such as anemia or hemoglobinopathies, and the diagnosis should be confirmed unless classic symptoms are present. Postprandial hyperglycemia is typically considered significant when glucose...
35
 01:22
Diabetic Ketoacidosis ll: Pathophysiology
61
Diabetic ketoacidosis (DKA) is a metabolic emergency characterized by hyperglycemia, ketonemia, and metabolic acidosis. It results from severe insulin deficiency and an excess of counterregulatory hormones, leading to uncontrolled lipolysis, ketogenesis, and widespread electrolyte and fluid disturbances.Pathophysiology The central event in DKA is a profound loss of insulin action. Without insulin, glucose uptake in insulin-dependent tissues is impaired, while hepatic glucose production...
61