
持続的な炎症が肝臓のメバロナート経路に及ぼす影響は,高血糖症に起因する
Daniel Okin1, Ruslan Medzhitov2
1Department of Immunobiology, Yale University School of Medicine, New Haven, CT 06520, USA.
Cell
|March 22, 2016

まとめ
持続的な炎症は,肝臓のグルコース生成を増加させ,血糖を上昇させます. これは,CYP7A1の抑制によって発生し,RHO関連タンパク質キナーゼの活性化とグルコースホメオスタシスの変化を引き起こします.
科学分野:
- 生物化学
- 生理学
- 免疫学
背景:
- 血糖のコントロールは生存に不可欠です.
- 持続的な炎症は,感染症,肥満,および2型糖尿病におけるグルコースホメオスタシスの障害と関連しています.
- これらの状態における炎症の正確な役割は完全に理解されていません.
研究 の 目的:
- 持続的な炎症がグルコースホメオスタシスに影響するメカニズムを調査する.
- 炎症による高血糖症に関与する分子要因を特定する.
主な方法:
- 持続的な炎症の背景にある肝臓のグルコース生成の分析
- メバロナート経路とその中間物質の調査
- CYP7A1発現とRHOC活性に関する評価
- RHO関連タンパク質キナーゼ信号の評価
主要な成果:
- 継続的な炎症は血糖値の上昇につながる.
- 炎症は肝臓のグルコース生成を増加させる.
- CYP7A1は持続的な炎症の間に抑制され,中間代謝物質の蓄積を引き起こします.
- RHOCのプレニル化と,その後のRHO関連タンパク質キナーゼの活性化が観察されています.
結論:
- 持続的な炎症は,新しいメカニズムを通してグルコースの恒常性を変化させます.
- この経路は,CYP7A1抑制,メバロナート経路の変化,およびRHO関連タンパク質キナーゼの活性化を含む.
- この発見は,炎症に関連した代謝障害に関する新しい洞察を提供します.
関連する概念動画
 01:17
Gastritis-II: Pathophysiology
1.7K
Gastritis is marked by disruption of the mucosal barrier that usually protects the stomach tissue from digestive juices and manifests in acute and chronic forms.
In acute gastritis, the gastric mucosa becomes swollen and red and undergoes superficial erosion. Superficial ulceration may lead to bleeding.
In chronic gastritis, persistent or repeated insults lead to chronic inflammatory changes and, eventually, thinning or atrophy of the gastric tissue.
Gastritis can stem from various causes, each...
In acute gastritis, the gastric mucosa becomes swollen and red and undergoes superficial erosion. Superficial ulceration may lead to bleeding.
In chronic gastritis, persistent or repeated insults lead to chronic inflammatory changes and, eventually, thinning or atrophy of the gastric tissue.
Gastritis can stem from various causes, each...
1.7K
 01:22
Effect of Hepatic Disease on Pharmacokinetics: Pathophysiologic Assessment and Liver Function Test
256
In clinical practice, the direct measurement of hepatic blood flow to evaluate liver function presents significant challenges due to the intricate and specialized nature of the necessary techniques. Consequently, healthcare professionals often rely on empirical estimates derived from thorough patient examinations and liver function tests to gauge liver health. Among the tools at their disposal, the Child–Pugh and MELD scoring systems stand out for their ability to categorize and assess...
256
 01:14
Effect of Hepatic Disease on Pharmacokinetics: Active Drug, Metabolite and Fraction of Metabolized Drug
291
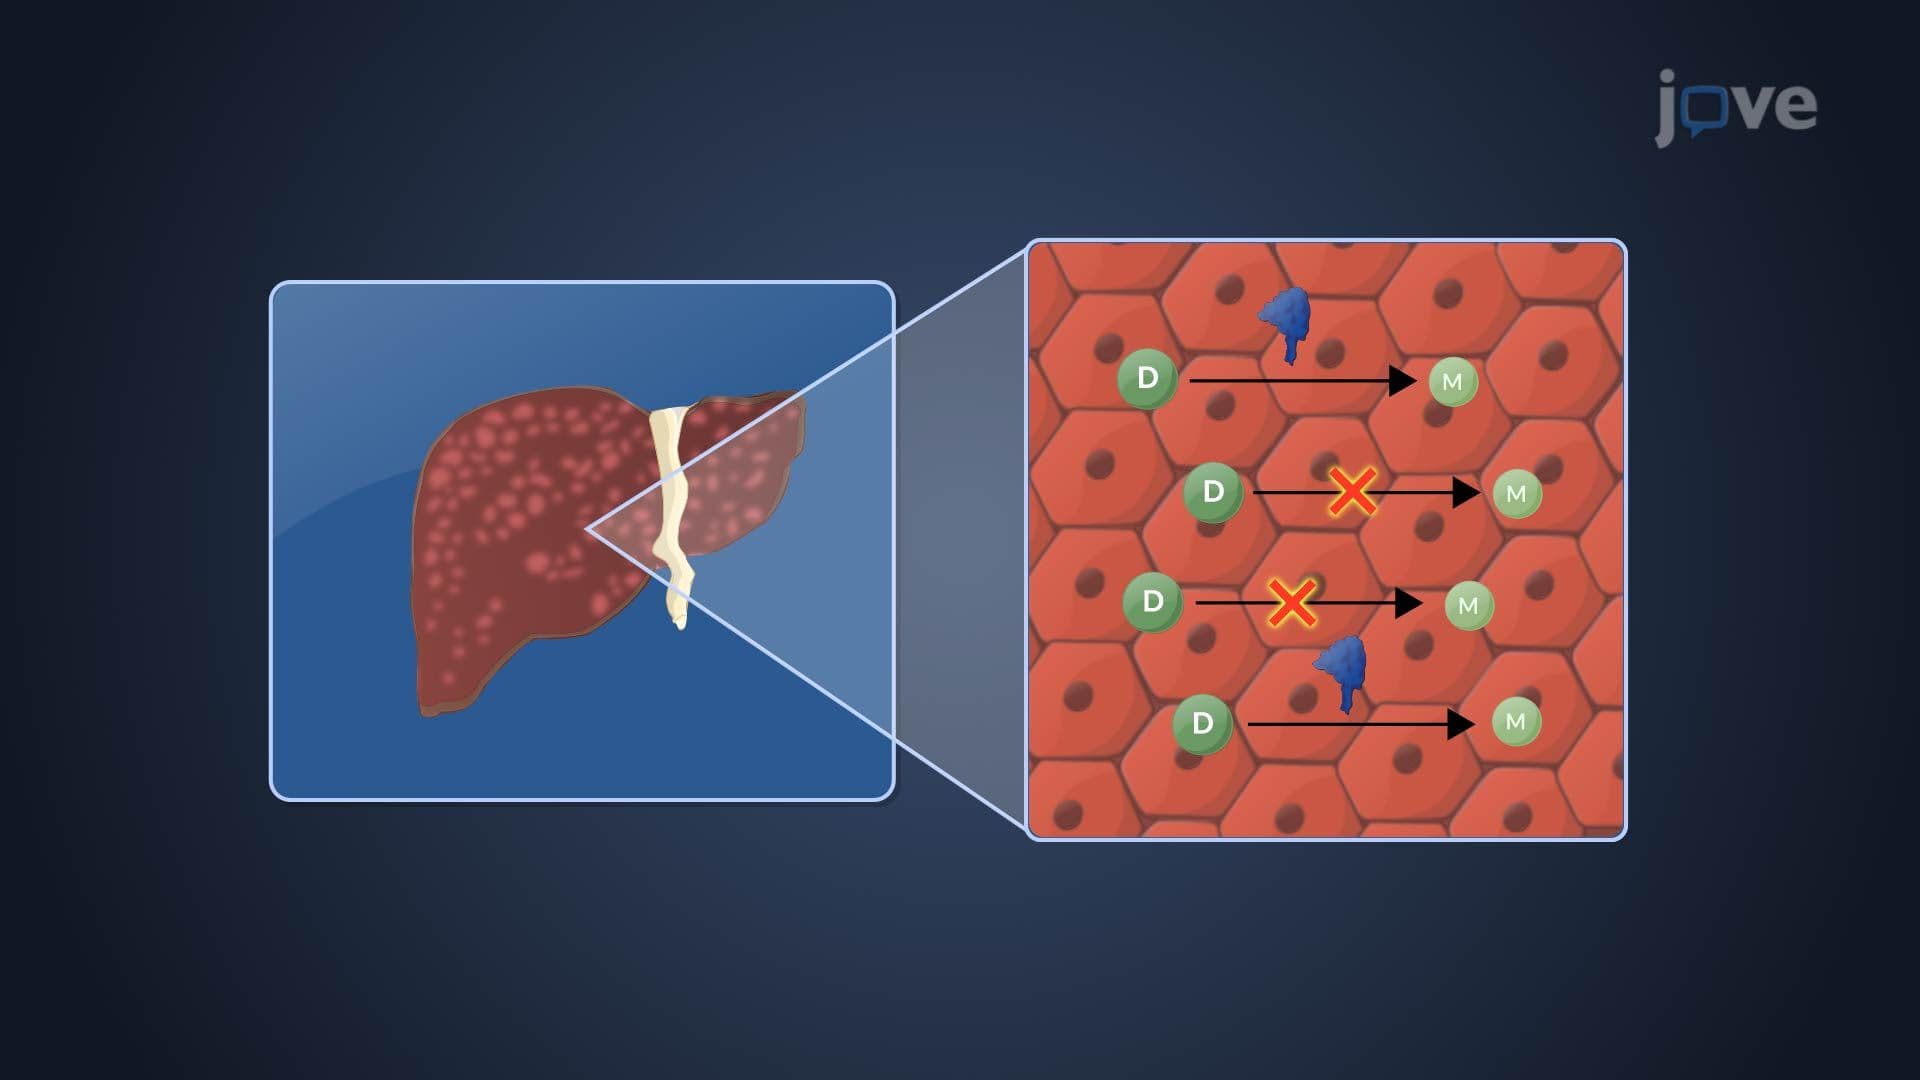
In pharmacotherapy, monitoring drug concentrations is paramount, especially for drugs whose therapeutic effects hinge on both the active compound and its metabolite. Hepatic impairment profoundly influences drug potency by altering liver function. If the drug is more potent than its metabolite, impaired liver function amplifies drug activity due to elevated drug concentration levels. Conversely, if the metabolite holds greater potency, diminished liver function diminishes drug activity by...
291
 01:08
Effect of Hepatic Disease on Pharmacokinetics: Dose Adjustments Due to Hepatic Impairment
335
Hepatic impairment, characterized by decreased liver function, does not uniformly mandate adjustments in drug dosage. Whether dosage modifications are necessary depends on various factors related to the drug's metabolism and elimination pathways. If a drug is primarily excreted via the kidneys and bypasses significant hepatic processing, if it undergoes minimal metabolic transformation in the liver, or if it is volatile and primarily expelled through the lungs, dose adjustments may not be...
335
 01:26
Effect of Hepatic Disease on Pharmacokinetics: Drug Dosing and Hepatic Blood Flow
333
Chronic liver disease significantly impacts drug metabolism due to alterations in hepatic blood flow and enzyme accessibility. This disruption affects the body's pharmacokinetics—the movement and processing of drugs within the system. Key enzymes crucial for metabolizing medications become less accessible, changing how drugs are processed and utilized. Furthermore, liver disease influences the synthesis of plasma proteins, such as albumin and globulins, which play critical roles in drug...
333
 01:16
Hepatic Drug Excretion: Influencing Factors
731
The biliary system of the liver, crucial for bile secretion and drug excretion, comprises intrahepatic bile ducts that merge to form the common hepatic duct. This duct, carrying hepatic bile, combines with the cystic duct, draining the gallbladder and forming the common bile duct, which empties into the duodenum. Bile, produced by hepatic cells lining the bile canaliculi, is composed primarily of water, bile salts, pigments, electrolytes, and lesser amounts of cholesterol and fatty acids. Bile...
731